Key takeaways
- 1Knee arthroscopy is keyhole surgery that uses a small camera to examine the inside of the knee and, when appropriate, treat a clearly identified problem.
- 2Common arthroscopic procedures include meniscus repair, partial meniscectomy, loose-body removal, selected cartilage treatment and synovial surgery.
- 3The procedure is usually performed as day surgery, and patients having a simple arthroscopy often begin walking soon after the operation.
- 4Recovery depends more on what is done inside the knee than on the size of the skin incisions. A meniscus repair generally requires substantially more rehabilitation than simple trimming or loose-body removal.
- 5Routine arthroscopic lavage or debridement is not recommended simply for knee osteoarthritis, and exercise-based treatment is usually preferred over arthroscopic partial meniscectomy for degenerative meniscal tears without a specific surgical indication.
Overview
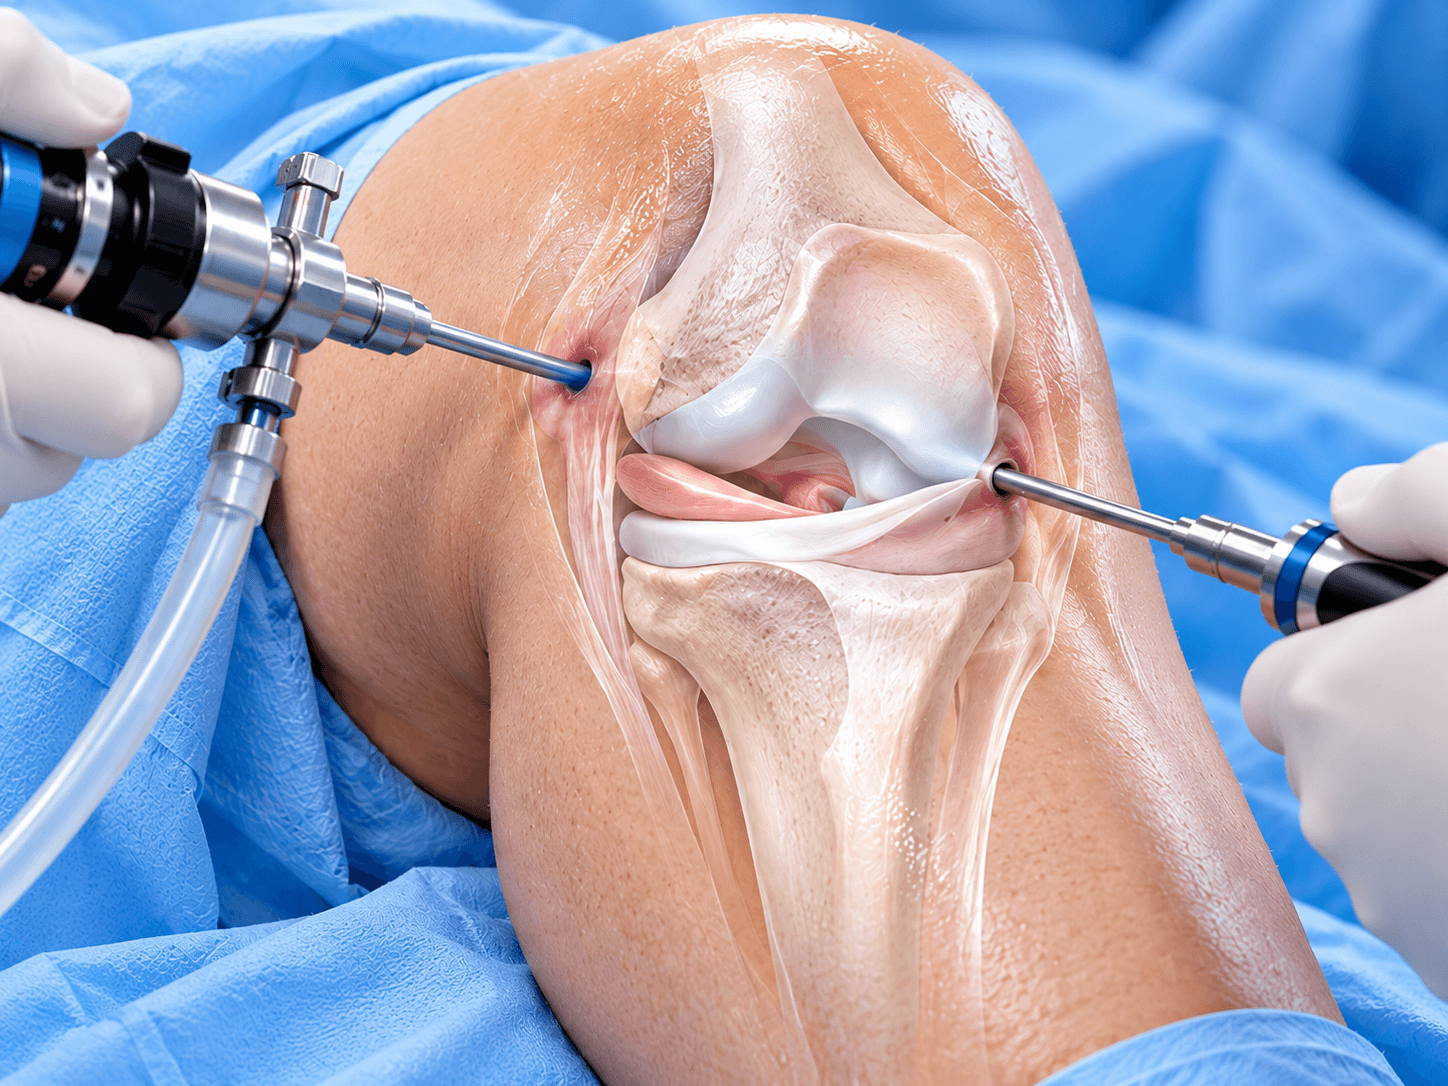
Knee arthroscopy is a minimally invasive surgical technique in which an orthopaedic surgeon inserts a small camera called an arthroscope into the knee through a small incision to examine and treat structures inside the joint. Additional small portals can be created for specialized instruments when treatment is required.
The arthroscope contains a light source and camera. Images from inside the knee appear on a monitor, allowing the surgeon to inspect structures that include the menisci, articular cartilage, anterior cruciate ligament, posterior cruciate ligament, synovium and joint surfaces.
Knee arthroscopy is often described as keyhole knee surgery because the incisions are much smaller than those used during open surgery. However, the small size of the incisions does not necessarily mean that every arthroscopic procedure has a short recovery. What happens inside the joint matters much more than the size of the portals.
A diagnostic arthroscopy with minimal treatment can recover relatively quickly. Arthroscopic meniscus repair, cartilage restoration or ligament reconstruction can require months of rehabilitation because repaired biological tissues need time to heal.
For this reason, patients should ask not only whether they are having a knee arthroscopy, but what procedure will actually be performed arthroscopically.
What Can the Surgeon See During Knee Arthroscopy?
The arthroscope provides a magnified view of the internal knee structures. The surgeon can examine the medial and lateral compartments, the surfaces of the femur and tibia, the underside of the kneecap, both menisci and the central ligaments.
This direct visualization can identify cartilage damage, meniscal tears, loose fragments, synovial abnormalities and other intra-articular findings. The surgeon can also test the stability and quality of structures using small probes.
Modern MRI can diagnose many knee injuries before surgery, so arthroscopy is no longer routinely required simply to discover what is wrong. Diagnostic arthroscopy is generally reserved for situations where symptoms remain significant despite appropriate assessment, or when the surgeon expects to treat a specific problem during the same procedure.
Knee Arthroscopy Is a Surgical Approach, Not One Operation
This distinction is particularly important for patients researching the procedure online.
A patient can say, “I am having knee arthroscopy,” while actually having any of several different operations.
One person may have a loose fragment of cartilage removed. Another may have a torn meniscus repaired with sutures. Another may have an unstable portion of meniscus trimmed. A fourth patient may undergo treatment of an osteochondral lesion.
These operations can all use an arthroscope but have different indications, restrictions and recovery periods.
This is why a generic statement such as “knee arthroscopy recovery takes two weeks” is potentially misleading.
How Knee Arthroscopy Has Changed
Arthroscopic surgery transformed orthopaedics because surgeons could examine and treat the inside of a joint without making a large open incision.
Over time, however, research also clarified where arthroscopy does not add meaningful benefit.
One of the most important changes has involved degenerative knee disease. Arthroscopic washing and generalized debridement were previously performed much more frequently for osteoarthritis. High-quality research later demonstrated that routine arthroscopy does not provide meaningful benefit for uncomplicated degenerative knee osteoarthritis.
Similarly, arthroscopic partial meniscectomy was once commonly performed for middle-aged and older adults whose MRI demonstrated a degenerative meniscus tear.
Randomized trials subsequently showed that structured exercise therapy can produce comparable long-term results for many patients with degenerative meniscal tears.
This has led modern orthopaedic practice toward much more selective use of arthroscopy.
The objective is no longer simply to operate because an MRI shows a tear. The surgeon should determine whether the structural finding actually explains the patient's symptoms and whether arthroscopy is likely to change the clinical outcome.
Traumatic and Degenerative Meniscus Tears Are Different
A traumatic meniscus tear in a younger athlete after a twisting injury is different from a degenerative tear found on MRI in a 60-year-old with gradual knee pain.
Acute tears can include displaced fragments that catch inside the joint or restrict movement. Certain tears have enough healing potential to be repaired.
In these situations, arthroscopic treatment can be appropriate.
Degenerative tears develop as meniscal tissue changes with age and joint degeneration. They can appear on MRI even in people who do not have significant knee symptoms.
For many degenerative tears, structured rehabilitation is the preferred initial treatment.
This difference should be made clear on a high-quality knee arthroscopy page because simply grouping every meniscal tear together would be medically inaccurate.
Preserving the Meniscus
When surgery is necessary, modern treatment increasingly emphasizes preserving functional meniscal tissue.
The meniscus distributes load across the knee, contributes to joint stability and helps protect the articular cartilage.
Removing excessive meniscal tissue increases contact pressure within the joint.
For a repairable acute tear, the surgeon may therefore prefer meniscus repair rather than removing the torn section.
Partial meniscectomy remains useful when tissue is unstable, symptomatic and not realistically repairable. The principle is to remove as little functioning meniscus as necessary.
Does Knee Arthroscopy Treat Arthritis?
Knee arthroscopy does not reverse osteoarthritis.
It cannot regrow widespread cartilage that has been lost from an arthritic joint, and simply washing debris from the joint does not change the underlying degenerative process.
For this reason, routine arthroscopic lavage or debridement should not be offered as treatment for osteoarthritis alone.
A person who has osteoarthritis can still occasionally need an arthroscopic operation for a separate specific problem, such as a genuinely loose body that mechanically blocks the knee. That is different from performing arthroscopy to treat the arthritis itself.
This distinction protects patients from receiving an operation that is unlikely to provide meaningful benefit.
Who it's for
- Acute traumatic meniscus tears that remain symptomatic
- Repairable meniscus tears where preserving the meniscus is possible
- Displaced meniscus tears that restrict knee movement or cause true mechanical locking
- Unstable meniscal fragments causing persistent symptoms after appropriate assessment
- Loose bodies made of cartilage or bone moving within the knee joint
- Selected focal cartilage injuries
- Osteochondral lesions requiring arthroscopic assessment or treatment
- Synovial disorders requiring biopsy, debridement or synovectomy
- Septic arthritis requiring urgent arthroscopic washout and debridement
- Scar tissue or selected causes of arthrofibrosis
- Selected patellar tracking or intra-articular problems where arthroscopic treatment is clinically appropriate
- ACL or other ligament reconstruction, where arthroscopy forms part of the larger reconstructive procedure
- Persistent symptoms after a traumatic knee injury when examination and imaging support a treatable intra-articular lesion
- Selected unexplained mechanical symptoms when other investigations have not provided an adequate diagnosis and arthroscopy is expected to guide or provide treatment
Good candidates
A good candidate for knee arthroscopy has more than knee pain alone. There should usually be a specific intra-articular problem that corresponds with the patient's symptoms and that arthroscopy can reasonably treat.
A young athlete with an acute displaced meniscal tear after a twisting injury is a very different candidate from an older adult with generalized knee pain, osteoarthritis and an incidental degenerative meniscus tear on MRI. The first patient may have a lesion that benefits substantially from arthroscopic repair. The second may be better treated with exercise, weight management, medication or another nonsurgical approach.
The surgeon should therefore consider symptoms, physical examination, imaging, age, activity, mechanism of injury and previous treatment together.
True Mechanical Locking
The phrase “my knee locks” can mean several things.
Some patients use it to describe momentary stiffness or pain. Others have a genuinely displaced structure preventing the knee from fully extending.
True mechanical locking can be clinically important because a displaced meniscus fragment or loose body may physically block motion.
An acute displaced meniscus tear restricting movement can be a stronger indication for arthroscopic intervention than nonspecific clicking in a degenerative knee.
Acute Meniscus Tears
Patients with acute traumatic tears may be suitable for arthroscopic treatment when symptoms remain significant or the tear is unstable.
MRI is usually the preferred imaging test when an acute meniscus tear is suspected.
The tear pattern, location, tissue quality and blood supply determine whether repair is realistic.
Whenever possible, repairable functional tissue should generally be preserved rather than removed.
Athletes
Athletes frequently undergo knee arthroscopy for traumatic meniscus, cartilage or ligament injuries.
The decision should be based on the injury rather than pressure to return to sport quickly.
A meniscus repair can require a longer initial rehabilitation than partial meniscectomy, but preservation of meniscal tissue can be important for long-term joint health.
The fastest operation is therefore not necessarily the best operation.
Patients With Loose Bodies
A fragment of cartilage or bone can become free inside the knee.
Loose bodies may move around the joint and cause catching, pain or episodic locking.
When symptoms correlate with a clearly identified loose body, arthroscopic removal can be appropriate.
The surgeon should also investigate why the loose body formed. Causes can include osteochondral injury, osteochondritis dissecans, trauma or degenerative disease.
When Knee Arthroscopy Is Usually Not Recommended
Knee arthroscopy should not be presented as a universal treatment for knee pain.
Routine arthroscopic lavage or debridement is not recommended for uncomplicated knee osteoarthritis.
Similarly, a degenerative meniscus tear on MRI does not automatically require arthroscopic partial meniscectomy.
Many adults with degenerative tears improve with structured physiotherapy, and high-quality randomized evidence has shown exercise-based treatment can provide comparable long-term function to arthroscopic partial meniscectomy in this population.
Arthroscopy is also unlikely to help when pain comes primarily from advanced bone-on-bone arthritis affecting much of the joint.
In that situation, treatment should address the underlying osteoarthritis rather than simply cleaning the inside of the knee.
Before surgery
Confirming the Diagnosis
The first step is understanding what is actually causing the knee symptoms.
An orthopaedic surgeon reviews when the symptoms began, whether an injury occurred and what movements reproduce pain. Swelling, locking, catching, giving way and inability to fully extend the knee are particularly relevant.
The surgeon should also know whether symptoms appeared suddenly after trauma or gradually over months or years.
This history helps distinguish acute injuries from degenerative disease.
Physical Examination
The surgeon examines both knees and evaluates swelling, range of motion, tenderness, stability and alignment.
When a meniscus injury is suspected, examination can include joint-line tenderness and maneuvers such as the McMurray or Thessaly tests.
No single physical examination test identifies every meniscal tear.
Combining history, examination and imaging provides a more reliable assessment.
Ligament testing may also be performed because ACL or collateral ligament injuries can occur with meniscal damage.
X-Rays
X-rays do not show the meniscus directly, but they remain useful.
Weight-bearing radiographs can identify osteoarthritis, fractures, alignment abnormalities and loss of joint space.
This is particularly important in middle-aged or older patients.
If advanced arthritis is present, an MRI-detected meniscal tear may not be the main cause of pain.
That information can prevent unnecessary arthroscopy.
MRI
MRI is usually the preferred imaging test for suspected acute meniscal injuries and many other soft-tissue knee conditions.
It can demonstrate the menisci, ligaments, cartilage, bone marrow and surrounding structures.
MRI also helps the surgeon assess whether a tear may be repairable.
However, MRI should not be treated as an automatic indication for surgery.
Structural abnormalities can exist without producing symptoms.
The images need to match the clinical presentation.
Trying Nonsurgical Treatment First
Many knee conditions improve without surgery.
Depending on the diagnosis, treatment can include temporary activity modification, structured physiotherapy, progressive strengthening and appropriate pain management.
The purpose of conservative treatment is not simply to delay an inevitable operation.
For many patients, particularly those with degenerative meniscal symptoms, rehabilitation may be the definitive treatment.
Surgery becomes more relevant when there is a clearly treatable lesion and symptoms persist despite appropriate nonsurgical care, or when a displaced injury needs earlier intervention.
Prehabilitation
Preoperative physiotherapy can be useful when the knee is swollen or weak.
The objectives are to restore as much normal movement as possible, improve quadriceps control and prepare the patient for postoperative exercises.
A stronger, calmer knee usually makes early rehabilitation easier.
Prehabilitation is particularly helpful when arthroscopy forms one component of a larger reconstructive procedure.
Medical Assessment
Simple arthroscopy is generally less physiologically demanding than joint replacement, but it still requires anaesthesia and surgery.
Patients may need blood tests or other investigations depending on age, medical history and hospital protocol.
Significant heart, lung, kidney or metabolic conditions should be discussed with the anaesthetic team.
Diabetes should be reasonably controlled.
Active infection elsewhere in the body may require treatment before elective surgery.
Medication Review
The surgical team needs a complete list of prescription medication, over-the-counter drugs and supplements.
Anticoagulants and antiplatelet medicines require individual instructions.
Certain diabetes medicines may need adjustment because patients often fast before anaesthesia.
Patients should never stop important medication simply because they read online that it is routinely discontinued before surgery.
Planning for Meniscus Repair
When a meniscal tear might be repairable, the patient should understand before surgery that the postoperative plan may change depending on what the surgeon finds.
A tear that looks repairable on MRI may prove unsuitable for repair because of tissue quality or configuration.
Conversely, a surgeon may discover that a tear can be preserved rather than trimmed.
Patients should therefore discuss the possible procedures and recovery implications before signing consent.
Planning Travel
International patients should avoid planning an immediate flight after surgery without clearance.
A simple knee arthroscopy is often performed as a day case, but postoperative swelling, thrombosis risk and the type of procedure still matter.
A patient undergoing meniscus repair may also have different mobility restrictions from someone having a simple partial meniscectomy.
Travel planning should therefore be based on the actual operation rather than the generic label “arthroscopy.”
How the operation is performed
Knee arthroscopy is performed through small portals around the knee. The surgeon introduces a camera into the joint, fills the knee with sterile fluid to improve visibility, systematically examines the internal structures and then introduces specialized instruments through additional portals when treatment is required.
Although the general setup is similar for most arthroscopic procedures, what happens after the initial inspection depends entirely on the patient's diagnosis.
Anaesthesia and Positioning
Knee arthroscopy is commonly performed under general anaesthesia, although spinal or other regional techniques can also be used.
The patient lies on the operating table with the knee positioned so that the surgeon can move it during the procedure.
A tourniquet may be placed around the thigh. Whether it is inflated and for how long depends on the operation and surgeon preference.
The leg is cleaned with antiseptic solution and covered with sterile drapes.
Creating the Arthroscopy Portals
The surgeon makes one or more small incisions around the front of the knee.
These incisions are called portals.
A standard viewing portal allows the arthroscope to enter the joint.
A second portal is commonly created for instruments.
Additional portals may be used when access to a particular structure is required.
The portal positions are selected to give safe access while protecting important structures around the knee.
Inserting the Arthroscope
The arthroscope is a narrow rigid instrument containing a camera and light system.
Sterile fluid is introduced into the knee.
The fluid expands the joint and clears blood or debris from the field of view.
Images from the camera are displayed on a high-definition monitor.
The surgeon can inspect structures at close range and move the knee to see different areas of the joint.
Systematic Inspection of the Knee
A careful arthroscopy usually involves examining the knee systematically rather than immediately treating the first visible abnormality.
The surgeon assesses the patellofemoral compartment and the cartilage beneath the kneecap.
The medial compartment is inspected, including the medial femoral condyle, medial tibial plateau and medial meniscus.
The central compartment is assessed for the ACL and PCL.
The lateral compartment is then examined, including the lateral meniscus and cartilage surfaces.
This systematic examination helps identify additional injuries that may not have been obvious on imaging.
Arthroscopic Probing
A small probe is one of the most useful arthroscopic instruments.
The surgeon can touch or gently move structures while viewing them on the monitor.
For a meniscal tear, probing helps determine whether the tissue is stable, displaced or repairable.
Cartilage defects can also be evaluated for size, depth and stability.
The surgeon's treatment decision therefore depends not only on how something looks but how it behaves mechanically.
Arthroscopic Partial Meniscectomy
What Happens During Partial Meniscectomy?
Partial meniscectomy removes only the unstable portion of a damaged meniscus that cannot reasonably be repaired.
Small arthroscopic punches and motorized shavers trim the torn tissue.
The surgeon then contours the remaining edge to create a stable rim.
The goal is not to remove the whole meniscus.
Modern meniscal surgery aims to retain as much healthy functional tissue as possible.
Why Meniscus Preservation Matters
The menisci distribute force across the knee.
Removing meniscal tissue reduces the contact area between the femur and tibia and increases stress on the remaining cartilage.
The amount of tissue removed therefore matters.
When a tear can heal successfully after repair, preserving the meniscus can be more advantageous than simply trimming it away.
Partial meniscectomy remains useful when the damaged portion is nonviable, unstable or located in tissue with poor repair potential.
Arthroscopic Meniscus Repair
Repairing Instead of Removing the Tear
A meniscus repair attempts to reconnect the torn tissue so it can heal.
Different techniques can be used according to tear location and pattern.
All-inside devices place sutures or anchors entirely within the joint.
Inside-out repair passes sutures from inside the knee through the capsule, where they are tied through a separate small incision.
Outside-in repair can be useful for certain anterior tears.
The surgeon chooses the method based on anatomy and experience.
Which Meniscus Tears Can Be Repaired?
Healing potential is influenced by blood supply.
The outer portion of the meniscus has better vascularity than the inner free edge.
Acute longitudinal tears in vascular tissue often have greater repair potential than complex degenerative tears.
Age is considered, but biological tissue quality and tear pattern can be more important than age alone.
Meniscal root tears and radial tears require specialized repair strategies and should not be treated as ordinary simple tears.
Why Recovery Is Longer After Repair
Removing an unstable fragment does not require tissue to heal back together.
A repair does.
Sutures need to protect the meniscus while biological healing takes place.
This can mean temporary limits on knee bending, weight-bearing or sport.
The longer early rehabilitation is a trade-off made in an attempt to preserve meniscal function.
Loose-Body Removal
Loose fragments inside the joint can be removed arthroscopically.
The surgeon identifies the object with the camera and retrieves it using grasping instruments.
A loose body can be made of cartilage, bone or a combination of tissues.
Large fragments may require slight enlargement of a portal for safe removal.
The underlying cause should be assessed because simply removing a fragment does not prevent another from forming when the original disease remains active.
Cartilage Procedures
Chondroplasty
Chondroplasty involves smoothing unstable edges of damaged articular cartilage.
A motorized shaver can remove loose flaps that catch inside the joint.
The procedure does not regenerate normal cartilage and should not be represented as a cure for widespread osteoarthritis.
It is used selectively for focal unstable lesions.
Microfracture and Bone-Marrow Stimulation
Certain small focal full-thickness cartilage defects can be treated using bone-marrow stimulation techniques.
Tiny holes are created in the underlying bone to allow marrow elements to enter the defect.
The resulting repair tissue is different from normal hyaline cartilage.
Patient selection is therefore important.
Larger defects or high-demand patients may be better suited to other cartilage-restoration procedures.
Cartilage Restoration
Some cartilage restoration techniques are performed arthroscopically or with arthroscopic assistance.
These can include osteochondral graft procedures, autologous chondrocyte-related techniques and scaffold-based procedures.
Because recovery varies considerably, these should be discussed as separate cartilage operations rather than generic “simple knee arthroscopy.”
Synovectomy
The synovium is the tissue lining the inside of the joint.
Certain inflammatory or proliferative disorders can cause abnormal synovial tissue.
Arthroscopic synovectomy removes selected abnormal tissue using shavers and other instruments.
The extent of treatment depends on the underlying diagnosis.
Biopsy samples may also be obtained when pathological examination is required.
Arthroscopic Washout for Infection
Septic arthritis is an infection inside the natural knee joint and can rapidly damage cartilage.
Urgent treatment is usually required.
Arthroscopy can be used to irrigate the knee thoroughly and remove infected or inflamed tissue.
Samples are collected for microbiological testing.
Antibiotic treatment accompanies surgery.
This is very different from arthroscopic lavage for osteoarthritis; the indication here is infection, not degeneration.
Arthrofibrosis and Scar-Tissue Release
Selected patients with severe loss of movement due to intra-articular scar tissue may undergo arthroscopic release.
Scar bands are identified and carefully removed.
The operation is usually combined with an intensive rehabilitation strategy because simply removing scar tissue without restoring movement can lead to recurrence.
The decision to perform arthrolysis depends on why the knee became stiff and whether less invasive measures have failed.
ACL Reconstruction and Knee Arthroscopy
Most modern ACL reconstructions use arthroscopy to assess the knee and position the ligament graft.
However, ACL reconstruction should be considered a separate reconstructive procedure rather than a routine knee arthroscopy.
The operation involves graft harvesting or preparation, bone tunnels or sockets, graft fixation and a much longer rehabilitation programme.
For Orthopedic Abroad, the dedicated ACL Reconstruction page should therefore remain the primary resource for that procedure.
Completing the Arthroscopy
Once treatment is finished, the surgeon performs a final examination.
Instruments and arthroscope are removed and fluid drains from the knee.
The small portal incisions are closed with sutures, adhesive strips or another closure technique.
A sterile dressing and compression bandage may be applied.
The patient is then transferred to the recovery area.
Hospital stay
Most uncomplicated knee arthroscopy surgery is performed as a day-case procedure.
After surgery, patients recover from the anaesthetic in a monitored area. Nurses check pain, blood pressure, circulation and the surgical dressings.
Once the patient is medically stable, has eaten or drunk appropriately and can move safely, discharge can usually occur later the same day.
An overnight stay is occasionally necessary because of medical conditions, late operating time, postoperative nausea, pain control or a more complex procedure.
Walking Before Discharge
After many simple arthroscopic procedures, patients are encouraged to stand and place weight through the leg as tolerated.
Crutches may be provided for comfort and balance.
Some patients need them only briefly.
However, this does not apply universally.
A meniscus repair, cartilage procedure or other reconstruction can require partial weight-bearing or a brace.
The surgical team's instructions override any generic arthroscopy advice.
Pain Control
Pain after simple arthroscopy is usually manageable with a multimodal strategy.
Paracetamol or acetaminophen may be used, along with anti-inflammatory medication when medically appropriate.
Local anaesthetic may be injected around the portals or into the knee.
Stronger medication is sometimes prescribed for the early postoperative period.
Pain should generally decrease over time.
Increasing severe pain rather than gradual improvement warrants assessment.
Swelling
Swelling is normal after arthroscopy because the joint has been operated on and filled with fluid.
The amount depends on how much treatment was performed.
Elevation and controlled cold therapy can help reduce discomfort.
Patients should expect that swelling may fluctuate with activity during the first weeks rather than disappearing immediately.
Discharge Instructions
Patients should leave with clear information about wound care, pain medication, weight-bearing, crutches, exercises and follow-up.
They should also know whether stitches need removal.
The discharge plan needs to specify what was actually done during surgery. “Knee arthroscopy performed” is not enough information for the physiotherapist who will supervise rehabilitation.
International patients should receive a copy of the operative report.
Recovery
Recovery after knee arthroscopy can range from a few weeks to several months because the arthroscope is only the surgical approach; the treatment performed inside the knee determines the rehabilitation.
A patient having simple loose-body removal or a limited partial meniscectomy may resume routine activities relatively quickly.
A patient having meniscus repair, cartilage repair or ligament reconstruction should expect a substantially longer recovery.
For a relatively simple arthroscopy, soreness and swelling often improve over the first few weeks and many routine activities return within approximately two to six weeks.
Mild residual swelling can persist longer.
Why the Small Incisions Can Be Misleading
Patients sometimes assume that two small portal incisions mean the knee has undergone only a minor intervention.
The skin wounds may indeed heal quickly.
The tissues inside the knee may take much longer.
If a meniscus has been sutured, the body needs time to heal the repair. If cartilage restoration has been performed, biological repair is even slower.
Recovery instructions should therefore be based on the internal procedure rather than how quickly the portal wounds look normal.
Recovery After Meniscus Repair
Meniscus repair requires a different mindset.
Because the surgeon is trying to heal tissue rather than remove it, the repair must be protected.
Some protocols restrict weight-bearing for a period.
A brace may be used.
Deep knee flexion can be restricted early because it increases load on certain meniscal regions.
The specific tear pattern and repair technique matter.
Progression to running and pivoting sport occurs much later than after uncomplicated partial meniscectomy.
Return to sport after repair can take several months, with many athletes requiring approximately four to seven months or longer depending on the injury and associated procedures.
Recovery After Partial Meniscectomy
Recovery following limited arthroscopic partial meniscectomy is generally faster.
Weight-bearing is commonly allowed relatively early.
The main goals are controlling swelling, restoring full motion and rebuilding quadriceps strength.
Many patients resume everyday activities within several weeks.
The presence of osteoarthritis or cartilage damage can prolong symptoms and may limit how much improvement surgery provides.
Returning to Work
For uncomplicated arthroscopy, desk-based employees may return within several days to one or two weeks depending on swelling, commuting and ability to elevate the leg.
Physically demanding employment usually requires more time.
Jobs involving prolonged kneeling, climbing or heavy lifting place greater stress on the recovering knee.
Meniscus repair or cartilage treatment can substantially extend time away from physical work.
Driving
Patients should drive only when they have adequate control of the leg, can enter and leave the vehicle safely and can perform an emergency stop without hesitation.
They also need to be free from medication that impairs alertness.
A simple arthroscopy may allow driving relatively soon, but recommendations vary.
Right-knee surgery can affect pedal control more directly.
The treating surgeon should provide individual clearance.
Returning to Sport
Return to sport depends on the procedure and sport.
Cycling and swimming are often useful low-impact rehabilitation activities once wounds are appropriately healed.
Running requires adequate strength, minimal swelling and good knee control.
Pivoting sports create additional demands.
A footballer returning after meniscus repair should therefore not follow the same timeline as someone recovering from a small loose-body removal.
Recovery timeline
- Control swelling and walk safely1Control swelling and walk safely
Days 0–3
Details: Rest with the leg elevated when appropriate, begin prescribed knee and ankle exercises, use crutches if needed and take short controlled walks. Weight-bearing restrictions depend on the actual procedure performed.
- Improve movement and normalize walking2Improve movement and normalize walking
Days 4–14
Gradually increase activity, restore full knee extension and progressive flexion, and strengthen the quadriceps. Simple arthroscopy patients may return to sedentary work during this phase.
- Restore routine strength and function3Restore routine strength and function
Weeks 2–6
Progress walking, cycling, balance and strengthening exercises. Higher-impact activity should depend on swelling, movement quality and the arthroscopic procedure rather than time alone.
- Return to unrestricted activity where appropriate4Return to unrestricted activity where appropriate
Weeks 6–12+
Many patients after simple arthroscopy are close to normal activity. Meniscus repairs and cartilage procedures usually remain on a slower, procedure-specific rehabilitation pathway.
- Return to demanding sport after repaired tissue has healed5Return to demanding sport after repaired tissue has healed
Months 3–6+
This phase applies mainly to patients who underwent meniscus repair, cartilage restoration or another reconstructive arthroscopic procedure. Sport-specific strength and functional testing should guide clearance.
Outcomes and success rates
What Determines the Success of Knee Arthroscopy?
There is no meaningful single knee arthroscopy success rate because arthroscopy can refer to many different procedures.
Success after removal of a symptomatic loose body is different from success after meniscus repair.
Results after traumatic meniscal surgery are also different from outcomes when arthroscopy is performed in an arthritic knee.
The most important predictor of benefit is whether the patient has a problem that arthroscopy can actually correct.
A technically perfect arthroscopy cannot solve pain caused primarily by advanced diffuse osteoarthritis.
Outcomes After Acute Meniscus Surgery
Acute traumatic meniscus tears are an area where arthroscopic surgery can have an important role.
Modern treatment places increasing emphasis on preserving the meniscus.
When an acute tear has healing potential, repair can provide better tissue preservation than partial meniscectomy.
Recovery is slower because the tissue needs to heal, but meniscus preservation can be important for long-term joint mechanics.
The exact outcome depends on tear pattern, location, age, tissue quality, rehabilitation and associated ligament injury.
Outcomes After Partial Meniscectomy
Arthroscopic partial meniscectomy can relieve symptoms caused by selected unstable, nonrepairable meniscus tears.
However, it should not be treated as routine treatment for every MRI-detected tear.
Degenerative tears deserve particular caution.
Multiple randomized studies have demonstrated that exercise-based physiotherapy produces outcomes comparable to arthroscopic partial meniscectomy for many middle-aged patients with degenerative meniscal tears.
Long-term evidence has also raised concern that unnecessary removal of meniscal tissue may contribute to structural degenerative progression.
The modern goal is therefore appropriate selection and preservation rather than simply removing abnormal MRI findings.
Arthroscopy for Osteoarthritis
Routine arthroscopic washout or debridement does not provide a clinically meaningful treatment for osteoarthritis.
Arthritis affects the biology and structural surfaces of the joint.
Flushing the joint does not restore lost cartilage.
This is why major guidelines recommend against arthroscopic lavage or debridement for osteoarthritis as the indication itself.
Patients with arthritis should instead receive evidence-based nonsurgical osteoarthritis management and, when disease becomes severe and disabling, consideration of appropriate reconstructive surgery such as knee replacement.
Implants and technology
Arthroscopy Equipment
Modern arthroscopy uses high-definition camera systems and powerful light sources.
The arthroscope itself is narrow enough to pass through a small portal while providing a detailed view of the joint.
Fluid pumps maintain visualization by controlling joint pressure.
Specialized instruments include probes, graspers, punches, scissors and motorized shavers.
Radiofrequency devices can be used selectively for soft-tissue treatment and haemostasis.
Meniscus Repair Devices
Modern meniscus repair can use all-inside suture devices, anchors or traditional suture techniques.
All-inside systems can reduce the need for additional incisions.
Inside-out techniques remain valuable for certain tear patterns because they allow robust suture placement.
Technology should not determine whether a meniscus is repaired.
The tear pattern and biological healing potential should determine the treatment, with the surgeon choosing the most appropriate repair device.
Arthroscopic Visualization and 4K Systems
Newer arthroscopy towers can provide high-definition or 4K visualization.
Improved image quality can help distinguish subtle tissue planes and cartilage lesions.
Some systems also offer enhanced image-processing modes.
These technologies may improve visualization, but they do not change the fundamental indications for arthroscopy.
A better camera cannot turn an inappropriate operation into an appropriate one.
Navigation and Augmented Technology
Computer-assisted tools are expanding within orthopaedic surgery.
Navigation is well established in certain joint replacement procedures, while its routine role in simple knee arthroscopy is much smaller.
Augmented-reality guidance, artificial intelligence and advanced imaging integration are areas of ongoing development.
For routine meniscal surgery, experienced arthroscopic technique and accurate diagnosis remain far more important than adding expensive digital technology.
Risks and how they are managed
All surgery carries risk. Partner hospitals follow enhanced-recovery and infection-prevention protocols, and your surgeon will discuss the risks specific to your case before consent.
- Infection: Infection after routine knee arthroscopy is uncommon, but any increasing redness, warmth, drainage, fever or worsening pain requires prompt assessment.
- Blood clots: Deep-vein thrombosis can occur after knee surgery. The risk depends on patient health, mobility and the procedure performed.
- Bleeding or haemarthrosis: Blood can accumulate within the knee and increase swelling and discomfort.
- Persistent swelling: Some swelling can continue for several weeks, particularly after more extensive treatment or when underlying arthritis is present.
- Persistent pain: Arthroscopy cannot guarantee that knee pain will resolve, particularly when symptoms arise from degenerative joint disease rather than the treated lesion.
- Knee stiffness: Temporary stiffness is common. Significant persistent stiffness can occasionally require additional treatment.
- Nerve irritation or numbness: Small nerves near the portals can become irritated, producing numbness or tingling around the incision.
- Blood-vessel injury: Major vascular injury is rare but potentially serious.
- Meniscus repair failure: A repaired meniscus may fail to heal or can tear again, sometimes requiring additional surgery.
- Progression of osteoarthritis: Removing meniscal tissue does not prevent arthritis and excessive loss of meniscus can increase joint loading.
- Cartilage injury: Surgical instruments can rarely damage articular cartilage.
- Instrument complications: Breakage of arthroscopic equipment within the joint is rare.
- Anaesthetic complications: Reactions to anaesthetic medicines, breathing problems or cardiovascular complications can occur, although serious events are uncommon in appropriately assessed patients.
- Need for further surgery: Persistent symptoms, recurrent tears, repair failure or progression of the underlying condition may eventually require another procedure.
Alternatives
- Structured physiotherapy: Exercise-based rehabilitation is often the preferred initial treatment for degenerative meniscal symptoms and many nonlocking knee problems.
- Activity modification: Temporarily reducing painful impact or twisting activities can allow inflammation to settle while strength is rebuilt.
- Pain medication: Appropriate analgesics or anti-inflammatory medication can help selected patients manage symptoms while rehabilitation progresses.
- Weight management: When excess body weight contributes to osteoarthritis symptoms, weight reduction can decrease knee load.
- Injections: Corticosteroid or other injections may be considered for selected conditions, particularly when symptoms are driven by inflammation or osteoarthritis rather than a surgically treatable mechanical lesion.
- Observation: Some stable meniscus tears do not require surgery when symptoms are improving and there is no locking.
- Meniscus repair instead of meniscectomy: When arthroscopy is required and a tear has healing potential, preserving the meniscus may be preferable to trimming it.
- Cartilage restoration surgery: Selected focal defects may require a dedicated restorative procedure rather than simple chondroplasty.
- Ligament reconstruction: Knee instability caused by an ACL or other ligament tear may require reconstruction rather than isolated diagnostic arthroscopy.
- Knee osteotomy: Selected younger patients with localized arthritis and malalignment may benefit from realignment surgery.
- Partial or total knee replacement: Advanced compartmental or widespread osteoarthritis may be better treated with arthroplasty rather than arthroscopic debridement.
What Knee Arthroscopy costs
The contracted Turkey partner package next to approved self-pay benchmarks. Benchmarks are 20th–80th percentile ranges of approved records, normalised to USD.
Turkey package
$2,500 – $4,500
United States self-pay
$7,900 – $19,800
United Kingdom self-pay
$3,350 – $10,100
Typical self-pay range by country
Surgeons who perform Knee Arthroscopy
All surgeonsSurgeon profiles for this procedure are being added.
Hospitals offering this procedure
Antalya Yaşam Hospital
Private hospital in Muratpaşa, Antalya, with an orthopedics and traumatology department
BHT Clinic Istanbul Tema Hospital
Large private hospital in Atakent, Küçükçekmece, with an orthopedics and traumatology unit
Biruni University Hospital
University hospital in Küçükçekmece, Istanbul, with a published orthopedics and traumatology department
Çankaya Hospital for Orthopedic Care
Çankaya Hospital for Orthopedic Care is an orthopedic hospital in central Ankara with robotic-arm assisted surgery
Sources and references
Peer-reviewed guidance and institutional sources used to write and review this page.
- 01
- 02Clinical Practice Guideline for the Management of Acute Isolated Meniscal Pathology
American Academy of Orthopaedic Surgeons, 2024
https://www.aaos.org/quality/quality-programs/acute-isolated-meniscal-pathology/
- 03Plain Language Summary — Management of Acute Isolated Meniscal Pathology
American Academy of Orthopaedic Surgeons, 2024
https://orthoinfo.aaos.org/globalassets/pdfs/plain-language-summary_meniscus-tears-2024.pdf?tab=all_guidelines&utm_source=chatgpt.com
- 04Knee Arthroscopy Post-operative Advice
Cambridge University Hospitals NHS Foundation Trust, 2025
https://www.cuh.nhs.uk/patient-information/knee-arthroscopy-post-operative-advice/
- 05Knee Arthroscopy — Patient Information
Royal National Orthopaedic Hospital NHS Trust
https://www.rnoh.nhs.uk/patients-and-visitors/patient-information-guides/knee-arthroscopy-patients-information
- 06Knee Arthroscopy
Leeds Teaching Hospitals NHS Trust, 2025
https://www.leedsth.nhs.uk/patients/resources/knee-arthroscopy
- 07Osteoarthritis in Over 16s: Diagnosis and Management — Arthroscopic Procedures
National Institute for Health and Care Excellence
https://www.nice.org.uk/guidance/NG226/chapter/recommendations
- 08Effect of Physical Therapy vs Arthroscopic Partial Meniscectomy in People With Degenerative Meniscal Tears: Five-Year Follow-up of the ESCAPE Randomized Clinical Trial
JAMA Network / PubMed, 2022
https://pubmed.ncbi.nlm.nih.gov/35802374/