Key takeaways
- 1Total knee replacement resurfaces damaged areas of the femur and tibia with prosthetic components rather than removing the entire knee. It is mainly used for severe arthritis that causes persistent pain, stiffness and disability.
- 2Total knee replacement surgery generally takes about 1–2 hours, and most patients begin standing and walking on the day of surgery or within 24 hours as part of modern rehabilitation.
- 3Most patients make major functional progress during the first 6–12 weeks, but swelling, strength, endurance and confidence can continue improving for six months to one year.
- 4Knee replacements are designed to function for decades. Registry evidence estimated that approximately 82% of total knee replacements remained unrevised at 25 years, while current NHS patient guidance describes modern knee replacements as lasting around 25 years in many patients.
- 5Robotic-assisted total knee replacement can improve the accuracy of component positioning and reduce alignment outliers, but recent randomized evidence has not shown a consistent clinically meaningful advantage in patient-reported function over well-performed conventional knee replacement.
Overview
Total knee replacement is an operation that replaces the damaged joint surfaces of the knee with artificial metal and plastic components. The medical term is total knee arthroplasty, often abbreviated to TKA. It is one of the most established operations for people whose knee has been severely damaged by osteoarthritis or another form of arthritis and whose pain and loss of function have become difficult to control with non-surgical treatment.
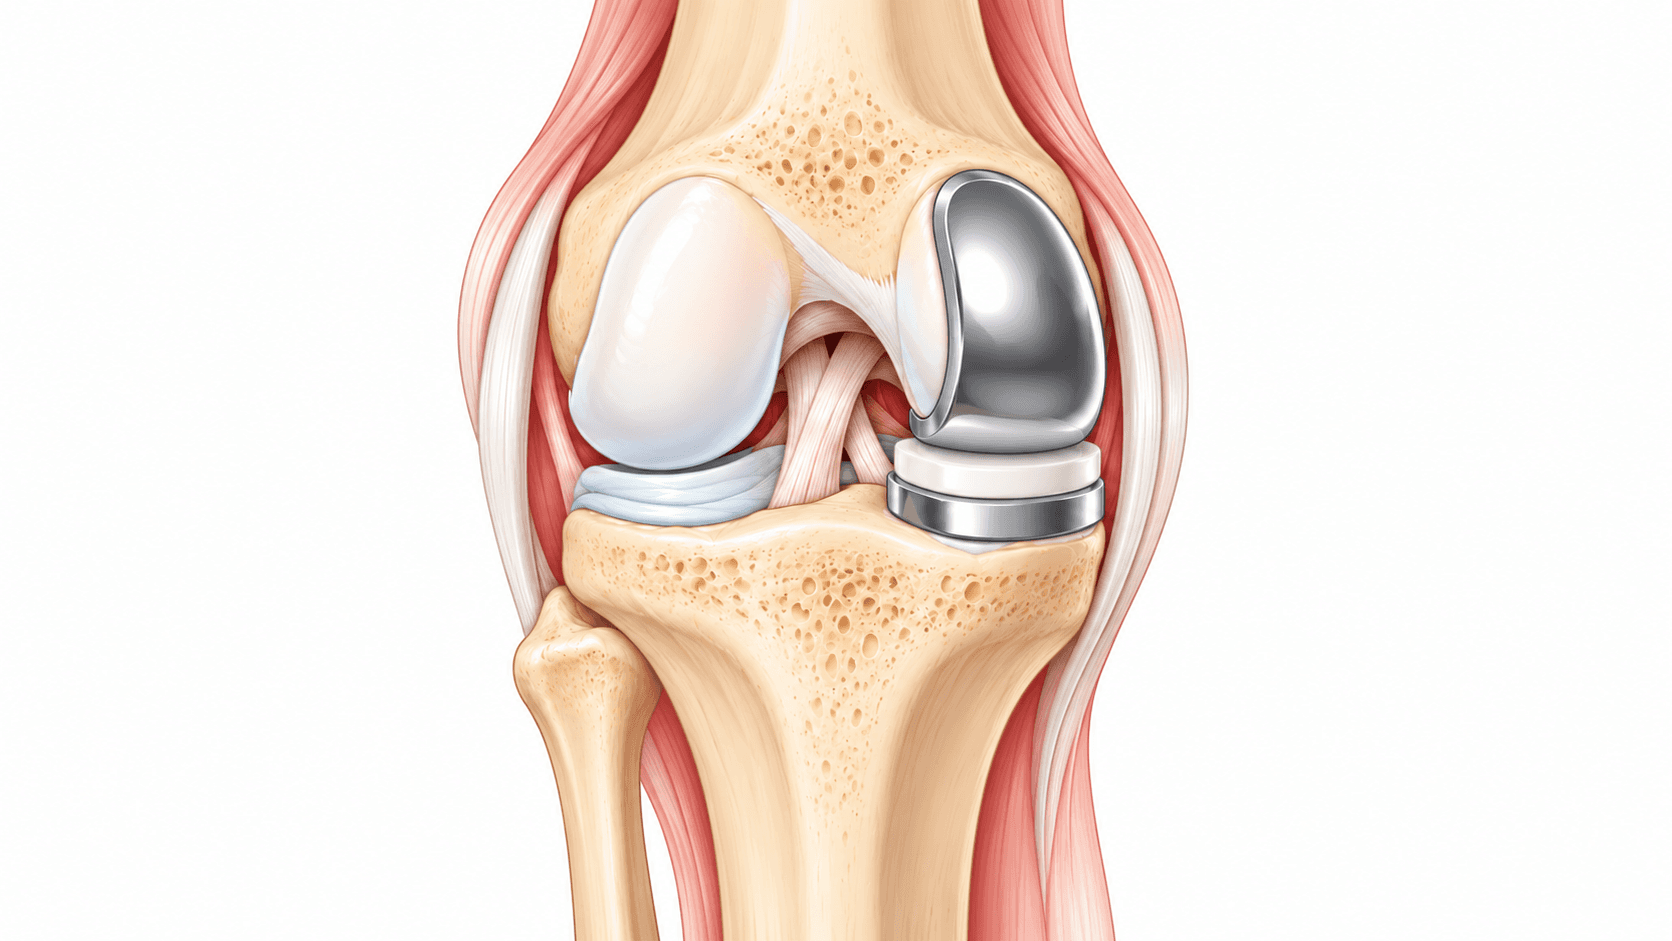
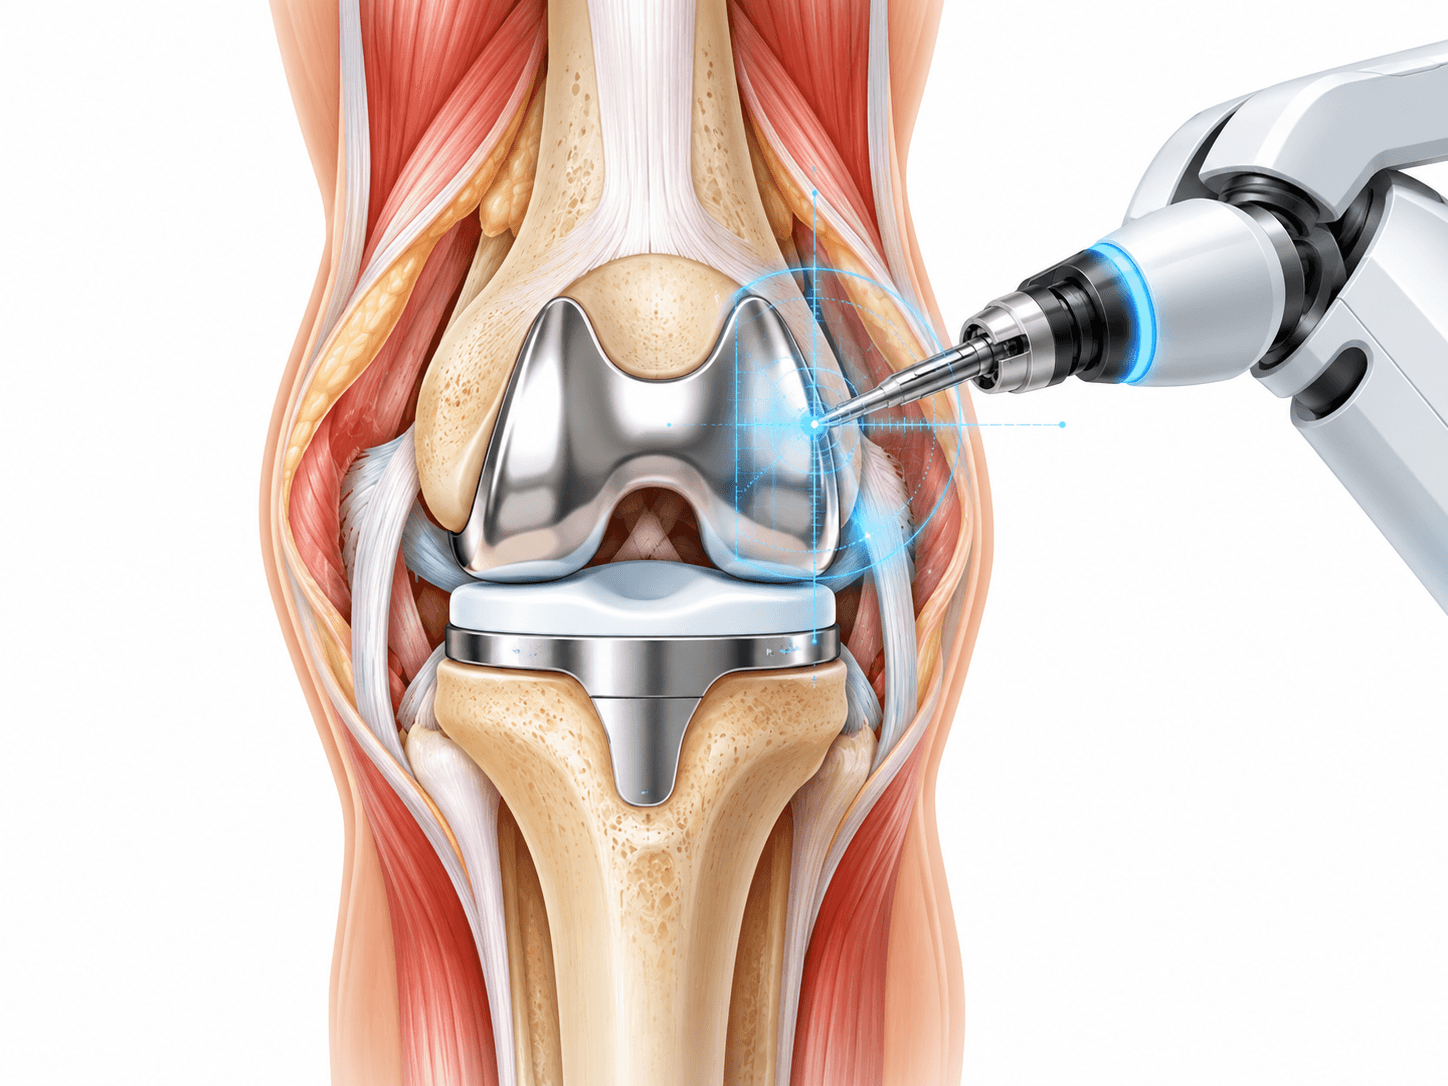
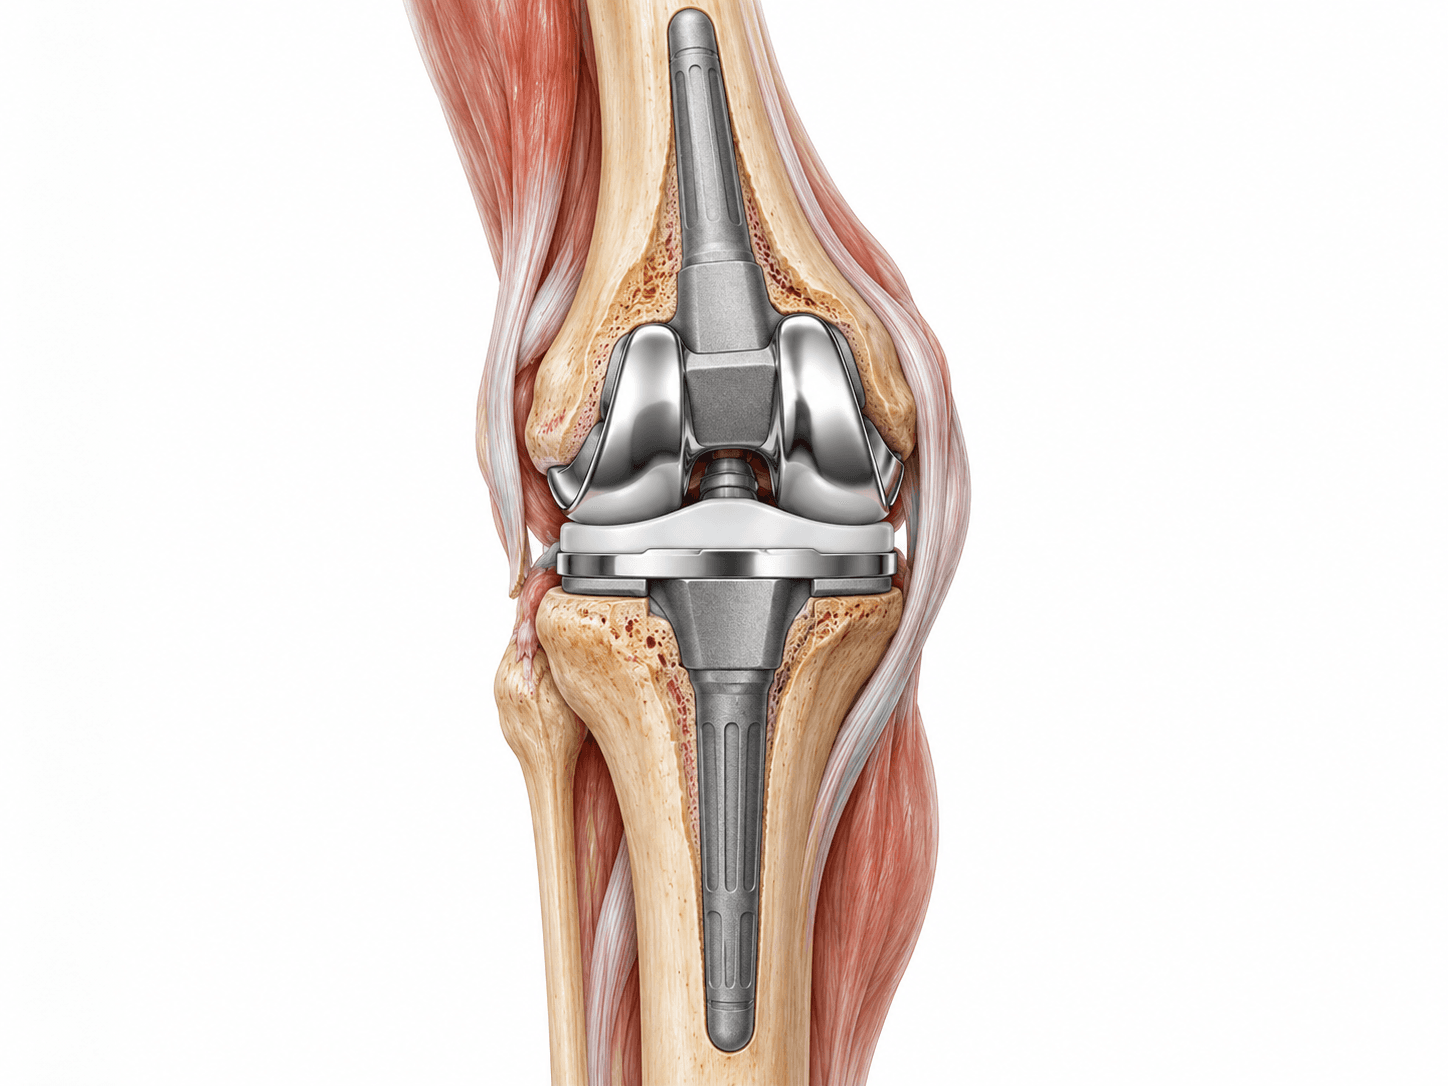
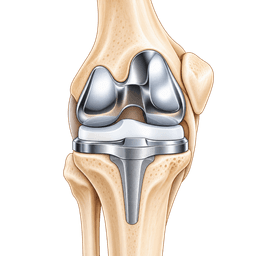
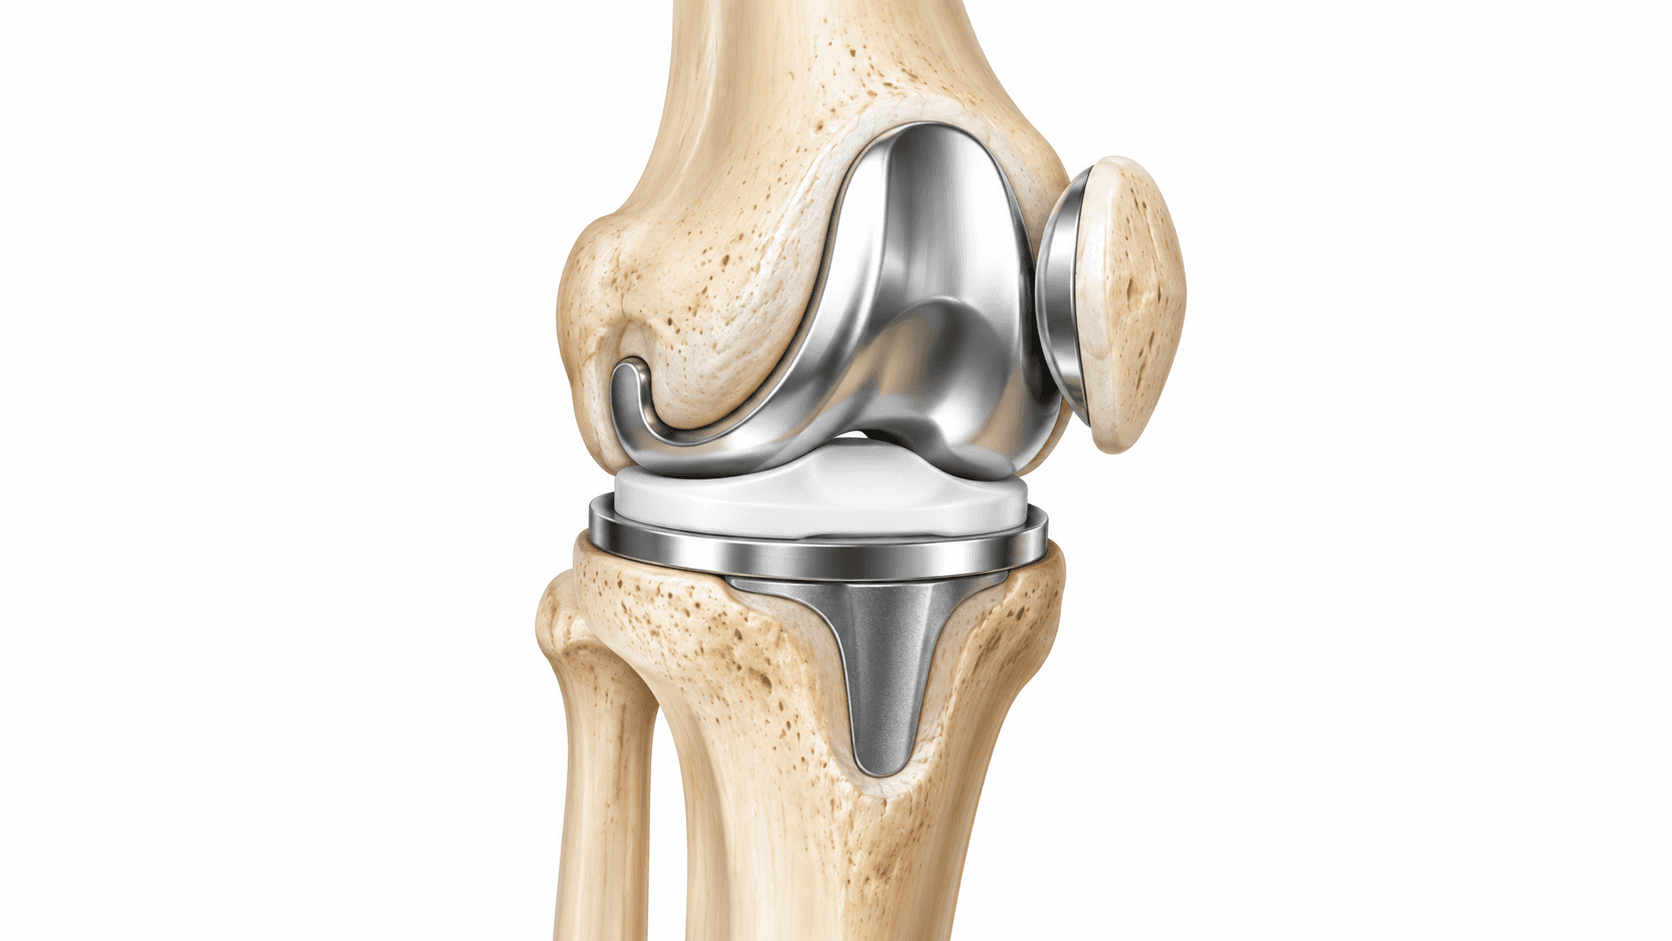
Despite the name, the surgeon does not remove the whole knee. A full knee replacement surgery is better understood as a resurfacing operation. The damaged cartilage and a relatively thin layer of underlying bone are removed from the lower end of the thigh bone, or femur, and the upper surface of the shin bone, or tibia. These prepared surfaces are then covered with specially shaped prosthetic components.
A medical-grade polyethylene insert sits between the metal components and acts as the new smooth bearing surface. Depending on the surgeon's technique and the condition of the joint, the underside of the kneecap may also be resurfaced.
Most of the patient's natural anatomy remains in place. The femur and tibia are not replaced in their entirety. Muscles, tendons, skin, most bone and many of the knee's soft-tissue structures remain part of the reconstructed joint.
The principal objective is to create a stable, well-aligned and functional knee that produces significantly less pain.
What is a total knee replacement?
A total knee replacement treats damage affecting multiple parts of the knee joint.
The knee contains three principal compartments: the medial compartment on the inner side, the lateral compartment on the outer side and the patellofemoral compartment between the kneecap and the femur.
Some patients develop arthritis in only one compartment. These patients may sometimes qualify for partial knee replacement.
Total knee replacement is usually more appropriate when arthritis involves multiple compartments, when deformity is substantial or when the joint cannot reliably be reconstructed with a limited replacement.
The most common underlying diagnosis is osteoarthritis.
Osteoarthritis damages the smooth cartilage covering the ends of the bones. As cartilage becomes progressively thinner, the joint loses its low-friction surface. The underlying bone responds by becoming denser and may produce osteophytes or bone spurs. Joint space narrows, movement becomes painful and the knee can become stiff or deformed.
Symptoms often begin with pain during longer periods of walking.
As the disease progresses, patients may experience pain on stairs, difficulty standing from a chair, reduced walking distance, swelling and stiffness after periods of rest.
Advanced disease can cause pain at night or while sitting.
The leg may gradually become bow-legged or knock-kneed.
NHS guidance states that total or partial knee replacement is principally offered when pain and mobility problems have an important impact on everyday life and alternatives are no longer providing enough relief.
What does the surgery achieve?
The operation has several related goals.
First, it removes arthritic surfaces that generate pain during movement and weight bearing.
Second, it restores a smoother artificial articulation between the femur and tibia.
Third, the surgeon attempts to establish appropriate alignment and ligament balance.
Fourth, the operation aims to improve useful motion.
The objective is not to create a knee that necessarily feels exactly as it did when the patient was 20 years old.
Even a technically successful knee replacement can produce some awareness of the prosthetic joint.
Patients can experience clicking from the components, numbness beside the incision, difficulty kneeling, occasional swelling or a feeling that the artificial knee is mechanically different from the opposite natural knee.
These features do not necessarily indicate surgical failure.
Modern patient satisfaction nevertheless appears high. A 2025 study of 1,702 contemporary TKA patients reported satisfaction in 89.7% of participants.
Total knee replacement versus total knee arthroplasty
These terms mean essentially the same thing.
Total knee replacement is the term patients commonly use.
Total knee arthroplasty is the medical terminology used in guidelines and scientific research.
“TKA” is the abbreviation for total knee arthroplasty.
The phrase total knee replacement surgery is therefore interchangeable with TKA in most patient-facing discussions.
Patients also occasionally search for “total knee replacement surgical” information. In medical English, this is more naturally expressed as total knee replacement surgical technique, total knee replacement surgical procedure or simply total knee replacement surgery.
What conditions can require total knee replacement?
Osteoarthritis accounts for the majority of elective replacements.
Other causes include rheumatoid or inflammatory arthritis, post-traumatic arthritis following a fracture or major injury, osteonecrosis, severe joint deformity and selected complex structural disorders.
A previous knee injury can accelerate degeneration.
For example, a serious fracture involving the joint surface may heal but leave uneven cartilage loading. A major ligament injury can alter knee mechanics. Over many years, these changes can lead to post-traumatic arthritis.
Inflammatory arthritis differs from osteoarthritis because an immune-mediated inflammatory process attacks joint structures. Modern disease-modifying medication has reduced the number of patients reaching advanced destructive rheumatoid arthritis, but replacement remains appropriate when irreversible structural damage causes severe symptoms.
Osteonecrosis occurs when part of the bone loses an adequate blood supply. Collapse near the joint surface can eventually produce arthritis severe enough to require replacement.
Whatever the diagnosis, the underlying principle is similar: the natural joint has become sufficiently painful and mechanically compromised that replacing the damaged surfaces offers a better balance of benefit and risk than continuing conservative care.
Who it's for
- Severe knee osteoarthritis
- Persistent symptoms despite conservative treatment
- Pain that significantly restricts walking
- Pain at rest or at night
- Major loss of knee movement
- Progressive bow-leg or knock-knee deformity
- Inflammatory arthritis with irreversible joint destruction
- Post-traumatic arthritis
Good candidates
Good candidates for total knee replacement have more than an abnormal X-ray.
Their knee disease has a meaningful effect on their life.
A patient may be considered when pain limits walking, work, exercise, sleep or normal independence and when reasonable non-surgical treatment has failed to provide sufficient control.
NHS guidance reflects this approach: knee replacement is generally considered when knee pain has an important impact on everyday life and alternatives have not worked adequately.
X-rays are important, but the decision should not be based on X-rays alone.
Some patients have dramatic radiographic arthritis yet remain functionally active.
Others with similar structural changes experience severe daily pain.
The surgeon therefore evaluates how radiographic disease corresponds with the patient's symptoms and examination.
Pain should also genuinely originate from the knee.
A person can have osteoarthritis on an X-ray but experience substantial pain from the hip, lower spine, peripheral nerves or vascular disease.
Replacing the knee will not reliably resolve pain coming from another anatomical source.
A detailed assessment looks at pain location, duration, swelling, deformity, walking pattern, range of motion and stability.
The clinician also evaluates the hip and neurological function when necessary.
Is there an age limit?
There is no simple upper or lower age threshold.
Historically, surgeons often tried to delay replacement in younger patients because older prostheses had more limited longevity.
Modern implants have improved.
A younger patient with severe arthritis may therefore reasonably undergo replacement if symptoms justify it.
However, younger patients have more years of life in which a prosthesis may eventually wear or loosen, so their lifetime probability of revision is higher.
A 2026 systematic review of patients younger than 50 found substantial functional improvement after TKA but emphasized the importance of longer-term survivorship considerations in younger adults.
Older age by itself is also not a contraindication.
An 80-year-old who remains medically stable and independent may gain enormous quality-of-life improvement from reducing severe arthritic pain.
The decision depends more on general health, frailty, rehabilitation potential and surgical risk than on a birthday alone.
Obesity
Patients with obesity can have successful total knee replacement, but elevated body weight can increase the technical demands of surgery and is associated with several postoperative risks.
A 2026 meta-analysis identified obesity, diabetes, immunosuppressant use, hypoalbuminaemia and systemic inflammatory disease among factors associated with increased periprosthetic joint infection risk after primary TKA.
This does not mean every patient above a particular BMI should automatically be denied surgery.
It means that modifiable risks should be assessed and improved where realistic.
Diabetes
Diabetes is common among patients undergoing joint replacement.
The diagnosis itself does not automatically prevent surgery.
However, poor glycaemic control can increase infection and wound-healing risks.
Preoperative assessment may therefore include HbA1c and a plan for perioperative diabetes medication.
Smoking
Smoking and nicotine exposure can impair tissue perfusion and wound healing.
Stopping before elective surgery is generally advisable and can reduce broader cardiovascular and pulmonary risk as well.
When a patient may need optimization first
Elective total knee replacement may need to be delayed when there is active infection, uncontrolled serious medical disease, unstable cardiovascular status, major untreated skin problems near the operative area or another condition making surgery temporarily unsafe.
Optimization should not be confused with rejection.
Its purpose is to lower preventable risk and improve recovery.
Before surgery
Preparation for total knee replacement surgery begins well before the day of the operation.
The preoperative process has two goals: confirm that replacement is the correct treatment and make surgery as safe as reasonably possible.
Clinical assessment
The surgeon should understand how knee disease affects the patient's life.
Questions commonly cover walking distance, stair use, night pain, swelling, stiffness, instability, work and exercise.
Previous treatments are documented.
These may include physiotherapy, medication, injections, weight management, bracing and walking aids.
The surgeon also asks about previous fractures, ligament injuries, arthroscopy or other operations because old scars and altered anatomy can affect the surgical plan.
Examination
A knee replacement examination evaluates:
standing alignment;
gait;
flexion and extension;
fixed deformity;
ligament stability;
swelling;
tenderness;
patellar movement;
muscle strength.
Skin condition is important.
An infected wound near the knee must be resolved before an elective prosthesis is implanted.
X-rays
Standing knee radiographs are the principal imaging investigation in most straightforward cases.
X-rays can demonstrate loss of joint space, osteophytes, deformity, subchondral sclerosis and bone loss.
Additional alignment radiographs may help the surgeon assess the mechanical axis of the leg.
MRI is generally unnecessary when advanced arthritis is already clear on standard radiographs.
A severely arthritic knee does not require an MRI simply because MRI is a more expensive test.
CT has more specialized uses.
Some robotic systems create a three-dimensional surgical plan from a CT scan. Other systems use intraoperative mapping and require no preoperative CT.
Medical evaluation
Preoperative testing is tailored to the patient.
It may include a full blood count, kidney function, electrolytes, blood group and ECG.
Patients with significant cardiovascular, respiratory or other systemic disease may require specialist assessment.
The team needs to know about:
heart disease;
previous heart attack;
stroke;
hypertension;
diabetes;
kidney disease;
lung disease;
sleep apnoea;
previous blood clots;
bleeding disorders;
medication allergies;
previous anaesthetic complications.
Medication review
Every prescription medication, over-the-counter medication and supplement should be reported.
Particular attention is required for anticoagulants and antiplatelet medication.
Patients should not stop blood thinners themselves.
Stopping anticoagulation can create serious clotting risk, while continuing certain medication through surgery can increase bleeding. The correct plan depends on the drug and the medical reason it was prescribed.
Diabetes medicines may also need modification around fasting and surgery.
Immunosuppressive treatment can require coordination with the patient's specialist.
Infection prevention
Implanting a prosthesis creates particular concern about infection because bacteria can attach to artificial surfaces and become difficult to eradicate.
Any active infection should therefore be evaluated before elective replacement.
Periprosthetic joint infection remains a major cause of revision TKA. A 2025 systematic review of revision causes found infection responsible for approximately 22.3% of documented revision indications, with infection particularly important among early failures. This does not mean 22.3% of all knee replacements become infected; it means infection made up that proportion among the revised knees included in the analysis.
That distinction should remain clear in patient-facing content.
Prehabilitation
Preparation should also include physical preparation.
The patient may be encouraged to perform exercises that strengthen:
quadriceps;
gluteal muscles;
calf;
core.
Prehabilitation does not rebuild worn cartilage.
Its value lies in maintaining physical reserve and teaching the patient exercises that will be needed after surgery.
Learning to use a walker or crutches before the operation can make early rehabilitation less intimidating.
Home preparation
Most patients leave hospital before they are fully recovered.
The home should therefore be prepared in advance.
Trip hazards such as loose rugs can be removed.
Frequently used objects can be moved to accessible heights.
Meals can be prepared in advance.
Patients who live alone should discuss how shopping, laundry, cleaning and transport will be handled during the early recovery period.
A stable chair with armrests is often easier than a low sofa.
The patient's physiotherapist can advise whether a walker, crutches or cane should be available.
Preparing for international treatment
For Orthopedic Abroad, the preoperative process should begin before the patient books the trip whenever possible.
Records useful for a remote surgical assessment include recent standing knee X-rays, medication list, major medical history, previous surgical reports and details of walking ability and symptoms.
Complex previous surgery may require additional imaging.
International patients should understand that final surgical confirmation may still require an in-person examination after arrival.
Travel should therefore be coordinated with a clinical review rather than based entirely on a promotional package.
How the operation is performed
How is total knee replacement surgery performed?
Total knee replacement surgery removes damaged cartilage and a thin layer of bone from the lower femur and upper tibia, prepares those surfaces to receive prosthetic components and places a polyethylene bearing between the new metal surfaces. The surgeon also balances the surrounding ligaments to create a stable knee through its range of motion.
The total knee replacement surgical technique is more complex than simply cutting bone and inserting a prosthesis. Long-term function depends on a combination of component positioning, soft-tissue balance, fixation, patellar mechanics and rehabilitation.
Anaesthesia and positioning
The patient receives either spinal/regional anaesthesia or general anaesthesia according to the agreed plan.
Additional nerve blocks or local infiltration analgesia may be used to improve postoperative pain control.
The patient lies on the operating table with the leg prepared using antiseptic solution and sterile drapes.
A tourniquet may or may not be used depending on surgeon preference and the clinical situation.
Surgical incision
An incision is made over the front of the knee.
The length depends on anatomy, body size, previous scars and the technique being used.
The goal is not to create the smallest possible scar.
A very small incision that compromises visualization or implant positioning is not an advantage.
Entering the joint
The surgeon carefully opens the joint and moves the patella sufficiently to expose the femur and tibia.
Damaged meniscal tissue is removed.
Osteophytes are removed where necessary.
The state of the cruciate ligaments, collateral ligaments and bone is assessed.
Preparing the femur
The distal femur is shaped using cutting guides.
These guides can be conventional mechanical instruments, navigation-assisted systems or robotic technology.
Only the amount of bone required to fit the implant is removed.
The surgeon determines femoral component size and rotation.
Femoral rotation is important because it can influence flexion stability and patellar tracking.
Preparing the tibia
A controlled cut is made across the upper tibia.
Again, the amount removed is relatively limited.
The tibial surface must support the implant without excessive bone removal.
Alignment and rotation are evaluated.
Balancing the knee
Soft-tissue balancing is one of the most important parts of the procedure.
The knee contains ligament structures that stabilize it throughout movement.
If the joint is too tight on one side or too loose on the other, the artificial knee can feel stiff or unstable.
The surgeon therefore evaluates the spaces between the bones in extension and flexion and adjusts the bone cuts, component positioning or surrounding soft tissues as necessary.
Severe bow-legged or knock-kneed deformity can require more extensive balancing.
Trial implants
Temporary components are inserted before the definitive implants.
These trials allow the surgeon to evaluate:
extension;
flexion;
ligament stability;
patellar tracking;
overall alignment;
component size.
Adjustments can be made while the final implants have not yet been fixed.
The patella
The kneecap can be resurfaced or retained.
When it is resurfaced, a small amount of bone is removed from the underside and a polyethylene patellar component is fixed in place.
NICE currently recommends offering patellar resurfacing during primary elective total knee replacement, although international surgical practice remains variable and the evidence includes both clinical and cost-effectiveness considerations.
Implanting the definitive components
The femoral and tibial components are fixed to the bone.
This can be done with bone cement or with cementless porous surfaces designed for biological bone ingrowth.
A polyethylene insert is positioned on the tibial baseplate.
The femoral component glides over the polyethylene surface as the knee bends.
Final assessment
Before closure, the surgeon again checks stability, extension, flexion and patellar tracking.
The wound is irrigated.
Bleeding is controlled.
The joint and soft tissues are closed.
The skin may be closed with sutures, staples, absorbable material or surgical adhesive depending on technique.
A sterile dressing is applied.
How long does the operation take?
A routine primary total knee replacement commonly takes around 1–2 hours.
This does not include all the time the patient spends in the operating department.
Anaesthetic preparation, positioning and recovery add substantially to the total experience.
Complex replacement after previous trauma, severe deformity or previous operations can require longer.
Hospital stay
The hospital stay after primary total knee replacement has shortened considerably with modern enhanced-recovery protocols.
AAHKS states that many patients remain approximately one to three days, although same-day surgery is increasingly possible for appropriately selected patients.
The appropriate discharge time depends on clinical readiness rather than a marketing promise about staying fewer hours.
Immediately after surgery
The patient is transferred to a recovery area.
Staff monitor:
blood pressure;
heart rate;
oxygen;
pain;
nausea;
leg circulation;
neurological function.
The anaesthetic gradually wears off.
Postoperative medication is started.
Early walking
One of the most important changes in modern joint replacement is that patients are no longer routinely confined to bed for several days.
NICE recommends rehabilitation on the day of surgery when possible and no later than 24 hours afterward. Rehabilitation should include mobilization and advice for everyday activities.
A physiotherapist helps the patient stand using a walker or crutches.
The first steps can feel difficult because of pain, swelling and weakness.
This is expected.
Pain control
Pain after total knee replacement can be substantial during the early days.
Modern care uses multimodal analgesia rather than depending on one medication.
Treatment can include local infiltration analgesia, regional blocks, acetaminophen/paracetamol, anti-inflammatory medication where appropriate and limited opioid medication when necessary.
Research comparing nerve-block strategies shows that different regional techniques can influence early postoperative pain and mobility.
Blood-clot prevention
Major lower-limb surgery temporarily raises the risk of deep-vein thrombosis and pulmonary embolism.
Early walking is important.
Medication and mechanical prophylaxis may also be prescribed according to the patient's risk profile.
Discharge
Patients usually need to demonstrate that they can:
stand safely;
walk an appropriate distance;
transfer from bed and chair;
manage stairs when needed;
control pain with oral medication;
eat and drink;
urinate normally;
understand the medication plan.
An international patient may be ready to leave hospital but not yet ready to fly internationally. These are separate decisions.
Recovery
Recovery narrative
The main recovery after total knee replacement occurs over approximately 12 weeks, but improvement frequently continues for six months to one year.
Recovery is not perfectly linear.
Patients often have several good days followed by a more swollen or stiff day after increasing activity.
That does not automatically indicate a complication.
Early recovery involves three processes occurring simultaneously:
the surgical tissues are healing, swelling is resolving and muscles that may have been weak for months or years are being retrained.
Pain and swelling
The knee is usually painful and swollen immediately after surgery.
Swelling can extend down the calf, ankle and foot.
As walking increases, swelling can temporarily increase toward the end of the day.
Over the following weeks it generally decreases.
Some swelling can continue for several months.
Restoring extension
Straightening the knee is an important early rehabilitation objective.
A knee that remains persistently flexed requires more muscular effort during standing and walking.
Patients are therefore encouraged to practise extension exercises according to their rehabilitation plan.
Restoring flexion
Knee bending also improves progressively.
Flexion is needed for sitting, stairs, cycling and other everyday activities.
There is no single flexion angle that every patient must achieve.
Preoperative range of motion, scar tissue, anatomy and rehabilitation all affect the final result.
Walking
Patients generally start using a walker or crutches.
As balance and quadriceps control improve, they may transition to a cane and eventually independent walking.
This should be based on safe gait rather than competition with other patients.
Rehabilitation
NICE states that patients should receive postoperative rehabilitation advice before discharge and should have access to supervised rehabilitation when individual needs require it.
Rehabilitation commonly includes:
knee-extension exercises;
flexion exercises;
quadriceps activation;
hip strengthening;
calf strengthening;
balance work;
walking progression.
Return to ordinary activities
Many people can perform a substantial proportion of ordinary daily activities by around six weeks.
The transition from six to twelve weeks is often when patients begin to feel much more independent.
AAHKS describes return to most activities at approximately three months, with full maximal strength and endurance potentially requiring six to twelve months.
Driving
Driving can resume when the patient can control the vehicle safely, react quickly and perform an emergency stop.
The right knee often requires more recovery than the left because it controls the accelerator and brake in most cars.
Sedating pain medication must also have been stopped.
Return to work
Desk work can often resume earlier than physical occupations.
Heavy manual labour requires stronger muscles, balance and endurance and therefore usually needs a longer rehabilitation period.
The surgeon and rehabilitation team should consider the actual physical demands of the job rather than merely the job title.
Kneeling
Many patients can kneel after healing, but it may feel uncomfortable.
Numbness or tenderness around the scar can make kneeling unpleasant even when the implant is functioning normally.
Sport
Patients are generally encouraged to remain active after replacement.
Walking, swimming, cycling and many recreational activities are compatible with modern TKA.
Repeated high-impact activities such as distance running or frequent jumping are often discouraged because they create higher repetitive forces across the artificial joint.
Recovery timeline
- Stand and begin walking safely1Stand and begin walking safely
Day 0–3
Rehabilitation usually begins on the day of surgery or within 24 hours. The patient learns to stand, walk with a walker or crutches, transfer safely and perform basic exercises. Pain and swelling are expected. Medication and thrombosis prevention begin immediately. Discharge occurs when the patient is medically stable and sufficiently mobile.
- Independent movement around the home2Independent movement around the home
Week 1–2
Walking distance gradually increases. The patient continues exercises aimed at knee extension, flexion and quadriceps activation. Swelling remains common. The surgical wound should progressively heal. Medication, wound-care and blood-clot-prevention instructions must be followed carefully.
- Progress toward a cane or independent walking3Progress toward a cane or independent walking
Weeks 2–6
Patients become more independent with household activities. Walking aids are gradually reduced when gait becomes stable. Flexion and extension continue improving. Pain usually decreases substantially, although swelling and stiffness are still common after exercise or prolonged standing.
- Return toward most normal daily activities4Return toward most normal daily activities
Weeks 6–12
Strength and endurance improve more noticeably. Many patients resume driving and work during this phase once medically cleared. Walking becomes more natural and rehabilitation progresses toward functional strengthening. Some swelling, warmth and stiffness can still occur.
- Improved strength, endurance and recreation5Improved strength, endurance and recreation
Months 3–6
Most patients can perform the majority of ordinary activities with much less awareness of recovery. Walking, cycling, swimming and other low-impact activities can be progressed. Residual stiffness and swelling continue improving.
- Late functional recovery6Late functional recovery
Months 6–12
The replaced knee continues to mature. Maximum strength, confidence and endurance can take up to one year, especially in patients who were severely weak or inactive before surgery. AAHKS notes that full recovery to maximal strength and endurance may take six months to one year.
Outcomes and success rates
Outcomes and success rates
Total knee replacement is designed primarily to reduce arthritic pain and improve function.
Most appropriately selected patients experience substantial improvement.
A contemporary 2025 study reported postoperative satisfaction of 89.7%, suggesting that modern outcomes may be somewhat better than the older frequently repeated estimate that approximately one in five patients is dissatisfied.
That does not mean 90% of patients have a completely normal-feeling knee.
Patient satisfaction and implant survival measure different outcomes.
A patient can have an implant that is mechanically sound but still experience stiffness or difficulty kneeling.
Conversely, another patient may remain highly satisfied despite occasional swelling or mechanical clicking because severe preoperative pain has resolved.
Pain relief
Pain reduction is usually the most important benefit.
The severe bone-on-bone arthritic pain that prevented walking or interrupted sleep typically improves substantially.
The patient then temporarily experiences surgical pain from the operation itself.
Postoperative pain decreases as soft tissues heal and strength returns.
Function
Successful total knee replacement can improve:
walking distance;
stair use;
ability to stand;
sleep;
independence;
recreational activity.
Outcome depends partly on the patient's preoperative condition.
Someone who has been severely deconditioned for several years may require longer rehabilitation than a physically active patient.
How long does a total knee replacement last?
This is one of your most important target queries.
Modern total knee replacements commonly function for decades.
A major systematic review incorporating national joint registries estimated that approximately 82.3% of total knee replacements were still unrevised at 25 years.
Current NHS guidance tells patients that knee replacements can last around 25 years.
The number must be interpreted correctly.
An 82% 25-year survivorship figure means approximately 82% had not undergone revision surgery by 25 years in the registry datasets studied.
It does not mean that 18% suddenly failed exactly at year 25.
Some implants fail earlier.
Many continue functioning longer.
Implant longevity depends on patient age, implant design, activity, fixation, infection, trauma and other factors.
What can cause a replacement to fail?
A 2025 systematic review found periprosthetic joint infection and aseptic loosening to be the most common documented causes of revision. Infection was more prominent among early revisions, while aseptic loosening became more important later.
Other reasons include instability, fracture, polyethylene wear and mechanical problems.
Implants and technology
Total knee replacement usually uses a femoral component, tibial component and polyethylene bearing.
If the patella is resurfaced, an additional polyethylene patellar component is used.
Femoral component
The femoral component covers the prepared lower end of the thigh bone.
It is usually made from a strong metal alloy designed to provide a smooth surface against the polyethylene bearing.
Tibial component
The tibial system commonly contains a metal baseplate fixed to the tibia and a polyethylene insert placed on top.
The plastic insert becomes the principal bearing surface.
Patellar component
If the surgeon resurfaces the kneecap, a polyethylene button is attached to the prepared underside of the patella.
Cemented fixation
Cemented knee replacement uses bone cement to create immediate fixation between the implant and bone.
It has decades of clinical evidence and remains widely used.
Cementless fixation
Cementless knee components use porous surfaces designed for bone to grow onto or into the implant.
Modern cementless designs have generated increasing interest, particularly for younger patients with strong bone.
A 2026 systematic review of registry and large-database studies found that contemporary cementless and cemented TKA generally have relatively small differences in revision outcomes and emphasized limitations in existing registry evidence.
Therefore cementless fixation should not be advertised as universally superior.
Cruciate-retaining implants
Some implants preserve the posterior cruciate ligament.
The prosthesis is designed to function with that remaining ligament.
Posterior-stabilized implants
Other designs remove the posterior cruciate ligament and use implant geometry to reproduce part of its stabilizing function.
Both strategies are established.
The patient's anatomy and surgeon's technique determine which is appropriate.
Robotic total knee replacement
Robotic systems assist the surgeon with planning and execution.
They do not perform surgery independently.
Depending on the system, the technology can help determine:
component size;
bone-cut position;
alignment;
ligament balance;
implant orientation.
Recent evidence shows that robotic-assisted TKA can reduce radiographic alignment outliers and improve precision. A 2026 meta-analysis of 24 randomized trials involving 3,425 patients, however, found no significant overall difference in major WOMAC, functional Knee Society or Oxford Knee Score improvements compared with conventional TKA.
A 2025 meta-analysis of prospective studies similarly found better radiographic precision with robotics, while most clinical differences were small and often not clinically meaningful.
The evidence therefore supports a balanced message:
robotic technology can improve surgical precision, but it does not automatically produce a better-feeling knee.
Computer navigation
Navigation systems give surgeons intraoperative measurements of alignment and component position.
They differ from robotic systems because they may provide measurement and guidance without mechanically constraining cutting instruments.
Personalized alignment
Traditional knee replacement commonly targets mechanical alignment.
Newer approaches include kinematic alignment and functional alignment.
These strategies attempt to reproduce more of the patient's individual anatomy and ligament balance.
Robotic technology has made these approaches easier to quantify.
Early results are promising, but current long-term evidence remains less mature than for conventional established TKA.
Risks and how they are managed
All surgery carries risk. Partner hospitals follow enhanced-recovery and infection-prevention protocols, and your surgeon will discuss the risks specific to your case before consent.
- Infection
- Deep-vein thrombosis
- Pulmonary embolism
- Persistent knee pain
- Stiffness
- Implant loosening
- Instability
- Periprosthetic fracture
- Nerve injury
- Blood-vessel injury
- Wound problems
- Bleeding or haematoma
- Polyethylene wear
- Patellar problems
- Anaesthesia or medical complications
Alternatives
- Exercise and physical therapy
- Weight management
- Pain medication
- Corticosteroid injection
- Walking aids or bracing
- Partial knee replacement
- Osteotomy
- Continued non-surgical treatment
What Knee Replacement costs
The contracted Turkey partner package next to approved self-pay benchmarks. Benchmarks are 20th–80th percentile ranges of approved records, normalised to USD.
Turkey package
$7,500 – $12,500
United States self-pay
$27,150 – $60,150
United Kingdom self-pay
$13,900 – $30,100
Germany self-pay
$11,350 – $29,650
Typical self-pay range by country
Surgeons who perform Knee Replacement
All surgeonsHospitals offering this procedure
Antalya Yaşam Hospital
Private hospital in Muratpaşa, Antalya, with an orthopedics and traumatology department
BHT Clinic Istanbul Tema Hospital
Large private hospital in Atakent, Küçükçekmece, with an orthopedics and traumatology unit
Biruni University Hospital
University hospital in Küçükçekmece, Istanbul, with a published orthopedics and traumatology department
Çankaya Hospital for Orthopedic Care
Çankaya Hospital for Orthopedic Care is an orthopedic hospital in central Ankara with robotic-arm assisted surgery
Sources and references
Peer-reviewed guidance and institutional sources used to write and review this page.
- 01What Is a Knee Replacement?
NHS, 2026
https://www.nhs.uk/tests-and-treatments/knee-replacement/what-is-a-knee-replacement/
- 02Why a Knee Replacement Is Done
NHS, 2026
https://www.nhs.uk/tests-and-treatments/knee-replacement/why-its-done/
- 03Joint Replacement (Primary): Hip, Knee and Shoulder
National Institute for Health and Care Excellence, 2020
https://www.nice.org.uk/guidance/ng157/chapter/Recommendations
- 04Total Knee Replacement
American Association of Hip and Knee Surgeons, 2026
https://www.hipkneeinfo.org/knee-care/total-knee-replacement/
- 05How Long Does a Knee Replacement Last? A Systematic Review and Meta-analysis of Case Series and National Registry Reports
he Lancet / PubMed, 2019
https://pubmed.ncbi.nlm.nih.gov/30782341/
- 06Patient Satisfaction Is Nearly 90% After Total Knee Arthroplasty
Journal of Arthroplasty / PubMed, 2025
https://pubmed.ncbi.nlm.nih.gov/39581239/
- 07Comparative Pain Relief and Functional Outcomes Following Robotic-Assisted Versus Conventional Total Knee Arthroplasty
Peer-reviewed systematic review / PubMed, 2026
https://pubmed.ncbi.nlm.nih.gov/42789133/
- 08Robot-Assisted Total Knee Arthroplasty Demonstrates Superior Radiological but Comparable Clinical Outcomes Compared to Conventional Techniques
Peer-reviewed meta-analysis / PubMed, 2025
https://pubmed.ncbi.nlm.nih.gov/40923445/
- 09A Systematic Review of Registry and Large Database Studies Comparing Contemporary Cementless and Cemented Total Knee Arthroplasty
Journal of Arthroplasty / PubMed, 2026
https://pubmed.ncbi.nlm.nih.gov/42373150/
- 10Why Are Primary Total Knee Arthroplasties Failing? A Systematic Review and Meta-analysis
Journal of Arthroplasty / PubMed, 2025
https://pubmed.ncbi.nlm.nih.gov/40349863/
- 11Popliteal Tendon Impingement as a Cause of Pain Following Total Knee Arthroplasty: A Systematic Review
Peer-reviewed literature / PubMed, 2023
https://pubmed.ncbi.nlm.nih.gov/37661253/