








Key takeaways
- 1Carpal tunnel syndrome happens when the median nerve is squeezed inside the carpal tunnel, a bony and ligament-lined passage on the palm side of the wrist.
- 2The classic picture is tingling or numbness in the thumb, index, middle and half of the ring finger, with the little finger spared.
- 3Symptoms often wake people from sleep, and shaking or flicking the hand usually brings brief relief.
- 4A night splint holding the wrist in a neutral position is the first treatment for most people with mild or moderate carpal tunnel syndrome.
- 5Release surgery cuts the transverse carpal ligament to give the nerve room, and it is usually a day-case operation under local anaesthesia.
- 6Constant numbness, thumb muscle wasting or weakness mean the nerve is under real strain, and a specialist opinion should not be delayed.
- 7Planned carpal tunnel release in turkey can suit patients whose diagnosis is clear and whose records and nerve tests have been reviewed beforehand.
Overview
What is carpal tunnel syndrome?
Carpal tunnel syndrome is a squeezed-nerve problem at the wrist: the median nerve is compressed as it travels through the carpal tunnel, causing numbness, tingling and weakness in part of the hand. This page walks through how it develops, how it is confirmed, the treatments in the order most doctors use them, and how treatment in turkey is organised.
What is carpal tunnel syndrome?
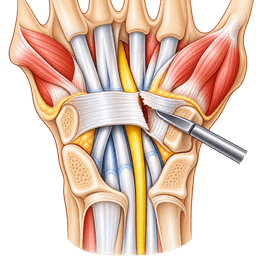
The carpal tunnel is a narrow passage at the base of the palm. Its floor and sides are formed by small wrist bones, and its roof is a strong band called the transverse carpal ligament. Through this tunnel run nine tendons that bend the fingers and thumb, plus the median nerve. There is very little spare room.
Carpal tunnel syndrome appears when pressure inside the tunnel rises, or the tunnel narrows, so the nerve is squeezed. Blood flow to the nerve drops, its signals become unreliable, and the hand starts to tingle, go numb or feel clumsy. Early on the effect is intermittent. With long-standing pressure, the nerve itself can be damaged.
Who gets carpal tunnel syndrome?
It is the most common nerve entrapment in the body. It is seen most often between 40 and 60 years of age, and women are affected roughly three times as often as men, probably because their tunnels are smaller on average. It is also more frequent in pregnancy, in diabetes, in an underactive thyroid and after a wrist fracture.
Many people assume that typing alone is the cause. The evidence for computer work is weaker than most expect. Repetitive forceful gripping and vibrating tools carry stronger links, and a person's anatomy and general health matter at least as much as their job.
How serious is carpal tunnel syndrome?
Most people have mild symptoms that come and go, and a good share improve without an operation. It becomes serious when the nerve is compressed for months or years. Persistent numbness, weakness of the thumb and wasting of the muscle at the thumb base can become permanent if treatment is delayed. That is why a clear plan and timely review matter more than the label.
This guide is educational and cannot replace an examination. If you are unsure what is behind your numb hands, a clinician should test the nerve before treatment is chosen.
Anatomy
What happens in the body with carpal tunnel syndrome
The median nerve is one of the three main nerves of the arm, and it supplies feeling to the thumb side of the palm and to the thumb, index, middle and half of the ring finger. Understanding the tunnel it passes through explains almost every symptom.
What does the normal carpal tunnel look like?
Picture the wrist as a small box. The floor is made of eight small carpal bones arranged in an arch. The roof is the transverse carpal ligament, a firm band about 3 to 4 cm wide that stretches from the bone at the base of the thumb to the bone on the little finger side. Inside the box sit the median nerve and nine flexor tendons, each wrapped in a slippery lining called synovium.
The nerve has two jobs. Its sensory fibres carry touch, pain and temperature from the skin. Its motor fibres power the small muscles at the base of the thumb, which let you pinch and bring the thumb across the palm. A small branch leaves the nerve just before the tunnel to supply the skin over the palm, which is why palm sensation is often normal in the early stage.
What changes in carpal tunnel syndrome?
Anything that thickens the tendon lining, swells the tissue or narrows the bony arch increases pressure. Because the tunnel cannot stretch, even a small rise in volume squeezes the softest structure, which is the nerve. Pressure is highest when the wrist is bent far forwards or backwards, which explains why gripping a phone, driving or sleeping with curled wrists provokes symptoms.
At first the nerve is only starved of blood flow for short spells, so symptoms come and go. Over time the covering of the nerve fibres thins, the nerve loses its normal signal speed and the fibres themselves can degenerate. Doctors can measure that slowing with nerve conduction studies, and it helps decide how urgent treatment is.
The nerve is also sensitive to position at the neck and elbow. A problem higher up the arm can mimic or coexist with carpal tunnel syndrome, which is one reason a careful examination matters before an operation at the wrist is planned.
Symptoms & causes
Carpal tunnel syndrome symptoms and causes
Common symptoms
- Tingling or pins and needles in the thumb, index, middle and half of the ring finger, often described as an electric buzzing that comes and goes during the day.
- Numbness that wakes you at night, so you shake or flick the hand to bring the feeling back; this pattern is typical of carpal tunnel syndrome at night.
- Numb hands at night or on waking in the morning, sometimes with a swollen, heavy feeling in the fingers even when no swelling can be seen.
- Dropping things such as cups, keys or a phone because the grip feels unreliable and the thumb side of the hand is numb.
- Difficulty with fine tasks like doing up buttons, threading a needle or picking up coins, caused by reduced feeling and weaker pinch.
- Pain in the wrist or forearm that sometimes travels up towards the elbow or shoulder, even though the problem is at the wrist.
- Symptoms triggered by holding a phone, steering wheel, book or handlebars, because the wrist stays bent and pressure in the tunnel climbs.
- Weakness of the thumb, with difficulty opening jars or turning keys, which suggests the motor fibres of the median nerve are affected.
- Visible flattening or wasting of the muscle pad at the base of the thumb in long-standing cases, a sign that treatment should not wait.
- Constant numbness rather than on-and-off tingling, which points to a more advanced stage and a nerve under sustained pressure.
Causes and risk factors
- Narrow tunnel by nature: some people are simply born with a smaller carpal tunnel, which is why the condition often runs in families and affects both wrists.
- Female sex and hormonal change: women are affected more often, and symptoms commonly appear around pregnancy or the menopause when fluid balance shifts.
- Pregnancy: fluid retention in the third trimester swells the tunnel contents, and many cases settle within weeks of delivery.
- Diabetes: raised blood sugar thickens connective tissue and makes the nerve more vulnerable to pressure, and recovery after release can be slower.
- Underactive thyroid and rheumatoid arthritis: both can thicken the tendon lining and fill the tunnel with swollen tissue.
- Wrist injury or fracture: a distal radius fracture that heals out of position, or swelling after injury, can narrow the tunnel.
- Repetitive forceful gripping and vibration: long hours with power tools, assembly work or heavy manual tasks raise the risk in some workers.
- Higher body weight and age: both are linked to higher rates, though the reasons are not fully understood.
- Cysts, tumours or thickened tissue inside the tunnel: uncommon, but they should be considered when only one hand is affected and symptoms are unusual.
Types
Types and stages of carpal tunnel syndrome
Doctors group carpal tunnel syndrome by how severe it is and what is behind it, because that decides whether splints are enough or whether the nerve needs to be released.
How is carpal tunnel syndrome graded?
There is no single universal scale, but most specialists describe three practical stages. The stage reflects both what you feel and what nerve tests show.
| Stage | What you notice | Typical nerve findings | Usual approach |
|---|---|---|---|
| Mild | Intermittent tingling, mostly at night or with certain positions; normal strength | Normal or slightly slowed signals | Night splint, activity changes, review at 6 to 8 weeks |
| Moderate | Frequent numbness, night waking, reduced grip and clumsiness | Clearly slowed signals along the median nerve | Splint and injection trial, or release if symptoms persist |
| Severe | Constant numbness, thumb weakness, wasting at the thumb base | Marked slowing or signs of nerve fibre loss | Release surgery is usually advised without a long delay |
What other forms exist?
Doctors also describe the problem by cause. Idiopathic means no clear trigger is found, and this is the most common form. Secondary cases follow a fracture, inflammatory arthritis, thyroid disease or pregnancy. Acute carpal tunnel syndrome is a rare, sudden form after a wrist injury or bleeding into the tunnel, and it needs prompt assessment.
Recurrent carpal tunnel syndrome describes symptoms that return after a previous release. It is far less common than first-time cases, and the cause is worked out carefully before a second operation is planned.
Why does the type change treatment?
Pregnancy-related symptoms usually resolve alone and are treated with splints. Cases linked to thyroid disease or diabetes need the underlying illness treated alongside the wrist. Severe cases with muscle wasting go to surgery sooner, because waiting risks permanent loss of thumb strength.
Diagnosis
How is carpal tunnel syndrome diagnosed?
Carpal tunnel syndrome is mostly diagnosed from your story and a hands-on examination, with nerve tests used when the picture is unclear or surgery is being considered.
What will the doctor ask?
Expect questions about which fingers tingle, when it happens, whether it wakes you and what relieves it. The pattern of thumb, index, middle and half ring finger with the little finger spared is very suggestive. The doctor will also ask about your job, hobbies, past wrist injuries, diabetes, thyroid disease, pregnancy and any neck problems.
How is the hand examined?
The clinician looks for wasting at the thumb base and tests thumb strength and pinch. They check sensation in each finger and compare it with the other hand. Several bedside tests are used. In Tinel's sign, the examiner taps over the nerve at the wrist. In Phalen's test, you hold both wrists bent for up to 60 seconds. In the carpal compression test, firm pressure over the tunnel is held for about 30 seconds. Reproducing your tingling supports the diagnosis, although none of these tests is perfect on its own.
When are nerve tests and imaging needed?
Nerve conduction studies and electromyography measure how quickly signals travel through the median nerve and whether the muscles are losing their supply. They are most helpful when the diagnosis is uncertain, when both the neck and wrist might be involved, or when a previous operation failed. Wrist ultrasound can show swelling of the nerve and is increasingly used. X-rays help if a fracture or arthritis is suspected. MRI is rarely needed.
What should you send for a remote review?
If you are asking a surgeon abroad to look at your case, prepare a short written history, photos of both hands showing the thumb base muscle, any nerve conduction report, wrist X-rays if taken, a list of medicines and a note of diabetes or thyroid results. These let a specialist judge severity before you travel.
Tests you may have
- Tinel's sign: the examiner taps over the median nerve at the wrist; tingling spreading into the fingers supports nerve irritation at the tunnel.
- Phalen's wrist flexion test: holding both wrists bent for up to 60 seconds reproduces numbness in the median nerve fingers when pressure is raised.
- Carpal compression test: sustained thumb pressure over the tunnel for about 30 seconds, often more reliable than Tinel's or Phalen's in practice.
- Nerve conduction studies: electrical measurements showing how fast the median nerve conducts, which grades severity and rules out neck or elbow causes.
- Electromyography (EMG): a fine needle records muscle activity, revealing whether thumb muscles have lost part of their nerve supply.
- Wrist ultrasound: shows swelling or flattening of the median nerve and can reveal cysts or thickened tendon lining inside the tunnel.
- Wrist X-ray: rules out arthritis, an old fracture or a bony prominence that narrows the tunnel.
- Blood tests: blood sugar, thyroid function and inflammatory markers look for medical conditions that make the nerve more vulnerable.
Look-alikes
Conditions that can feel like carpal tunnel syndrome
Which conditions look like carpal tunnel syndrome?
Several problems cause numb or tingling hands, so the first job is to make sure the median nerve at the wrist is really the culprit. The table sets out the main look-alikes and how doctors separate them.
| Look-alike condition | How it differs | How doctors tell |
|---|---|---|
| Cervical radiculopathy (pinched nerve in the neck) | Neck pain, shoulder or arm pain, and symptoms that change with neck movement | Neck examination, Spurling's manoeuvre, nerve studies and neck imaging |
| Cubital tunnel syndrome (ulnar nerve at the elbow) | Tingling in the little and ring fingers rather than the thumb side | Tapping at the elbow, finger sensation map, nerve conduction across the elbow |
| Thoracic outlet syndrome | Whole arm heaviness or tingling, worse with arms overhead | Positional tests, imaging of the shoulder girdle, specialist assessment |
| Peripheral neuropathy | Both hands and often both feet, in a glove-and-stocking pattern | Blood tests, foot examination, widespread nerve conduction changes |
| Thumb base arthritis | Aching at the thumb base with grinding, not true numbness | Pain on the grind test and X-ray changes at the joint |
| De Quervain's tenosynovitis | Pain on the thumb side of the wrist with gripping, no numbness | Finkelstein's test and tenderness over the first tendon compartment |
| Raynaud's phenomenon | Fingers turn white or blue in the cold, with colour change | History of colour change and cold triggers |
Can two problems exist together?
Yes. A nerve can be squeezed in more than one place, a pattern doctors call double crush. Diabetes, neck arthritis and carpal tunnel syndrome frequently overlap. Trigger finger and De Quervain's disease also appear together with it in people who do a lot of gripping. If your numbness does not follow the typical median nerve map, say so clearly before surgery is planned.
You can read about De Quervain's tenosynovitis and trigger finger for comparison, since the three are often confused by patients.
Non-surgical
Non-surgical treatment for carpal tunnel syndrome
Most people with mild or moderate carpal tunnel syndrome should try non-surgical care first, and many improve enough to avoid an operation. The steps below follow the order most hand specialists use.
What does a carpal tunnel splint do?
A carpal tunnel splint holds the wrist in a neutral, straight position so the tunnel stays as roomy as possible. Worn at night, it stops the wrist curling under the pillow or into the chest, which is when pressure peaks. Studies suggest night splinting improves symptoms in a good share of mild and moderate cases, particularly when started early and worn consistently for at least 6 weeks.
A well-fitting splint should be snug but not tight, should hold the wrist roughly straight and should leave the fingers free. Off-the-shelf splints are fine for most people, and a hand therapist can fit a custom one if needed.
Should you change daily activities?
Avoid prolonged wrist bending, tight pinching and tools that vibrate. Take micro-breaks every 30 to 45 minutes, keep the keyboard and mouse at a height that keeps the wrist level, and switch hands for tasks when you can. These changes will not cure severe cases, but they reduce the daily provocation of the nerve.
Which medicines are used?
Anti-inflammatory tablets (NSAIDs) are often tried, although the evidence that they help the nerve itself is limited. Medicines for nerve pain may be used for short spells in selected patients. Vitamin supplements have not shown a reliable benefit. A doctor will also look for and treat diabetes or thyroid disease, which can change the outlook.
What about a steroid injection?
A corticosteroid injection into the carpal tunnel reduces swelling around the tendons and relieves pressure on the nerve. Trials show it often works better than placebo for several weeks to a few months. Many patients then have symptoms return. It is useful as a trial that also helps confirm the diagnosis, as a bridge for pregnancy symptoms, or when surgery must be delayed. Repeated injections are usually avoided because of the risk of tendon weakening and the lack of a lasting result.
What does hand therapy add?
Nerve and tendon gliding exercises, posture advice and activity pacing are taught by hand therapists. The evidence for these exercises alone is modest, but they are low risk and fit well alongside splinting.
How long should non-surgical treatment last?
For mild or moderate carpal tunnel syndrome, 6 to 12 weeks of splinting and activity change is a reasonable trial. If numbness is constant, thumb weakness is developing or nerve tests show moderate to severe slowing, most surgeons advise moving to release surgery earlier.
Self-care
Exercises and self-care for carpal tunnel syndrome
Self-care for carpal tunnel syndrome centres on respecting wrist position, giving the nerve space to recover and keeping the rest of the arm moving. Check with your doctor or hand therapist before starting any exercises, particularly if numbness is constant or your thumb is weak.
Which habits help most?
- Wear the night splint every night for at least 6 weeks, even when symptoms ease.
- Keep wrists straight when typing, using a phone or holding a book; prop devices on a stand or pillow.
- Loosen your grip on pens, tools and steering wheels; a thicker pen helps.
- Shake out and gently stretch your hands for 30 seconds every half hour of repetitive work.
- Warm the hands before exercises, and avoid sleeping on your hands or with wrists curled.
Which exercises are commonly taught?
Therapists often teach a short sequence of tendon and nerve gliding movements. Start with a straight, open hand, move into a hook fist, then a full fist, then a straight fist, and finish with the thumb out to the side. Move slowly through each position, hold for about 5 seconds and repeat 5 to 10 times, two or three times a day.
A gentle wrist extension stretch can follow. Place the palm on a table with fingers pointing towards you, lean back lightly until you feel a mild stretch and hold for 15 to 30 seconds. Stop if the tingling increases.
How do you progress safely?
Increase repetitions slowly over 2 to 3 weeks. Mild tingling during an exercise that settles within a few minutes is acceptable for many people, but numbness that lingers for an hour tells you to scale back. Add light grip work, such as squeezing a soft ball, only once night symptoms have clearly improved.
What should you avoid?
Avoid forceful repeated gripping, long periods of wrist flexion, heavy lifting on bent wrists and resting your wrists on a hard desk edge. Do not rely on tight wrist braces during the day for heavy work, as they can restrict movement and sometimes increase pressure. Check wearing times with your clinician.
Which lifestyle factors matter?
Good blood sugar control in diabetes, treating an underactive thyroid and gradual weight management all support nerve health. If symptoms started in pregnancy, expect improvement after delivery and keep the night splint on in the meantime.
Check with your doctor or physiotherapist before starting new exercises, and stop any movement that causes sharp pain.
Treatment
Carpal tunnel syndrome treatment options
Carpal tunnel release is the standard operation for carpal tunnel syndrome that has not settled with non-surgical care, and it is one of the most commonly performed hand procedures in the world. The details of the carpal tunnel release procedure are set out on our procedure page, and the turkey pathway for carpal tunnel release explains how it is organised here.
What does carpal tunnel release involve?
The surgeon divides the transverse carpal ligament, which is the roof of the tunnel. Once the ligament is cut, the tunnel is larger and the pressure on the median nerve falls. The ligament heals with a looser scar bridge, so the space remains. The operation takes roughly 10 to 30 minutes and is normally done as a day case, under local anaesthesia with or without sedation.
Open or endoscopic release?
In open release, a small incision of about 2 to 4 cm is made in the palm. In endoscopic release, one or two smaller cuts allow a camera to guide division of the ligament from inside. Both are effective. Endoscopic methods may give a little less scar tenderness and a slightly quicker return to gripping, while open surgery gives a direct view of the nerve and is more widely used. Good evidence shows long-term relief rates are broadly similar.
Who is each approach suitable for?
| Approach | Best suited to | Trade-offs |
|---|---|---|
| Open release | Most patients; revision cases; unclear anatomy; thickened lining that needs clearing | Longer scar, more palm tenderness in the first weeks |
| Endoscopic release | Straightforward cases where a faster return to grip matters | Needs a surgeon experienced in the technique; small risk of incomplete release |
| Steroid injection | Mild to moderate cases, pregnancy, or while waiting for surgery | Relief is often temporary and the problem may return |
What results can you expect?
Most people notice that night symptoms and tingling improve within days to a few weeks. Numbness that has been present for a long time can take months to recover, and in severe cases it may never return fully. Thumb muscle bulk can improve slowly, though it is less predictable.
What are the main risks?
Serious complications are uncommon. They include wound tenderness, scar sensitivity, infection, stiffness, an incomplete release and rarely injury to the nerve or its branches. Some people have temporary grip weakness. Your surgeon should explain these, and how they are reduced, before you agree to an operation. Our carpal tunnel release cost guide explains what a package covers, without hospital-specific figures on this page.
When surgery is considered
Surgery for carpal tunnel syndrome is worth discussing when symptoms persist after a proper trial of non-surgical care, or earlier when nerve damage is already visible. The decision is shared between you and your surgeon.
Which situations point towards release surgery?
- Symptoms that continue after 6 to 12 weeks of consistent splinting, with or without a steroid injection.
- Constant numbness rather than on-and-off tingling.
- Weakness of the thumb, dropping objects or visible wasting at the thumb base.
- Moderate to severe slowing on nerve conduction studies.
- Symptoms that return quickly after each injection.
- Night waking that has caused months of poor sleep and affects work and mood.
When should you see a specialist sooner?
Seek a hand surgeon or neurologist promptly if you have sudden numbness after an injury, if both hands are affected with leg symptoms, if there is neck pain with arm weakness, or if numbness is spreading beyond the median nerve area. These patterns need a different workup before any carpal tunnel operation.
What should you ask your surgeon?
Ask how many releases the surgeon performs each year, whether they would recommend open or endoscopic release in your case and why, what the nerve tests showed, and how likely your numbness is to recover. Ask what the recovery plan is, when you can drive and return to work, and who handles complications after you return home.
Risks are higher and recovery slower in diabetes, in long-standing severe compression and when other nerve problems coexist. Honest counselling about this is part of good care. Our hand and wrist hub lists related conditions and procedures.
Procedures
Procedures that may treat carpal tunnel syndrome
Costs
Carpal tunnel syndrome treatment cost in Turkey
| Procedure | Turkey package | US self-pay | Saving |
|---|---|---|---|
| Carpal Tunnel Release | $1,500 – $2,800 | $7,633 | ~72% |
Packages are contracted partner prices with validity dates; benchmarks are source-backed estimates. Open a cost guide for the full country comparison.
In Turkey
Treating carpal tunnel syndrome in Turkey
Carpal tunnel syndrome treatment in turkey can suit people with a clear diagnosis who want planned surgery, because release is a short, well-established day-case operation. This section explains the pathway, the checks to make and the limits of travelling for it.
When does it make sense?
Travelling for carpal tunnel release is most reasonable when your diagnosis is confirmed, non-surgical care has not worked, you are medically stable and your records can be reviewed beforehand. Because the operation is brief and recovery is mostly at home, it is one of the simpler hand procedures to plan around. Our orthopedics in turkey overview explains how care is organised.
What does the pathway look like?
- Send your history, hand photos and any nerve test report through a free case review.
- A surgeon reviews the records and confirms whether surgery looks suitable and which technique is likely.
- You receive a written plan covering the operation, the stay and follow-up.
- You travel, are examined and have the operation, usually as a day case.
- Wound checks and early movement guidance follow; stitches are normally removed after about 10 to 14 days.
- Remote follow-up continues once you are home, as set out in our follow-up guide.
What should you check before booking?
Confirm that the hospital holds recognised accreditation, that your surgeon is a board-certified orthopedic or hand surgeon, and that they regularly perform carpal tunnel release. Ask who treats complications, how follow-up is arranged and whether your records and operative notes are given to you. Our questions to ask before surgery abroad is a useful checklist.
How long do you need to stay?
Many patients plan a short trip of about 4 to 7 days, covering consultation, surgery and a wound check. Some surgeons advise staying until the dressing is first changed. You should be able to fly once the surgeon is happy with the wound, and keeping the hand raised during the flight reduces swelling. See flying after surgery for general advice.
Where is care available?
Major centres include Istanbul, with other options in other cities. Your coordinator can explain what is practical for your travel route. Costs vary with the technique and hospital, so ask for a written package, and read our cost guide for carpal tunnel release to understand what is usually included.
When should you not travel?
Do not travel if the diagnosis is still uncertain, if your symptoms suggest a neck or other nerve problem, if you have uncontrolled diabetes, or if you cannot arrange safe follow-up at home. If you have sudden severe numbness after an injury, see local emergency care first.
Complications
Complications of carpal tunnel syndrome
Untreated carpal tunnel syndrome can progress to permanent nerve damage, while treatment carries small but real risks. Both sides are worth understanding before you decide.
What happens if carpal tunnel syndrome is left alone?
Mild cases may stay stable for years or even settle, particularly those linked to pregnancy. Persistent compression, however, can lead to constant numbness, loss of fine feeling, weak pinch and wasting of the muscle at the thumb base. The longer the nerve is squeezed, the less likely it is to recover fully after release. Burns and cuts on numb fingertips can also go unnoticed.
What are the risks of splints and injections?
Splints are very safe, but they can irritate skin or restrict the wrist if worn too tightly. Steroid injections may cause short-lived pain flare, skin thinning or paler skin at the site, a temporary rise in blood sugar in diabetes and, rarely, infection or damage to the nerve or a tendon.
What are the risks of release surgery?
Overall, serious problems are uncommon, and most people have a smooth recovery. Possible problems include:
- Scar tenderness or pillar pain at the base of the palm, which usually settles over 3 to 6 months.
- Stiff fingers or reduced grip strength for several weeks, helped by early movement.
- Wound infection or bleeding, which is uncommon and usually treated simply.
- Incomplete release or symptoms that persist or return, sometimes needing further assessment.
- Injury to the median nerve or a small branch, which is rare.
- Complex regional pain syndrome, a rare pain disorder that needs early recognition.
How can you lower the risks?
Choose an experienced surgeon, keep the dressing clean and dry, start finger movement the day after surgery and attend your wound check. Report increasing redness, swelling, fever or new numbness promptly to your surgical team.
Urgent care
When to seek urgent care for carpal tunnel syndrome
- Sudden severe numbness or weakness in the hand after an injury or fracture: seek urgent local emergency care before any travel or planned treatment.
- A hot, red, swollen and increasingly painful wrist or palm, especially with fever after surgery: contact your surgeon or emergency services the same day.
- Rapid loss of grip or a thumb that suddenly cannot move: arrange an urgent specialist assessment within days, not weeks.
- Numbness in both hands together with leg weakness, balance problems or bladder changes: go to emergency care, as this may signal a spinal problem.
- Constant numbness with visible wasting of the thumb base muscle: book a hand specialist review promptly, because delay raises the risk of permanent damage.
- A cold, pale or blue hand with severe pain: seek emergency help immediately, as blood supply may be threatened.
Prevention
How to lower your risk of carpal tunnel syndrome
Carpal tunnel syndrome cannot always be prevented, because anatomy, genes and hormones play a large part, but several habits reduce the strain on the nerve and lower the chance of symptoms flaring.
What reduces your risk?
Keep the wrist close to neutral during work and leisure. Adjust desk height, chair and screen so that the forearms are supported and the wrists are not bent sharply upwards. Use a light touch on the keyboard and mouse. Take regular breaks from repetitive gripping and vibrating tools, and use well-fitting gloves in cold environments, since cold increases stiffness.
Which health measures help?
Good control of diabetes, a treated thyroid and a healthy body weight reduce risk. Stopping smoking improves tissue health and nerve blood supply. If you are pregnant and develop symptoms, a night splint early on may prevent them becoming disruptive.
Can exercise prevent it?
General fitness, shoulder and neck posture work and regular hand stretching are sensible, although the evidence that exercise prevents carpal tunnel syndrome is limited. Think of them as supportive rather than as a strong shield against the problem.
What cannot be prevented?
You cannot change a naturally narrow tunnel, a family tendency or hormonal changes. If you notice night tingling, act early with a night splint and a clinical review. Early treatment protects the nerve better than waiting for constant numbness to appear.
How can you prevent recurrence after treatment?
After release, symptoms rarely return, but the habits above still matter. Keep treating any underlying diabetes or thyroid disease, protect the scar early on, and return to forceful gripping gradually under advice from your therapist. If the same symptoms come back months or years later, have them assessed rather than assuming the cause is identical.
Outlook
Living with carpal tunnel syndrome: outlook and recovery
Most people with carpal tunnel syndrome do well, whether they recover with splints or after release surgery. The speed and completeness of recovery depend mainly on how long and how severely the nerve has been compressed.
What is the natural course?
Mild symptoms often fluctuate. Some people improve with splints and activity changes, and pregnancy-related cases usually resolve after delivery. Others see slow worsening over months to years. Symptoms linked to diabetes or other conditions tend to persist unless the cause is also treated.
What is recovery after release like?
| Time after surgery | What to expect |
|---|---|
| First 48 hours | Keep the hand raised, move the fingers often, keep the dressing dry |
| 1 to 2 weeks | Night tingling usually improves; light daily tasks are possible; stitches come out at about 10 to 14 days |
| 2 to 6 weeks | Scar tenderness settles; many people drive and return to desk work, and grip builds |
| 6 to 12 weeks | Return to heavier manual work; strength approaches the other hand |
| 3 to 12 months | Slow recovery of long-standing numbness and thumb strength in severe cases |
When can you return to work and sport?
Desk workers often return within 1 to 2 weeks. People in heavy manual work or racquet sports usually need 4 to 8 weeks. Follow your surgeon's advice, and build up grip and impact gradually.
What are the long-term results?
Most patients report lasting relief of night symptoms and tingling after release. A smaller number have persistent numbness, usually after long-standing severe compression, and a minority need further assessment for recurrence. Early treatment gives the nerve the best chance to recover, which is why a clear diagnosis and sensible timing are so useful.
Surgeons
Specialists who treat carpal tunnel syndrome
FAQ
Carpal tunnel syndrome: frequently asked questions
What is carpal tunnel syndrome?
What are the first signs of carpal tunnel syndrome?
Can carpal tunnel syndrome go away on its own?
Does a carpal tunnel splint really work?
Why are my hands numb at night?
How long does carpal tunnel release take to heal?
Is carpal tunnel surgery painful?
Can carpal tunnel syndrome come back after surgery?
Is carpal tunnel syndrome surgery in turkey safe?
How long should I stay for carpal tunnel release in turkey?
Who is not suitable for carpal tunnel syndrome treatment in turkey?
Can I drive after carpal tunnel release?
Sources
Sources for this carpal tunnel syndrome guide
Peer-reviewed guidance and institutional sources used to write and review this page.
- 01Carpal Tunnel Syndrome
American Academy of Orthopaedic Surgeons (OrthoInfo), 2023
https://orthoinfo.aaos.org/en/diseases--conditions/carpal-tunnel-syndrome/
- 02
- 03Carpal tunnel syndrome
Mayo Clinic, 2023
https://www.mayoclinic.org/diseases-conditions/carpal-tunnel-syndrome/symptoms-causes/syc-20355603
- 04Carpal Tunnel Syndrome Fact Sheet
National Institute of Neurological Disorders and Stroke, 2023
https://www.ninds.nih.gov/health-information/disorders/carpal-tunnel-syndrome
- 05
- 06Carpal Tunnel Syndrome
American Society for Surgery of the Hand, 2023
https://www.assh.org/handcare/condition/carpal-tunnel-syndrome