Key takeaways
- 1Robotic knee replacement is still performed by an orthopaedic surgeon. The robotic system provides planning, tracking and controlled guidance but does not independently decide where to cut bone or place the implant.
- 2The most consistently demonstrated advantage is precision. Current evidence shows robotic-assisted total knee replacement generally produces more accurate implant positioning and fewer alignment outliers than conventional instrumentation.
- 3Greater technical accuracy does not automatically mean dramatically better patient outcomes. Recent systematic reviews show that pain, function and patient-reported outcomes are often similar between robotic and conventional knee replacement, especially in the short and medium term.
- 4Recovery remains a knee replacement recovery. Patients still need pain control, walking practice, physiotherapy, progressive strengthening and several months of biological and functional recovery.
- 5Robotic technology should support—not replace—surgeon expertise. Correct patient selection, implant choice, soft-tissue balancing, infection prevention, rehabilitation and experienced clinical judgment remain fundamental to the result.
Overview
Robotic knee replacement is a form of knee arthroplasty in which an orthopaedic surgeon uses computer-assisted robotic technology to plan and perform selected parts of knee replacement surgery with high spatial precision.
Despite the name, the operation is not performed by an autonomous robot.
There is no machine standing at the operating table independently deciding which bone to remove or which implant to insert.
The surgeon remains responsible for the procedure from beginning to end.
Robotic technology acts as a sophisticated surgical tool.
Depending on the platform, it can create a three-dimensional representation of the knee, identify anatomical landmarks, calculate alignment, measure soft-tissue tension and help guide bone preparation within boundaries defined by the surgical plan.
The surgeon then evaluates the information and adjusts the plan according to the patient's anatomy.
This ability to combine preoperative or intraoperative planning with real-time measurements is the principal reason robotic-assisted knee replacement has attracted attention.
Traditional knee replacement is already an effective operation.
However, even experienced surgeons must work within very small tolerances when deciding component size, position, rotation, alignment and ligament balance.
Robotic assistance aims to make those steps more reproducible.
Robotic Knee Replacement Is Not a Different Artificial Knee
A common misunderstanding is that a robotic knee replacement involves receiving a “robotic knee.”
It does not.
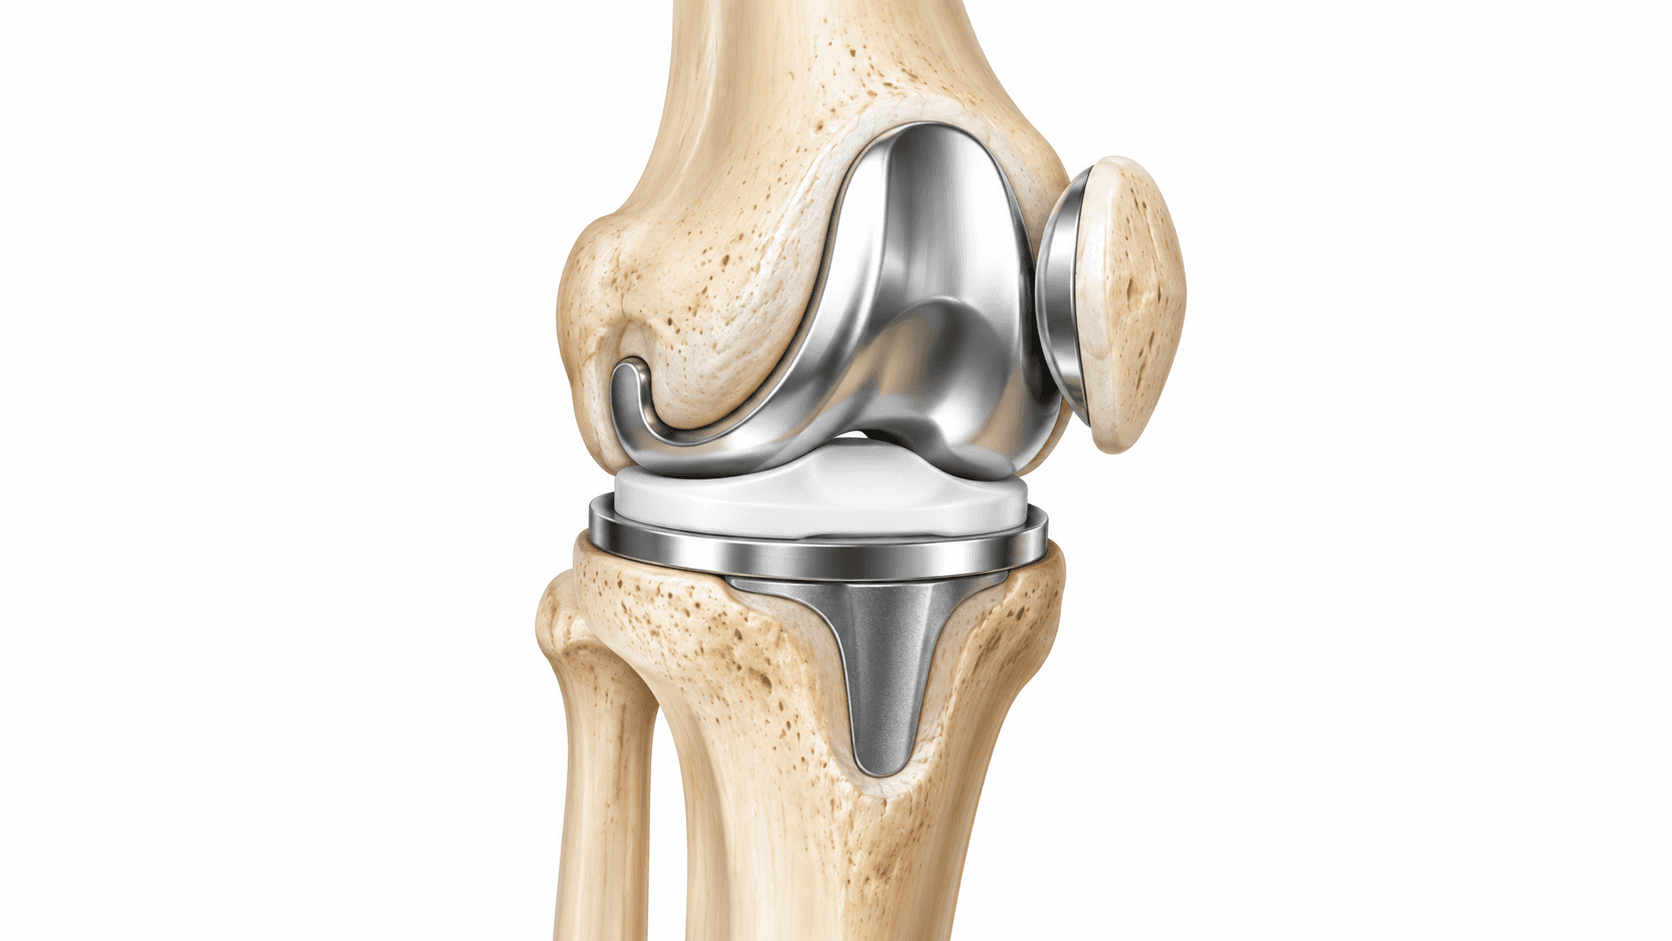
The implant placed inside the body is still an orthopaedic knee prosthesis.
The robot is used to help plan or perform the implantation.
After surgery, there is no robot, battery, motor, computer or electronic mechanism inside the patient's knee.
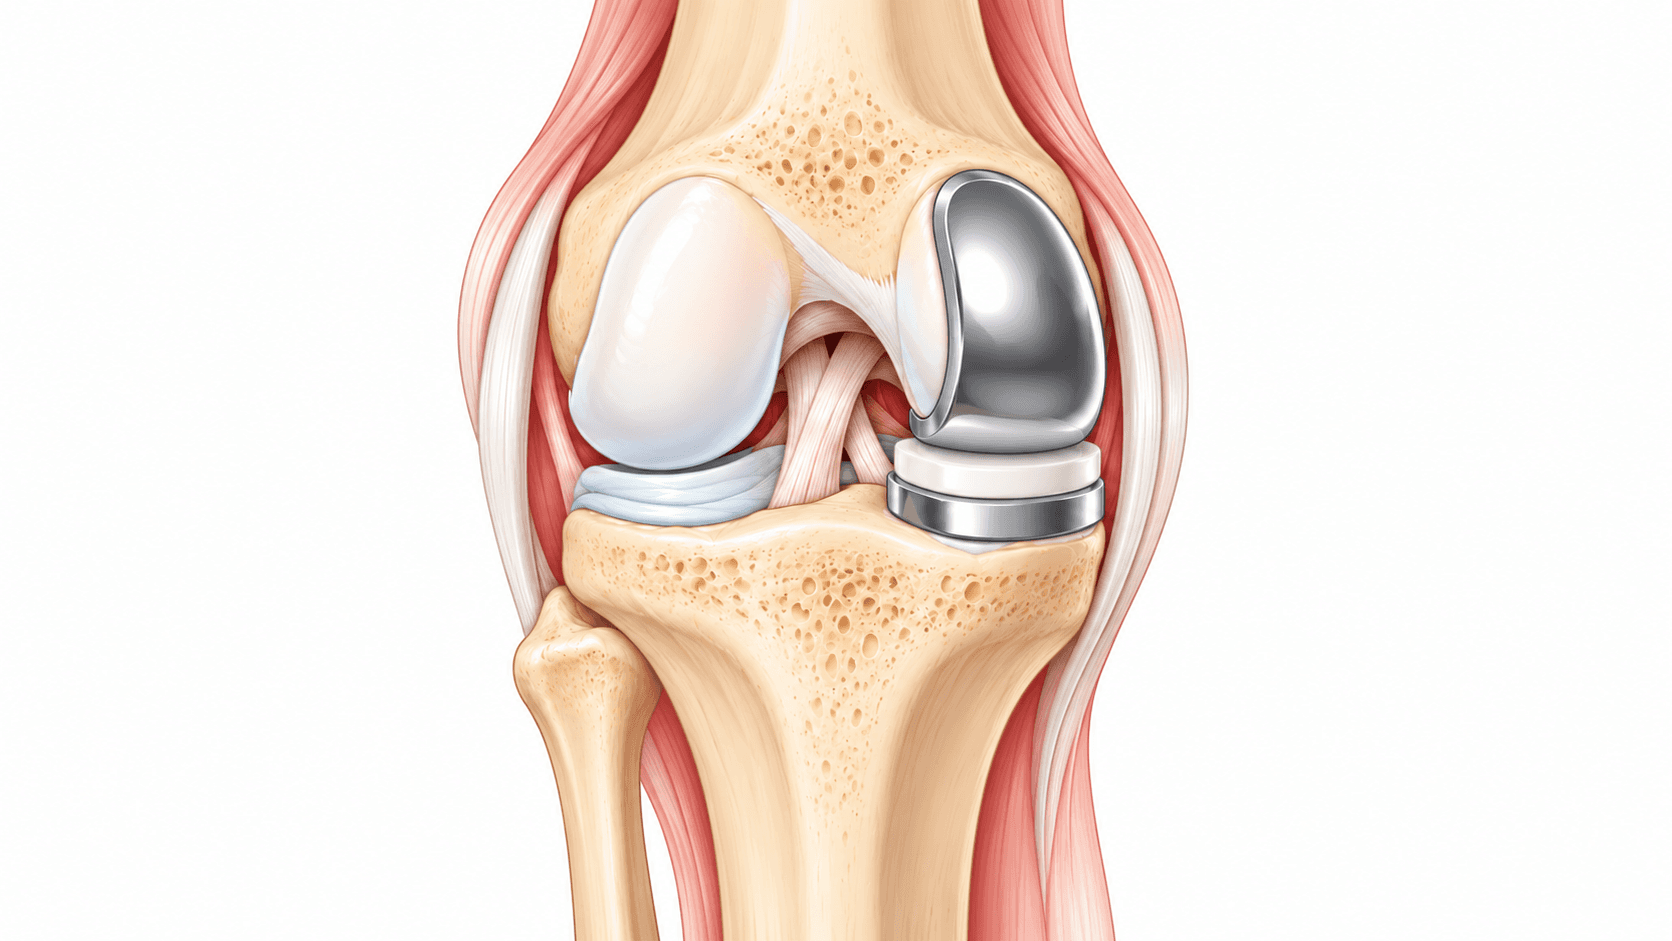
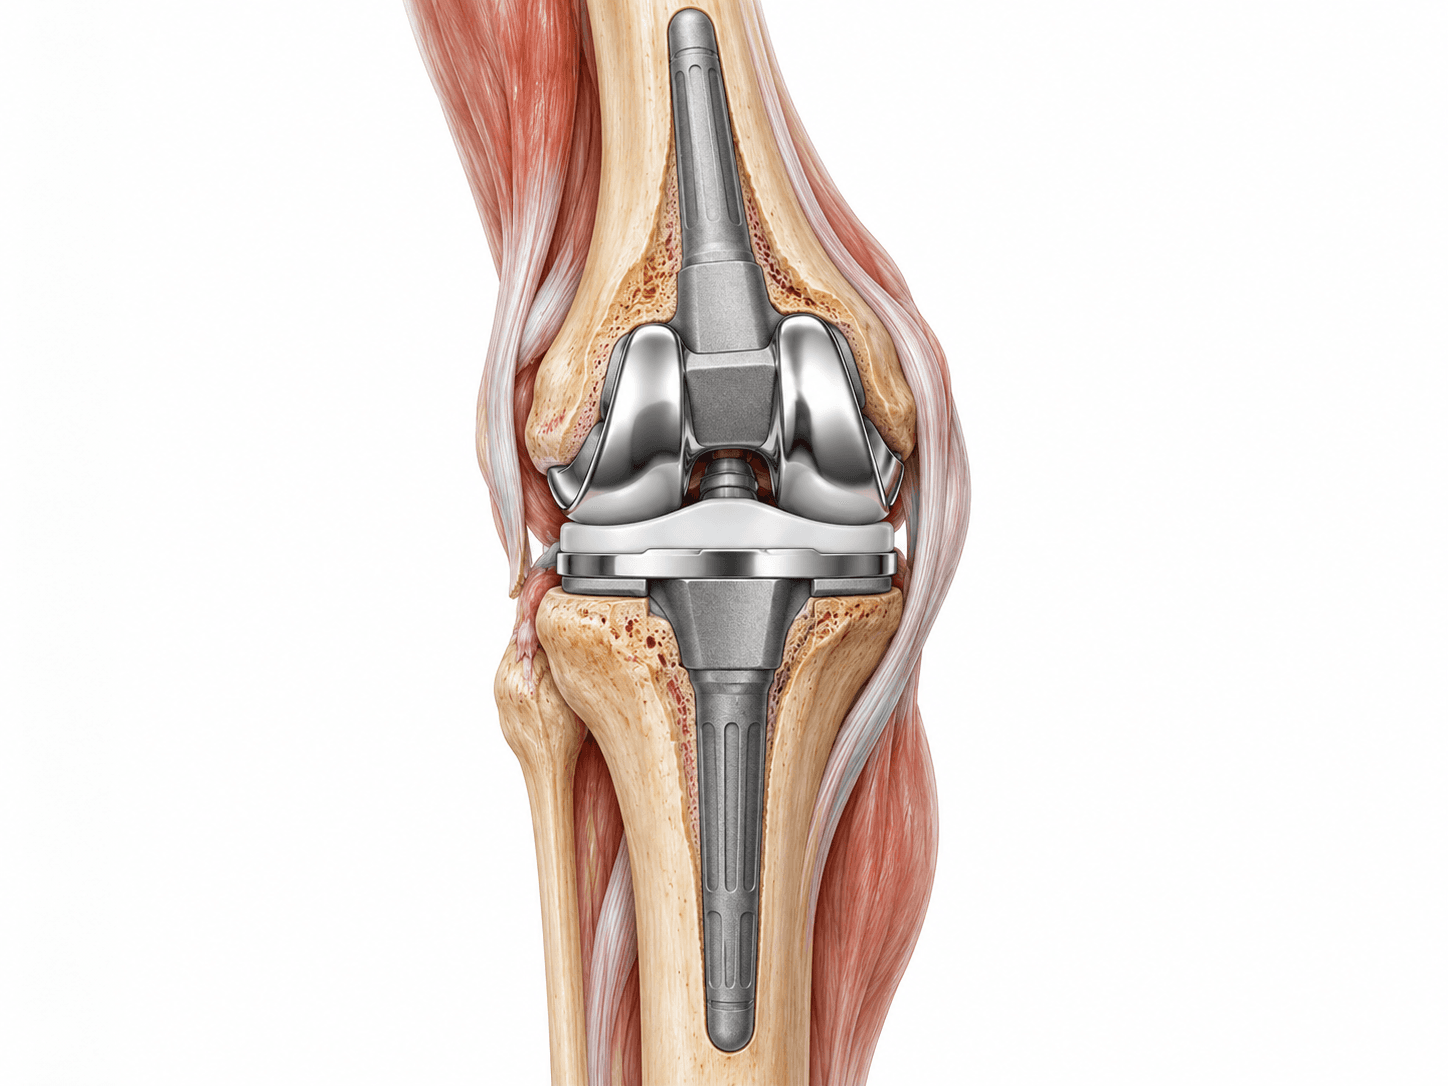
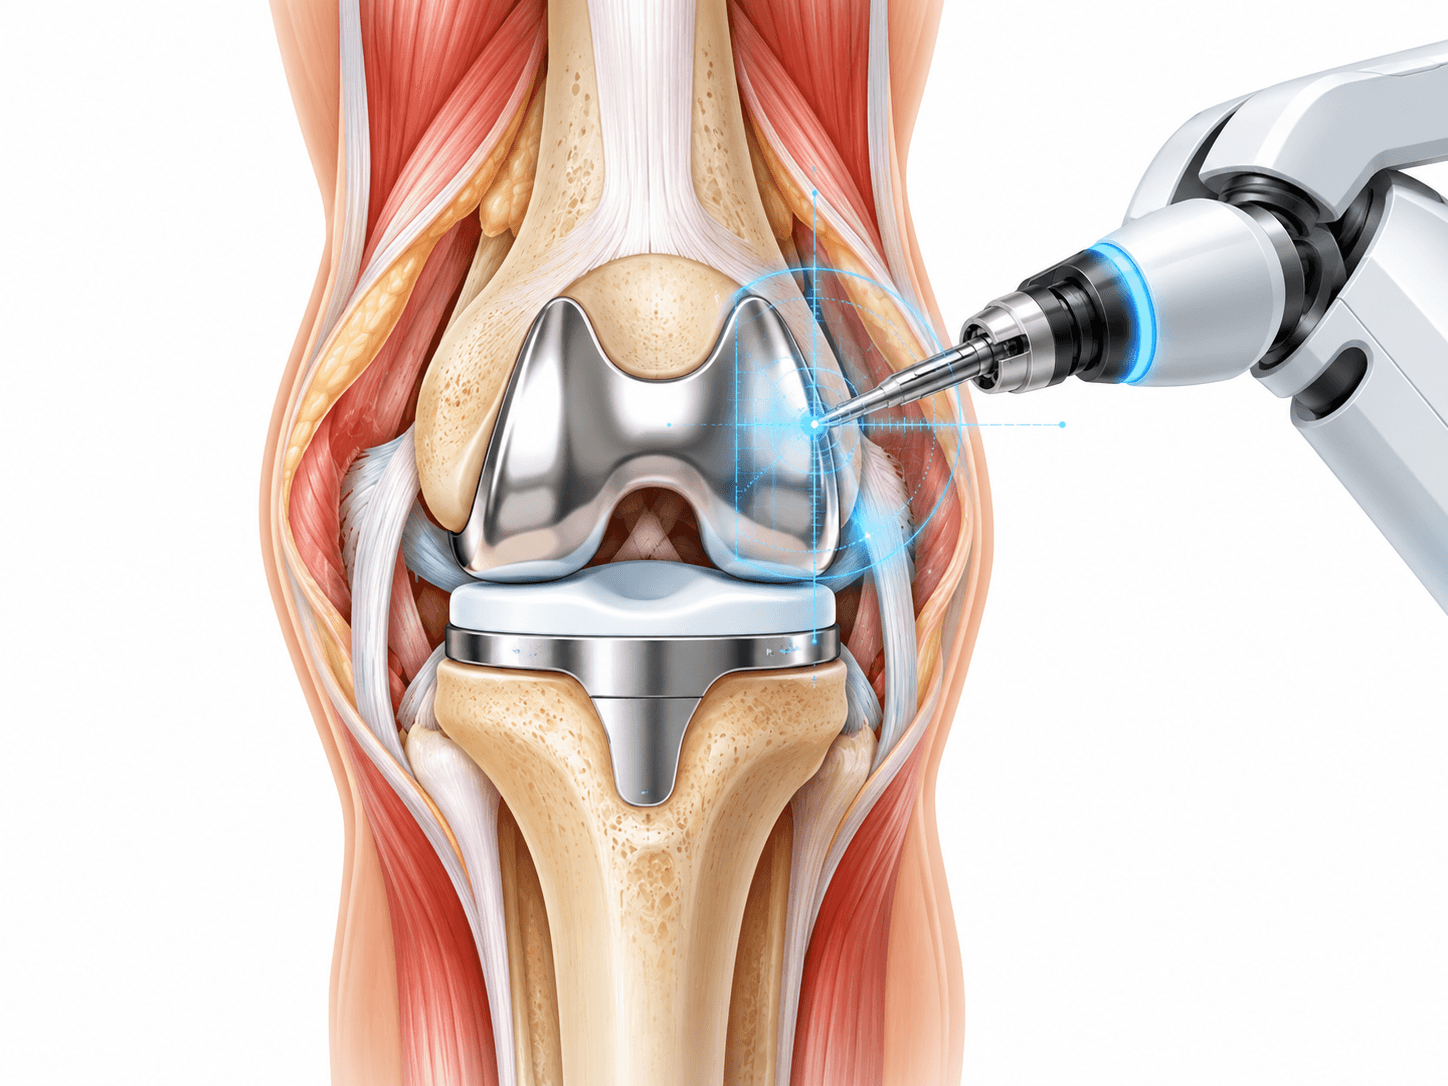
The implanted components are broadly similar to those used during conventional total knee replacement: a femoral component, tibial component and polyethylene bearing, with the patella resurfaced in selected patients depending on the surgical plan and implant philosophy.
The difference is primarily how the surgeon plans and prepares the joint, not whether the patient receives a mechanical robot.
What Is Robotic-Assisted Total Knee Arthroplasty?
The medical term for total knee replacement is total knee arthroplasty, usually abbreviated to TKA.
A robotic-assisted total knee arthroplasty may therefore also be described as RA-TKA, RATKA, robotic TKA or robot-assisted total knee replacement.
During a total knee replacement, damaged joint surfaces at the end of the femur and top of the tibia are reshaped and resurfaced with artificial components.
If the kneecap surface is treated, the patella may also receive a polyethylene component.
Robotic technology helps the surgeon determine how much bone should be removed and where the prosthetic components should sit.
It can also help assess the balance between the inner and outer sides of the knee throughout the arc of movement.
That information can be particularly valuable in knees with significant deformity or complex anatomy.
Why Precision Matters in Knee Replacement
A knee replacement is not simply a matter of putting two metal pieces into a knee.
The components must work together while interacting with the patient's ligaments, muscles and remaining bone.
Small changes in component position can influence how the knee moves.
The surgeon must consider several variables at once.
The tibial component has an angle in the frontal plane, another in the sagittal plane and a rotational orientation.
The femoral component also has coronal, sagittal and rotational positions.
The overall leg alignment matters.
Joint-line height matters.
The amount of bone removed matters.
Ligament tension matters in both extension and flexion.
The knee also needs to remain stable without becoming excessively tight.
Robotic systems are designed to help quantify these factors.
Instead of relying only on fixed mechanical cutting guides, visual inspection and manual measurements, the surgeon can obtain digital information during the procedure.
However, precision must be interpreted carefully.
An X-ray that is one degree closer to a predetermined alignment target does not automatically mean the patient will experience less pain.
Current evidence consistently supports improved radiographic and implant-positioning precision with robotic-assisted surgery, but evidence that these improvements produce major long-term clinical advantages remains less certain.
That distinction is important when explaining robotic surgery responsibly.
Conditions treated
Who it's for
- Severe knee osteoarthritis causing persistent pain and loss of function
- Bone-on-bone arthritis with marked joint-space loss on weight-bearing X-rays
- Pain that limits walking, stairs, work or normal daily activities
- Night pain or pain at rest related to advanced knee arthritis
- Significant knee stiffness that interferes with daily function
- Varus deformity, where the knee becomes progressively bow-legged
- Valgus deformity, where the knee becomes progressively knock-kneed
- Post-traumatic arthritis following a previous fracture or major knee injury
- Osteonecrosis causing substantial destruction of the knee joint
- Selected inflammatory arthritis cases with advanced structural joint damage
- Failure of appropriate nonsurgical treatment, such as physiotherapy, medication, activity modification or injections
- Progressive loss of mobility and independence despite conservative management
- Advanced arthritis affecting multiple knee compartments, making total knee replacement more appropriate than a partial replacement
- Complex knee anatomy or deformity where computer-assisted planning may help the surgeon reproduce the intended implant position accurately
- Patients undergoing primary total knee replacement who are suitable for the implant and robotic platform used by the surgical centre
Good candidates
The ideal candidate for robotic knee replacement is usually someone who is already an appropriate candidate for total knee replacement and who is being treated in a centre where the surgical team is experienced with a suitable robotic platform.
A robot should not create an indication for surgery where none existed.
The patient should have radiographically significant joint damage combined with symptoms that meaningfully affect quality of life.
The patient should also understand the purpose of the technology.
Robotic assistance may improve planning and precision.
It does not guarantee a painless knee.
It does not guarantee faster recovery.
It does not guarantee that the implant will last longer.
And it does not replace physiotherapy.
Age and Robotic Knee Replacement
There is no specific minimum or maximum age that defines candidacy for robotic knee replacement.
Age is considered together with symptoms, general health, bone quality, activity, expectations and the severity of arthritis.
An active 55-year-old with end-stage osteoarthritis may be a reasonable candidate.
An 82-year-old with severe pain and acceptable surgical fitness may also be a reasonable candidate.
The important question is whether knee replacement is clinically justified and whether the expected benefits outweigh the risks.
Body Weight
Obesity does not automatically prevent a patient from having knee replacement.
However, higher body weight can increase anaesthetic complexity, wound problems, infection risk and mechanical loads across the implant.
Weight should therefore be considered as part of preoperative optimization.
Robotic technology should not be marketed as a way to eliminate risks related to obesity.
Diabetes
Patients with diabetes can undergo knee replacement, but blood glucose control is important.
Poorly controlled diabetes can increase infection and wound-healing risks.
Preoperative optimization should therefore occur regardless of whether conventional or robotic technology is used.
Previous Knee Surgery
Previous arthroscopy does not usually prevent robotic replacement.
Previous ligament reconstruction, osteotomy, fracture fixation or other major surgery may make planning more complex.
CT-based systems may also need special consideration when substantial metal hardware remains in the limb because metal can create imaging artifacts.
Before surgery
Diagnostic Assessment
The decision to perform robotic knee replacement begins with an orthopaedic assessment rather than with a robot.
The surgeon evaluates the patient's symptoms, knee examination, imaging, overall health and treatment history.
The goal is to confirm that the pain originates primarily from the knee and that joint replacement is appropriate.
This is important because knee pain can occasionally be referred from the hip or spine.
Replacing a knee that is not the true source of the pain will not solve the underlying problem.
X-Rays Before Robotic Knee Replacement
Weight-bearing X-rays remain fundamental.
They help demonstrate the degree and distribution of osteoarthritis.
The surgeon assesses joint-space narrowing, deformity, bone quality and osteophytes.
Long-leg alignment X-rays may also be obtained.
These can show the mechanical relationship between the hip, knee and ankle and help evaluate overall limb alignment.
Different robotic platforms use different imaging workflows.
Some systems require a CT scan.
Others do not.
CT-Based Robotic Knee Replacement
Certain robotic systems create a detailed three-dimensional model using a preoperative CT scan.
The scan is processed to generate a digital representation of the patient's femur and tibia.
The surgeon then uses this model to plan component size, position and orientation.
Mako is a well-known example of a CT-based robotic-assisted system.
A patient-specific plan is created before or during the procedure and matched to the actual anatomy in theatre.
CT-based planning provides detailed three-dimensional bone information.
However, it exposes the patient to additional radiation and creates another imaging step before surgery.
The clinical importance of that trade-off varies between patients and systems.
Imageless Robotic Knee Replacement
Not every robotic knee replacement requires CT imaging.
Some platforms create a digital representation of the knee during surgery.
The surgeon registers anatomical landmarks directly using tracking instruments.
The system then uses those points to model the joint.
Examples of systems using imageless or optional-imaging workflows include CORI, VELYS and certain ROSA workflows.
An imageless system avoids the need for a mandatory preoperative CT scan.
This does not inherently make it better or worse than CT-based robotics.
They are different technological approaches to the same broad goal: improving surgical planning and execution.
Preoperative Medical Assessment
Patients undergo medical evaluation before surgery.
The exact tests depend on age, health and hospital protocol.
Blood tests usually assess factors such as haemoglobin, kidney function, glucose and electrolytes.
An ECG may be required.
Some patients need cardiology or respiratory assessment.
Anaesthesiology reviews medications, previous anaesthetic experiences and relevant medical conditions.
The team also checks for active infections.
An elective joint replacement should generally not proceed while a patient has an uncontrolled active infection.
Medication Review
Patients should provide a complete medication list.
Blood thinners require particular attention.
Some medications must be stopped or adjusted before surgery, while others should continue.
Diabetes medicines may also require temporary changes around fasting and surgery.
Patients should never independently stop anticoagulants, antiplatelet medications or other important prescription drugs.
The treating team should provide individualized instructions.
Preparing Physically Before Surgery
Better preoperative conditioning can make early rehabilitation easier.
The aim is not to “train away” end-stage arthritis.
Rather, maintaining as much strength and mobility as possible can help the patient after surgery.
Prehabilitation may focus on quadriceps strength, hip strength, walking tolerance and knee movement.
Even a short programme can help patients understand the exercises they will perform after surgery.
Preparing Expectations
Expectation management is particularly important with robotic procedures.
Advertising sometimes creates the impression that robotic knee replacement is almost painless or produces an automatically perfect knee.
That is unrealistic.
The patient still undergoes bone preparation.
The patient still receives artificial components.
The knee still develops postoperative inflammation.
Muscles still become inhibited and weak.
Physiotherapy is still required.
The most defensible benefit of robotics is greater surgical precision and planning capability, not the elimination of normal recovery.
How the operation is performed
How Is Robotic Knee Replacement Done?
Robotic knee replacement combines a standard knee replacement operation with computer-based planning, real-time tracking and a surgeon-controlled robotic system that guides bone preparation and implant positioning.
The exact process varies according to the robotic platform.
However, most systems follow the same general principles.
Step 1: Anaesthesia and Positioning
The patient receives either spinal or general anaesthesia.
Many centres use spinal anaesthesia when clinically appropriate.
Peripheral nerve blocks or periarticular local anaesthetic injections may also be used to reduce postoperative pain.
The patient lies on the operating table with the knee positioned so it can move through a full range during assessment.
The limb is cleaned and covered with sterile drapes.
Step 2: Surgical Exposure
The surgeon makes an incision over the front of the knee.
The joint is carefully exposed.
Although the operation uses robotic technology, the approach still requires surgical access to the knee.
Robotic knee replacement should therefore not be confused with arthroscopic or incision-free surgery.
The extent of the incision depends on anatomy, surgical technique and patient factors.
Step 3: Registration of the Knee
What Is Registration?
The robot needs to understand where the patient's actual bones are located in physical space.
This process is called registration.
Tracking arrays or reference pins are attached temporarily to the femur and tibia.
Special instruments then identify specific anatomical points.
The computer matches these points to either the preoperative 3D model or the model created during surgery.
This creates a coordinate system that allows the technology to track the knee continuously.
Why Tracking Matters
The knee moves during surgery.
The robotic system therefore needs to know the position of the bones at all times.
Optical tracking cameras or other tracking technologies monitor reference markers.
If the leg moves, the system updates the displayed position.
This dynamic tracking is one of the major differences between robotics and static preoperative planning alone.
Step 4: Evaluating Alignment and Ligament Balance
Before final bone preparation, the surgeon moves the knee through different angles.
The system records information about limb alignment and soft-tissue tension.
The surgeon can see how the inner and outer sides of the knee behave in extension, mid-flexion and deeper flexion.
This helps determine whether the planned implant position produces appropriate balance.
What Is Soft-Tissue Balance?
A knee replacement cannot function properly based only on bone alignment.
Ligaments around the knee also need suitable tension.
If one side is excessively tight, the knee can feel stiff or unbalanced.
If the joint is too loose, instability may occur.
Traditional surgeons assess this using experience, manual instruments and spacer blocks.
Robotic systems can add numerical measurements.
Those measurements can help the surgeon adjust component position before cutting bone.
This is one of the potentially valuable aspects of robotic surgery.
Step 5: Creating the Surgical Plan
The system displays a three-dimensional plan.
The surgeon chooses or confirms implant sizes.
The virtual femoral and tibial components can be adjusted.
The surgeon evaluates several variables.
These include component rotation, coronal alignment, tibial slope, joint-line level, bone resection thickness and predicted ligament gaps.
The plan can be modified repeatedly.
This is important because robotic surgery is not simply about following a preset alignment number.
Modern knee replacement increasingly recognizes that anatomy differs between patients.
The surgeon may use mechanical alignment, restricted kinematic alignment, functional alignment or another accepted philosophy according to implant system, patient anatomy and clinical judgment.
The robot allows the chosen strategy to be executed with high reproducibility.
Step 6: Robotic Bone Preparation
Active Versus Semi-Active Systems
Not all robots work in the same way.
Some systems use a robotic arm that constrains the cutting tool within predefined boundaries.
Others position cutting guides.
Handheld systems can control a burr or cutting instrument and stop or restrict it when it approaches the planned boundary.
Most modern orthopaedic robotic platforms are therefore better described as surgeon-controlled or semi-active systems rather than autonomous robots.
Haptic Boundaries
Some robotic arms use haptic technology.
The surgeon physically controls the tool.
However, the robot creates a virtual boundary around the planned bone area.
As the instrument reaches that boundary, movement becomes restricted.
This helps prevent removal of bone outside the planned region.
The principle is similar to an electronic safety zone.
Robotic Cutting Guides
Other systems position or stabilize a saw guide based on the computer plan.
The surgeon then uses the saw through that guide.
The technology's role is to help orient the cutting plane accurately.
Step 7: Removing the Damaged Joint Surfaces
The arthritic surfaces of the femur and tibia are removed according to the surgical plan.
The surgeon checks the bone cuts.
Trial components are then inserted.
The knee is moved through flexion and extension.
The robotic system may provide additional information about alignment and gaps with the trials in place.
Step 8: Trial Implant Assessment
Before final implantation, the surgeon evaluates the knee with temporary trial components.
The surgeon assesses stability in extension and flexion.
Patellar tracking is evaluated.
Range of motion is checked.
The surgeon confirms that there is no problematic impingement.
If necessary, adjustments can be made.
The digital information assists this process, but the final assessment still combines measurements with clinical judgment.
Step 9: Implanting the Final Prosthesis
The definitive components are inserted.
Depending on implant design and patient factors, components may be cemented or cementless.
A metal femoral component resurfaces the distal femur.
A metal tibial tray is placed on the top of the tibia.
A polyethylene insert between the components forms the bearing surface.
The kneecap may or may not be resurfaced.
Robotic technology does not necessarily determine whether patellar resurfacing is performed.
That decision depends on the implant, cartilage condition and surgeon philosophy.
Step 10: Final Robotic Verification
After implantation, alignment and knee stability can be reassessed.
The surgeon confirms range of motion and ligament balance.
The tracking equipment and temporary fixation pins are then removed.
The joint is irrigated and the wound closed.
Dressings are applied.
The patient is transferred to the recovery area.
Types of Robotic Knee Replacement Systems
Mako Robotic Knee Replacement
Mako SmartRobotics is one of the most recognized orthopaedic robotic systems.
For total knee replacement, it uses a preoperative CT scan to create a three-dimensional model.
The surgeon develops a patient-specific plan.
During surgery, the robot helps guide preparation according to that plan using haptic boundaries.
Mako can also be used for selected partial knee and hip replacement procedures.
It is a closed platform, meaning compatible implant choices are linked to the manufacturer's system.
ROSA Knee Replacement
ROSA is another robotic-assisted knee platform.
It is designed for total knee arthroplasty.
The system can use optional preoperative imaging and obtains intraoperative anatomical information.
A robotic arm helps position the cutting guide.
The surgeon performs the bone preparation while the system provides data about alignment and component position.
VELYS Robotic-Assisted Knee Replacement
VELYS is an imageless robotic-assisted platform for total knee replacement.
It uses intraoperative anatomical registration and optical tracking rather than requiring a preoperative CT scan.
The system provides information on alignment and soft-tissue balance.
The robotic-assisted cutting system then helps execute the surgical plan.
CORI Robotic Knee Replacement
CORI is a handheld robotic-assisted platform.
It can be used for total and partial knee arthroplasty with compatible implants.
The system creates a three-dimensional model intraoperatively.
A handheld cutting instrument operates within defined boundaries.
This allows the surgeon to prepare the bone without a mandatory preoperative CT scan.
ApolloKnee
ApolloKnee uses robotic positioning and intraoperative measurements to assist total knee arthroplasty.
Its BalanceBot technology can collect soft-tissue data while the knee moves through different positions.
This information can help the surgeon evaluate balance and component alignment.
SkyWalker Robotic Knee Replacement
SkyWalker is another robotic platform used for joint replacement.
For knee arthroplasty, some configurations rely on preoperative CT imaging and robot-assisted execution of the plan.
Availability varies substantially by country and hospital.
CT-Based vs Imageless Robotic Knee Replacement
Is One Better?
There is currently no universal evidence that every patient should choose CT-based robotics or imageless robotics.
CT systems provide detailed preoperative three-dimensional anatomy.
Imageless systems avoid an additional CT examination and generate their model during surgery.
The most important considerations include the surgeon's experience, implant compatibility, reliability of the workflow and whether the technology offers a meaningful advantage for that patient's anatomy.
Choosing surgery based solely on the robot's brand is rarely a sensible strategy.
Robotic Knee Replacement vs Traditional Knee Replacement
What Is Traditional Knee Replacement?
Conventional total knee replacement uses mechanical instrumentation to guide bone preparation.
Intramedullary or extramedullary alignment guides, cutting blocks and manual measurements help the surgeon position the implants.
Experienced surgeons can obtain excellent results using conventional instrumentation.
Robotic technology therefore does not replace a failed operation.
It adds another method of planning and execution to an already successful procedure.
Accuracy
This is where the evidence is most consistent.
Modern randomized trials and systematic reviews generally show fewer alignment outliers and more reproducible component positioning with robotic-assisted total knee replacement.
A 2025 meta-analysis involving 21 randomized controlled trials found significantly fewer mechanical-alignment outliers with robotic-assisted surgery.
A 2026 meta-analysis of prospective studies similarly reported greater precision in several radiographic measurements.
This is a genuine technical advantage.
The next question is whether it changes outcomes patients actually feel.
Pain and Functional Outcomes
Results are less dramatic here.
Some studies report slightly better early pain scores, range of motion or patient-reported outcomes with robotic surgery.
Other studies find no meaningful difference.
When multiple randomized trials are combined, the clinical differences are generally much smaller than the radiographic differences.
The 2026 prospective-study meta-analysis found some statistically improved clinical measures, but the authors concluded that the differences were not clinically meaningful overall.
This distinction between statistical difference and meaningful patient benefit should be maintained.
Implant Survival
Long-term implant survival is one of the most important questions.
If robotic technology produces more accurate placement, it is reasonable to hypothesize that this could reduce wear or loosening.
However, proving that requires many years of follow-up.
A 2025 systematic review and meta-analysis evaluating implant survivorship found no statistically significant survival advantage for robotic TKA compared with conventional TKA at short, medium or reported ten-year follow-up.
Both approaches showed high implant survival.
Longer-term modern robotic data are still developing.
Operative Time
Robotic surgery often takes longer.
Registration, tracker placement, computer planning and system setup create additional steps.
Several randomized-trial meta-analyses report longer operating times with robotic-assisted TKA.
The difference can decrease as the surgical team gains experience.
Nevertheless, patients should not be told that robotic surgery is inherently faster.
Blood Loss
Some studies show reduced blood loss with robotic assistance.
This may partly relate to differences in instrumentation and reduced use of intramedullary femoral guides.
However, modern blood-conservation protocols have reduced blood loss after both robotic and conventional replacement.
The clinical magnitude of the difference varies between studies.
Hospital Stay
Some studies report slightly shorter hospital stays following robotic replacement.
Hospital length of stay, however, is strongly affected by local protocols.
Enhanced-recovery pathways, physiotherapy, pain control and patient health can influence discharge at least as much as robotic technology.
Complications
Current evidence does not demonstrate a dramatic difference in overall complications.
Some recent analyses suggest lower pooled complication rates with robotics.
Other trials and meta-analyses find similar complication rates.
NICE concluded in its 2025 assessment that adverse events appear uncommon and are unlikely to differ substantially between robotic and conventional surgery, while recommending continued evidence collection.
Is Robotic Knee Replacement Better?
The Most Accurate Answer
Robotic knee replacement is generally more precise than conventional knee replacement in executing planned component position and alignment, but current evidence does not establish that it produces substantially better outcomes for every patient.
That is the most evidence-consistent answer available in 2026.
Robotics has a clear technical value.
The clinical value is likely more complex.
Certain patients may benefit more than others.
For example, technology may be particularly helpful when anatomy is unusual or when a surgeon is trying to reproduce an individualized alignment plan very precisely.
But a patient with straightforward anatomy can also obtain an excellent result with well-performed conventional knee replacement.
The quality of the surgeon and overall treatment pathway remain fundamental.
Hospital stay
Immediately After Surgery
After robotic knee replacement, the patient is transferred to the recovery unit.
Medical staff monitor blood pressure, heart rate, oxygen levels, pain and the surgical dressing.
The leg is examined for circulation and nerve function.
Nausea and anaesthetic side effects are treated when necessary.
Pain control commonly uses several methods rather than relying only on opioids.
This may include acetaminophen or paracetamol, anti-inflammatory medication when safe, local anaesthetic infiltration and nerve blocks.
When Does Walking Start?
Walking usually begins very early.
Many patients stand on the day of surgery.
A physiotherapist or clinical team member assists initially.
A walker or crutches may be used.
Most modern total knee replacements allow weight-bearing as tolerated unless there is a specific surgical reason for restriction.
The goal is safe movement rather than immediately walking without support.
Same-Day Robotic Knee Replacement
Selected patients can undergo knee replacement as day surgery.
Eligibility depends on general health, home support, pain control and mobility.
Robotic technology itself does not make same-day discharge automatically safe.
A healthy patient treated in a strong enhanced-recovery programme may leave the same day after either robotic or conventional surgery.
Another patient may appropriately stay one or two nights.
Recovery
Robotic Knee Replacement Recovery Time
Most patients make their largest early gains during the first 6–12 weeks after robotic knee replacement, but the knee can continue improving for 6–12 months.
Robotic technology does not eliminate the biological recovery associated with total knee replacement.
The tissues around the joint still need to heal.
Swelling still occurs.
The quadriceps still becomes temporarily weak.
Walking mechanics still need retraining.
Recovery depends on much more than implant placement.
Does Robotic Knee Replacement Recover Faster?
Some studies suggest modest early recovery advantages.
These can include slightly less pain, earlier functional milestones or shorter hospital stay.
However, evidence is not uniform.
Patients should not be promised a specific faster recovery simply because a robot is used.
Enhanced-recovery protocols, surgical technique, pain management, preoperative strength and physiotherapy all strongly influence recovery.
Return to Work
Desk Work
Patients with sedentary jobs may return around four to six weeks in many cases.
Some return earlier, particularly when working from home.
Fatigue and difficulty sitting with the leg down for long periods can delay return even when walking is improving.
Physical Employment
Work involving prolonged standing, lifting, climbing or manual labour generally requires longer recovery.
Eight to twelve weeks is common, but some jobs require several months.
Return should be based on functional ability rather than an arbitrary date.
Driving
Driving is usually resumed once the patient can safely enter the car, control the pedals and perform an emergency stop without hesitation.
The patient should no longer be using medication that affects alertness.
Right knee replacement often delays driving longer than left knee surgery in countries where the right foot controls the accelerator and brake.
Many patients resume around four to six weeks, but individual clearance is necessary.
Flying After Robotic Knee Replacement
International patients need specific planning.
Knee replacement temporarily increases the risk of venous thrombosis.
Long flights add prolonged sitting.
The appropriate time to fly depends on the patient's medical risk, flight duration and thrombosis-prevention plan.
A patient should not assume that discharge from hospital means immediate fitness for international air travel.
The surgeon should provide individualized clearance.
Recovery timeline
- Walk safely and control pain and swelling1Walk safely and control pain and swelling
Days 0–7
Walking begins with assistance. The patient performs short, frequent walks rather than one prolonged session. Exercises focus on activating the quadriceps and restoring knee movement. Swelling can be substantial. It is common for bruising and swelling to extend down the leg. Elevation and cold therapy may be used when advised. Full knee extension is an important early target. The patient should follow wound instructions carefully.
- Improve knee movement and reduce dependence on walking aids2Improve knee movement and reduce dependence on walking aids
Weeks 1–3
Physiotherapy progresses steadily. The patient works on straightening and bending the knee. Walking distance increases. Crutches or the walker can be reduced when the patient can walk safely with good control. The goal is not to abandon walking aids as quickly as possible. A symmetrical gait with support is preferable to limping without support. Pain generally decreases but can fluctuate after physiotherapy. Sleep disturbance remains common during early recovery.
- Regain independence in routine daily activities3Regain independence in routine daily activities
Weeks 3–6
Patients generally become more confident moving around the home and community. Strengthening becomes more demanding. Exercises target the quadriceps, hamstrings, gluteal muscles and balance. Many office workers begin considering return to work during this stage depending on commuting requirements and fatigue. The knee can still swell after a busy day. Improvement should be considered over weeks rather than from one day to the next.
- Improve strength, endurance and functional mobility4Improve strength, endurance and functional mobility
Weeks 6–12
This is an important rehabilitation period. Walking becomes more natural. Many patients no longer require a walking aid. Stationary cycling, swimming after complete wound healing and structured gym exercises may be introduced. Stair climbing improves. Patients with physically demanding occupations may still require restrictions. By approximately three months, many patients are substantially better than they were before surgery, although the knee may not yet feel fully recovered.
- Return to broader recreational activity5Return to broader recreational activity
Months 3–6
Strength and endurance continue improving. Longer walks become easier. Patients may return to activities such as cycling, swimming, golf and controlled hiking. Some patients report continued stiffness after sitting for a long period. Others notice mild swelling after demanding exercise. These symptoms can continue improving.
- Reach mature functional recovery6Reach mature functional recovery
Months 6–12
The rate of improvement slows but does not necessarily stop. Muscle strength, confidence and awareness of the artificial knee can continue changing for a year. Many patients eventually think about the knee much less frequently during normal activities. However, a joint replacement does not become a natural biological knee. Some patients continue to notice numbness around the incision, clicking or mild stiffness.
Outcomes and success rates
Robotic Knee Replacement Accuracy
Accuracy is the area where robotic systems show their strongest evidence.
A large 2025 randomized-trial meta-analysis found substantially fewer mechanical-alignment outliers with robotic-assisted surgery.
A 2026 meta-analysis of prospective studies again found better coronal alignment, joint-line restoration and several component-position measurements.
This supports the claim that robotic technology can improve the surgeon's ability to reproduce the intended plan.
It does not justify claiming guaranteed superiority in pain or satisfaction.
Robotic Knee Replacement Success Rate
There is no medically useful single “robotic knee replacement success rate.”
Success can mean different things.
It can mean implant survival.
It can mean pain improvement.
It can mean avoiding revision.
It can mean being able to walk without support.
It can mean returning to golf.
Modern total knee replacement generally produces substantial pain relief and improved function for most appropriately selected patients.
Robotic assistance appears to maintain those strong overall results while improving surgical precision.
The magnitude of any additional clinical benefit is still being investigated.
Implant Survivorship
A 2025 meta-analysis specifically examined survivorship.
At approximately two years, pooled implant survival was very high for both robotic and conventional knee replacement.
No significant difference was detected.
The same analysis found no significant difference in the two-to-five-year period.
Available ten-year data also did not demonstrate a statistically significant survivorship advantage.
These findings do not prove that robotics will never improve longevity.
They show that such a benefit has not yet been convincingly demonstrated.
Joint Awareness
Some patients continue to be aware of their artificial knee despite technically successful surgery.
Researchers use instruments such as the Forgotten Joint Score to study this.
Current comparisons between robotic and conventional TKA do not show a consistently large difference in joint awareness.
Component position is only one contributor to how a knee feels.
Pain sensitivity, soft-tissue balance, muscle function, preoperative expectations and rehabilitation also matter.
Alignment Philosophies in Robotic Knee Replacement
Mechanical Alignment
Traditional mechanical alignment generally aims to place the reconstructed limb around a neutral mechanical axis.
It has decades of clinical experience behind it.
Robotic systems can execute mechanical alignment accurately.
Kinematic Alignment
Kinematic alignment aims to reproduce aspects of the patient's pre-arthritic joint lines and natural knee anatomy.
Robotic systems can help surgeons make small planned adjustments reproducibly.
However, not every patient or implant is suitable for unrestricted kinematic alignment.
Functional Alignment
Functional alignment uses patient anatomy together with intraoperative soft-tissue information.
The surgeon adjusts implant position within accepted boundaries to optimize both alignment and ligament balance.
Robotic technology is particularly compatible with this type of individualized planning because the software can show how changes in component position affect measured gaps.
There remains active debate among orthopaedic surgeons about the best alignment strategy.
The existence of a robot does not resolve that debate.
The technology allows the chosen strategy to be performed more precisely.
Implants and technology
Is There a Special Robotic Implant?
No universal robotic knee implant exists.
Most robotic platforms are designed to work with particular implant families.
The prosthesis itself consists of established orthopedic materials.
Common components include a cobalt-chromium or other metal femoral component, metal tibial baseplate and polyethylene insert.
Cemented and cementless fixation may both be available depending on the system.
Closed Robotic Platforms
Many robotic systems are closed.
This means the robot is approved for use with specific implants produced by the associated manufacturer.
The surgeon cannot necessarily combine any robot with any implant.
This matters when comparing hospitals.
A hospital advertising a particular robotic platform may therefore also be limiting implant choice to the compatible product range.
That is not necessarily a disadvantage, but patients should understand it.
Cemented vs Cementless Robotic Knee Replacement
Robotic technology can be used with both cemented and compatible cementless knee systems.
Cemented fixation uses polymethylmethacrylate bone cement between the implant and bone.
Cementless implants rely on press-fit stability and porous surfaces designed to encourage bone growth.
Robotics may help optimize component positioning for either method.
It does not establish that cementless fixation is better for every patient.
Age, activity, bone quality, implant system and surgeon experience influence the decision.
Risks and how they are managed
All surgery carries risk. Partner hospitals follow enhanced-recovery and infection-prevention protocols, and your surgeon will discuss the risks specific to your case before consent.
- Implant loosening or wear over time
- Dislocation or instability
- Leg-length or alignment difference
- Periprosthetic fracture
- Infection (superficial or deep)
- Blood clots (DVT / pulmonary embolism)
- Bleeding or haematoma
- Anaesthetic complications
- Nerve or blood-vessel injury near the operative site
- Persistent pain or stiffness
Alternatives
- Activity modification and weight management
- Physiotherapy and strengthening
- Anti-inflammatory medication
- Corticosteroid or hyaluronic acid injections
- Bracing or walking aids
- Total Knee Replacement in selected cases
- Partial Knee Replacement in selected cases
What robotic knee replacement costs
The contracted Turkey partner package next to approved self-pay benchmarks. Benchmarks are 20th–80th percentile ranges of approved records, normalised to USD.
Turkey package
$9,500 – $15,000
United States self-pay
$41,950 – $71,750
Typical self-pay range by country
Surgeons who perform robotic knee replacement
All surgeonsHospitals offering this procedure
Antalya Yaşam Hospital
Private hospital in Muratpaşa, Antalya, with an orthopedics and traumatology department
BHT Clinic Istanbul Tema Hospital
Large private hospital in Atakent, Küçükçekmece, with an orthopedics and traumatology unit
Biruni University Hospital
University hospital in Küçükçekmece, Istanbul, with a published orthopedics and traumatology department
Çankaya Hospital for Orthopedic Care
Çankaya Hospital for Orthopedic Care is an orthopedic hospital in central Ankara with robotic-arm assisted surgery
Sources and references
Peer-reviewed guidance and institutional sources used to write and review this page.
- 01Robot-assisted surgery for orthopaedic procedures: early value assessment
National Institute for Health and Care Excellence, 2025
https://www.nice.org.uk/guidance/HTG743/chapter/1-recommendations
- 02Surgical Management of Osteoarthritis of the Knee Clinical Practice Guideline
American Academy of Orthopaedic Surgeons, 2022
https://www.aaos.org/quality/quality-programs/surgical-management-of-osteoarthritis-of-the-knee/
- 03Robot-assisted total knee arthroplasty demonstrates superior radiological but comparable clinical outcomes compared to conventional techniques
Knee Surgery, Sports Traumatology, Arthroscopy / PubMed, 2026
https://pubmed.ncbi.nlm.nih.gov/40923445/
- 04Robotic-assisted versus conventional total knee arthroplasty: a systematic review and meta-analysis of alignment accuracy and clinical outcomes
International Journal of Surgery / PubMed, 2025
https://pubmed.ncbi.nlm.nih.gov/40110313/
- 05Survivorship in robotic total knee arthroplasty compared with conventional total knee arthroplasty
Systematic review and meta-analysis / PubMed, 2025
https://pubmed.ncbi.nlm.nih.gov/40197345
- 06Evaluating Robotic-Assisted Total Knee Arthroplasty Compared to Conventional Methods
International Journal of Medical Robotics / PubMed, 2025
https://pubmed.ncbi.nlm.nih.gov/40252242/
- 07Robotic-assisted versus conventional total knee arthroplasty: systematic review and meta-analysis of randomized controlled trials
PubMed, 2024
https://pubmed.ncbi.nlm.nih.gov/39382767
- 08Comparison of robotic-assisted total knee arthroplasty: an updated systematic review and meta-analysis
PubMed, 2024
https://pubmed.ncbi.nlm.nih.gov/39052153/