








Key takeaways
- 1Achilles tendon rupture is a tear of the strongest tendon in the body, and it most often strikes active adults between about 30 and 50 years of age.
- 2A sudden snap or a feeling of being kicked in the back of the leg, followed by weak push-off, is the typical story.
- 3A fresh Achilles tendon rupture needs an urgent assessment by a local doctor, ideally within a few days, because early treatment gives the best results.
- 4Both a protective boot with early loading and surgical repair can work well, and the choice depends on age, activity goals, timing and the health of the tendon ends.
- 5Achilles tendon rupture recovery time is long: most people walk normally by about 3 months and return to running or sport between 6 and 12 months.
- 6Rehabilitation matters as much as the treatment itself, so a clear plan with a physiotherapist is part of any good pathway.
- 7Planned treatment of a torn Achilles tendon in turkey can be considered only after urgent local care is complete and your treating team agrees that you are stable to travel.
Overview
What is Achilles tendon rupture?
Achilles tendon rupture is a break in the thick tendon at the back of the ankle, and it takes away much of your ability to push off the ground. If you think you have just torn the tendon, get urgent local care first. This page explains what happens, how it is confirmed, how treatment is chosen, and how treatment in turkey can fit a planned stage later.
What is Achilles tendon rupture?
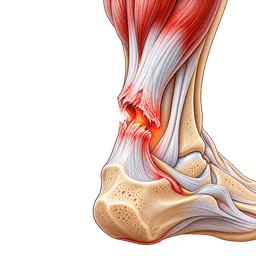
The Achilles tendon joins the two main calf muscles to the heel bone. In an Achilles tendon rupture the fibres of that cord separate, either fully or to a large extent. Most tears happen about 2 to 6 cm above the heel, in a stretch of tendon that has a relatively poor blood supply.
People often describe a pop, a bang or a sensation of being struck from behind. Some turn round expecting to find someone there. The pain can fade surprisingly quickly, which is one reason the injury is sometimes missed on the first day.
Who is affected by Achilles tendon rupture?
The typical patient is a man in his thirties or forties who plays sport only at weekends: football, badminton, tennis or basketball. Men are affected several times more often than women. Tears also occur in older adults during simple activities such as stepping off a kerb, particularly after years of tendon wear.
Certain medicines, including some fluoroquinolone antibiotics and repeated steroid exposure around the tendon, are linked with a higher risk. Previous heel-cord pain (tendinopathy) is another common background.
How serious is a torn Achilles tendon?
A torn Achilles tendon is not dangerous to life, but it is a major injury to function. Without a working tendon, climbing stairs, rising onto your toes and running all become difficult. Treated well, most people regain a strong, useful leg. Treated late or poorly, the tendon can heal long and weak, leaving a lasting limp.
The key message is speed and structure: see a doctor promptly, protect the ankle, and follow a staged rehabilitation plan.
How this page is organised
We start with anatomy and the types of tear, then cover diagnosis, look-alike problems and the two main treatment routes. Later sections explain self-care, when surgery makes sense, how planned care abroad works, and what to expect over the following year. You can also browse the wider foot and ankle hub.
Anatomy
What happens in the body with Achilles tendon rupture
The Achilles tendon is the largest and strongest tendon in the human body, and it transmits the force of the calf muscles to the heel when you walk, run or jump. In an Achilles tendon rupture, that chain of force is cut part-way along its length. Knowing the layout explains why the injury feels so specific.
What is the normal structure of the Achilles tendon?
Two muscles, the gastrocnemius (the visible calf bulge) and the soleus (a deeper, flatter muscle), merge into one tendon about 15 cm long. It runs down the back of the lower leg and attaches to the back of the heel bone (calcaneus). A thin sheath called the paratenon surrounds it and lets it glide.
Behind the tendon sits a small fluid-filled sac, the retrocalcaneal bursa, and the plantaris, a slim tendon that runs alongside and is sometimes mistaken for the Achilles in scans.
What changes in an Achilles tendon rupture?
Under load, the tendon can stretch only a few percent before fibres fail. A fall, a sudden sprint start or a forced landing can exceed that limit, especially if the tendon was already weakened by years of small, unhealed damage. When the ends separate, the calf muscle retracts upward and the gap fills with blood.
Without tension across the gap, the ankle can no longer point the foot downward with full power. That is why walking on the flat of the foot may still be possible while rising onto the toes is not.
Why does the blood supply matter?
The mid-portion of the tendon receives less blood than the ends. Slower healing and age-related change in this zone help to explain why tears cluster there, and why healing needs protection from over-stretching during the early weeks.
Symptoms & causes
Achilles tendon rupture symptoms and causes
Common symptoms
- A sudden snap, pop or "kick" in the back of the ankle at the moment of injury, often with no contact from another person.
- Immediate sharp pain at the back of the lower leg that may settle quickly, which can falsely reassure people that nothing serious happened.
- Swelling and bruising around the heel and lower calf that appear over hours and may spread down into the foot over a few days.
- A noticeable gap or dip that you can feel with a finger in the tendon, about 2 to 6 cm above the heel bone.
- Weakness when pushing off, so that rising onto the toes of the injured leg is impossible or very feeble compared with the other side.
- Difficulty climbing stairs or walking uphill, because the calf can no longer lift your body weight efficiently.
- A flat-footed or limping walk, as the heel cannot lift properly at the end of each step.
- Trouble standing on tiptoe on one leg, which is a quick bedside clue that doctors check for.
- Excessive upward flexing of the ankle compared with the opposite side, because the tight cord no longer holds the joint back.
Causes and risk factors
- Sudden forceful push-off in sport, such as sprinting, jumping or a rapid change of direction, which can overload the tendon in under a second.
- Forced upward bending of the ankle, for example slipping into a hole or landing awkwardly from height, which stretches the tendon beyond its limit.
- Violent upward stretch of a tensed calf, as can happen in a stumble when the foot is planted and the body weight falls forward.
- Pre-existing Achilles tendinopathy, meaning long-standing wear, small tears and thickening of the tendon that leave it weaker than normal.
- Fluoroquinolone antibiotics, which are linked with a higher chance of tendon injury, particularly in older adults and people taking steroids.
- Corticosteroid exposure, either as tablets over a long period or repeated injections near the tendon, which can weaken tendon fibres.
- Being an occasional athlete: sudden bursts of intense effort after long periods of inactivity put tendons under stress they are not prepared for.
- Age between about 30 and 50 years, when sport participation is still high but tendon quality begins to decline.
- Some inflammatory, metabolic or genetic conditions, including gout, diabetes and certain connective tissue disorders, which can affect tendon strength.
Types
Types and stages of Achilles tendon rupture
Doctors classify an Achilles tendon rupture by how much of the tendon has torn, where it has torn and how long ago it happened. These details change the best treatment, so a clear label is more than a technicality. The main groups are described below.
Partial and complete tears
In a partial tear, some fibres remain connected and the tendon may still carry load, so the ankle can sometimes still push off with reduced strength. In a complete Achilles tendon rupture, the ends are separated and push-off is largely lost. Ultrasound or MRI shows which pattern is present.
Location of the tear
- Mid-substance tear: the most common type, usually 2 to 6 cm above the heel.
- Insertional tear: the tendon pulls away from the heel bone, often with a bony fragment, and needs a different anchoring technique.
- Musculotendinous junction tear: where the muscle meets the tendon higher up, usually treated without surgery.
Acute, delayed and chronic tears
An acute tear is seen within about 4 weeks. A neglected or chronic tear is one diagnosed after that window, when the calf has shortened and the gap may be filled by scar. Surgery for a chronic tear can need a tendon transfer, which is more involved than a simple stitch repair.
How are treatment routes grouped?
| Group | Typical features | Usual direction |
|---|---|---|
| Acute complete tear, ends close together | Seen within days, small gap in foot-down position | Boot with early loading or surgical repair |
| Acute tear with wide gap or high demand | Active athlete, ends far apart | Surgical repair often discussed |
| Partial tear | Some push-off retained | Boot and rehabilitation |
| Insertional avulsion | Tendon pulled off the heel bone | Surgery with bone anchors |
| Chronic or neglected tear | Seen after 4 to 6 weeks, scar-filled gap | Reconstruction with tendon transfer |
Diagnosis
How is Achilles tendon rupture diagnosed?
Achilles tendon rupture is usually diagnosed by a doctor's examination, and imaging mostly confirms what the hands have already found. Getting the diagnosis right in the first days matters, because roughly a quarter of ruptures are missed or labelled a calf strain at first. Here is how the process works.
What does the doctor ask about?
You will be asked how the injury happened, whether you heard a snap, and how quickly the pain eased. The doctor will also ask about previous heel pain, antibiotics, steroid injections, diabetes and your sport or job. A clear story of a sudden push-off with a bang is strongly suggestive.
How is the Achilles tendon rupture examined?
Examination begins with looking and feeling. A dip in the tendon can often be felt in the first 24 to 48 hours, before swelling hides it. The most useful hands-on check is the Thompson (calf squeeze) test: with you kneeling or lying face down, the doctor squeezes the calf. A healthy tendon makes the foot move downward. In a complete tear, it does not.
Other signs include a lower resting foot position on the injured side and the inability to stand on one toe. A single test is not perfect, so several are combined.
When are scans needed?
Ultrasound is fast, cheap and good at showing the gap and whether the ends touch when the foot points down. MRI helps when the diagnosis is unclear, when the tear is near the heel, or when surgery for a chronic tear is being planned. X-rays do not show tendon but can reveal a bony avulsion.
What should you bring to a remote review?
- The date and mechanism of injury, and the date treatment began.
- Any ultrasound or MRI report and, if possible, the images themselves.
- Photos of the leg showing the foot position at rest.
- A list of medicines, especially antibiotics and steroids, and any conditions such as diabetes.
- Details of the boot or cast used so far and how much weight you are allowed to bear.
Tests you may have
- Thompson (calf squeeze) test, which checks whether squeezing the calf makes the foot point down; a lack of movement strongly suggests a complete tear.
- Palpation for a gap, feeling along the tendon with a finger to detect a dip in the usual 2 to 6 cm zone above the heel.
- Matles test, where the knee is bent to 90 degrees while you lie face down, to see if the injured foot drifts upward compared with the other side.
- Ultrasound scan, a quick dynamic test that shows fibre loss, the size of the gap and whether the ends come together when the foot is pointed down.
- MRI scan, which provides a detailed map of the tendon, useful for partial tears, insertional injuries and delayed presentations.
- Plain X-rays, which do not show the tendon but rule out an ankle fracture or a bone fragment pulled off the heel.
- Single-leg heel-raise check, a functional test in which the injured side cannot lift the body weight onto the toes.
Look-alikes
Conditions that can feel like Achilles tendon rupture
Several problems can mimic an Achilles tendon rupture, and telling them apart changes both urgency and treatment. The table below summarises the most common look-alikes and how doctors separate them. A sudden snap with loss of push-off should always be examined by a clinician rather than self-diagnosed.
| Look-alike condition | How it differs | How doctors tell |
|---|---|---|
| Calf muscle strain | Pain higher in the muscle belly, usually no snap, toe-rise still possible | Normal Thompson test; ultrasound shows muscle injury only |
| Achilles tendinopathy | Gradual heel-cord pain and thickening over weeks, no sudden loss of strength | Intact tendon on exam and scan |
| Partial Achilles tear | Some push-off kept, pain on loading | Ultrasound or MRI shows continuity of some fibres |
| Plantaris tendon rupture | Sharp inner calf pain, bruising, but push-off preserved | Normal Thompson test; scan shows an intact Achilles |
| Deep vein thrombosis | Calf swelling, warmth and tenderness, often without injury | Doppler ultrasound of the veins; treated as urgent |
| Ankle fracture | Bony tenderness, inability to bear weight, deformity | X-ray shows bone injury |
| Plantar fasciitis | Pain under the heel in the first steps of the day, no sudden event | Tenderness at the heel's underside; normal Thompson test |
Why is a missed tear a problem?
Because the foot can still be moved and walking on the flat is possible, a missed tear is a classic error. The ends then drift apart and scar fills the gap, so a tear that could have been treated with a boot may later need a more complex reconstruction. If you cannot rise on your toes after a snap, ask for a tendon-specific examination.
What about calf clots and other emergencies?
Swelling after a tendon injury is expected, but one-sided calf swelling with warmth and tightness can also signal a clot, particularly once you are immobilised. Any chest pain or breathlessness is an emergency. Doctors keep this in mind throughout care, which is why movement and, in some cases, preventive blood thinners are discussed.
Non-surgical
Non-surgical treatment for Achilles tendon rupture
Non-surgical care is a legitimate first-line choice for many people with an Achilles tendon rupture, and modern protocols give results close to surgery in suitable patients. The idea is to hold the tendon ends close together while they heal, then load the tendon gradually. Here is how the pathway usually runs.
What happens in the first days?
The ankle is placed in a boot or cast with the foot pointing down (equinus), which brings the torn ends together. You use crutches and keep the leg raised to control swelling. Pain is managed with simple analgesics such as paracetamol; many clinicians avoid long courses of anti-inflammatory tablets early on, and your doctor will advise you.
What is the early-loading boot protocol?
Current practice uses a boot with removable heel wedges. Weight-bearing as tolerated often begins within the first 2 weeks. Wedges are removed step by step over roughly 6 to 8 weeks, bringing the foot back to neutral. The boot is usually worn for a total of about 8 to 12 weeks, including during sleep at first.
What does the evidence show?
Large trials suggest that, when early loading is used, the chance of re-rupture after non-surgical care is similar to that after surgery, and strength outcomes are comparable. Surgery tends to carry a slightly lower re-tear rate in some studies but brings its own risks, including wound problems and infection. The best choice depends on the individual.
Who is non-surgical care best for?
- People who are older or less active and mainly need a good walking leg.
- Those with diabetes, smoking history, poor skin or circulation, where wounds heal poorly.
- Patients whose ultrasound shows the tendon ends meeting when the foot points down.
- Anyone who prefers to avoid an operation after an informed discussion.
What does Achilles tendon rupture rehabilitation look like in this route?
Physiotherapy starts while you are still in the boot, with ankle movement within safe limits and strengthening of the hip and knee. Once out of the boot, calf strengthening, balance work and gait retraining take over. Rehabilitation is not optional: a tendon that heals long and loose gives a weak push-off for years.
Self-care
Exercises and self-care for Achilles tendon rupture
Good self-care for a torn Achilles tendon means protecting the repair, keeping the rest of the body strong and following your physiotherapist's timetable closely. Always check with your doctor or physiotherapist before starting or progressing any exercise, because the safe limits depend on your treatment and the stage of healing.
What should you do in the first 2 weeks?
- Keep the leg elevated above heart level for much of the day to reduce swelling.
- Wear the boot exactly as instructed, including at night if told to.
- Move your toes and your hip and knee gently to keep circulation going.
- Learn safe crutch use and stair technique before leaving the clinic.
Which exercises help in the middle phase?
Between about 2 and 8 weeks, your therapist may add seated ankle movements inside the boot, straight leg raises, hip abduction in side-lying and core work. Stationary cycling with the boot off can follow when the team agrees. These keep the quadriceps, hamstrings and hip muscles from wasting.
How does calf strengthening progress?
After the boot is off, a common sequence is: seated double heel raises, standing double heel raises, then eccentric (slow lowering) raises, and finally single-leg heel raises. A target many clinics use is 20 to 25 single-leg raises with good height before running begins, but your own programme should set the numbers.
What should you avoid?
- Stretching the calf aggressively in the first 8 to 12 weeks, which can lengthen the healing tendon.
- Walking barefoot without a heel lift in the early phase.
- Returning to jumping, sprinting or sport before strength and endurance tests are passed.
- Smoking, which slows tendon healing and raises wound complications after surgery.
Which daily habits support healing?
Eat enough protein, keep well hydrated and manage sleep, since tissue repair happens at rest. If you have diabetes, tight glucose control matters for the tendon. Check the skin under the boot every day for pressure marks, and report any calf pain, swelling or breathlessness promptly.
Check with your doctor or physiotherapist before starting new exercises, and stop any movement that causes sharp pain.
Treatment
Achilles tendon rupture treatment options
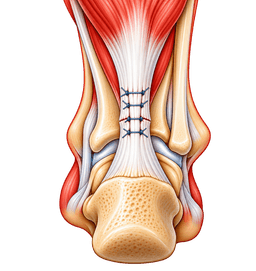
Surgical repair is the main procedural option for an Achilles tendon rupture, and it aims to stitch the torn ends together under controlled tension. It tends to be discussed for active people, large gaps, insertional tears and delayed cases. You can read the full technique on the Achilles tendon repair page.
What does Achilles tendon repair involve?
Under spinal or general anaesthesia, the surgeon makes a cut over the tendon, finds the torn ends and joins them with strong sutures. Open repair gives a clear view and robust fixation. Minimally invasive and percutaneous techniques use smaller cuts and may lower wound problems, though they need careful technique to avoid nerve irritation. Operations commonly take 45 to 90 minutes.
What techniques are used for special situations?
- Insertional avulsion: the tendon is reattached to the heel bone with suture anchors.
- Chronic tear: the gap may be bridged with a turn-down flap or, more often, a transfer of the flexor hallucis longus tendon from the big toe.
- Augmented repair: extra sutures or graft are used when tendon quality is poor.
What are the pros and cons compared with a boot?
| Factor | Boot with early loading | Surgical repair |
|---|---|---|
| Re-rupture | Low with modern protocols | Low, sometimes slightly lower |
| Wound and infection risk | None | Small but real |
| Strength return | Good in most patients | Good, may be somewhat faster in athletes |
| Best for | Older, less active, wound-risk patients | Active people, wide gaps, avulsions, chronic tears |
What happens after the operation?
The leg is placed in a splint or boot for the early weeks. Many surgeons allow protected weight-bearing from 2 weeks, then a gradual wedge reduction. Stitches or clips usually come out at about 2 weeks. Full recovery steps are described in the outlook section and in the rehabilitation guide.
When surgery is considered
Surgery for an Achilles tendon rupture is worth considering when you want the strongest possible push-off, when the tendon ends do not meet, or when the injury is an avulsion or a chronic tear. It is never an emergency in the sense of hours, but a window of roughly 2 to 3 weeks gives the simplest repair.
Which factors favour surgery?
- You play running, jumping or cutting sports and want to return to them.
- Ultrasound shows a wide gap or the ends do not touch in the foot-down position.
- The tendon has pulled off the heel bone.
- The tear is more than 4 to 6 weeks old and push-off remains poor.
- A previous non-surgical treatment has failed or the tendon re-ruptured.
Which factors favour a boot?
Older age, low physical demands, smoking, diabetes with poor circulation, skin problems at the heel and patient preference all tilt toward non-surgical care. A good clinician will lay out both routes without pressure.
What questions should you ask your surgeon?
- How many Achilles repairs do you perform in a typical year?
- Which technique do you propose and why does it suit my tear?
- What is your wound-healing and re-rupture experience, and how will you tell me if problems occur?
- When can I put weight on the leg, and when can I fly?
- Who will supervise my physiotherapy when I return home?
Is a second opinion sensible?
Yes. A tendon rupture is a decision with a trade-off rather than a right and wrong answer. If you are unsure, a records review by another orthopedic team can help you compare options before committing. You can request a free case review at any stage.
Procedures
Procedures that may treat Achilles tendon rupture
Costs
Achilles tendon rupture treatment cost in Turkey
| Procedure | Turkey package | US self-pay | Saving |
|---|---|---|---|
| Achilles Tendon Repair | $3,500 – $6,000 | $19,000 | ~75% |
Packages are contracted partner prices with validity dates; benchmarks are source-backed estimates. Open a cost guide for the full country comparison.
In Turkey
Treating Achilles tendon rupture in Turkey
Treatment of Achilles tendon rupture in turkey can make sense for a planned surgery or a delayed repair, but only after urgent local care has been completed. A fresh tear should be assessed, splinted in the foot-down position and protected where it happened. Travel is considered only once you are medically stable and your treating team agrees.
When does treatment in turkey suit a torn Achilles tendon?
It can suit people whose tear was diagnosed and protected locally, who prefer surgery, and who have time to travel within the repair window of about 2 to 3 weeks. It can also suit patients with a chronic tear who need reconstruction by a team that does tendon transfers regularly. It is not suitable if you are unwell, have a suspected clot, or cannot wear the protective boot safely on a journey.
Many readers ask about Achilles tendon rupture treatment in turkey and Achilles tendon rupture surgery in turkey, so the steps below set out what both involve.
What does the pathway look like?
- Records review: you send your report, scan, photos and medical history through our medical record review process.
- Plan: the surgeon proposes repair or a boot and explains the technique and timing.
- Travel and admission: you arrive, are examined again and have pre-operative checks.
- Surgery and early stay: a short hospital stay is common, followed by several days of local recovery before flying.
- Follow-up: a handover letter, a rehabilitation plan and remote check-ins support care at home.
What should you send for Achilles tendon repair in turkey?
Share the injury date, ultrasound or MRI reports and images, photos of the foot position, your medicines, allergies and conditions such as diabetes, and your height and weight. The more complete the file, the more accurate the plan.
How should you check a team?
- Look for a hospital with recognised accreditation and a foot and ankle service.
- Ask about the surgeon's own volume of Achilles repairs and their approach to complications.
- Confirm how re-operation, wound problems or infection would be handled.
- Ask for a written plan of rehabilitation that your home physiotherapist can follow.
What timing and travel points matter?
Plan to stay in turkey for roughly 7 to 14 days after surgery, depending on wound checks and your surgeon's advice. Read our flying after surgery guide for clot prevention on the flight, and the travel and accommodation page for practical planning. Cities such as Istanbul have large orthopedic centres.
Where can you learn more?
Visit the Achilles tendon repair in turkey page, the cost guide and the wider orthopedics in turkey hub. A free case review is the quickest way to see whether travel is sensible for your tear.
When should you not travel?
Avoid travel if you have signs of a clot, a new wound problem, uncontrolled diabetes or infection, or if your treating clinician has not cleared you to fly. In those situations, local care comes first and planning can wait.
Complications
Complications of Achilles tendon rupture
Complications of an Achilles tendon rupture come from the tear itself, from poor healing, and from treatment. Most people recover without major trouble, but knowing the possibilities helps you spot problems early and make a balanced decision between a boot and surgery.
What happens if a torn Achilles tendon is left untreated?
The tendon ends may heal in a lengthened position or not at all. The calf then weakens and shrinks, push-off drops, and the other leg and the foot arch take extra strain. Many people notice limping, difficulty on stairs and fatigue when walking longer distances. A late reconstruction is possible but is a bigger operation.
What are the risks of non-surgical treatment?
- Re-rupture, which is uncommon with modern early-loading protocols but more likely if the boot is abandoned early.
- A lengthened tendon that leaves a weaker push-off.
- Stiffness or calf wasting if rehabilitation is not followed.
What are the risks of surgery?
- Wound problems, including delayed healing, which are more likely with smoking or diabetes.
- Infection, which is uncommon but can be serious and may need further surgery.
- Irritation of the sural nerve, giving numbness along the outer foot.
- Scar tenderness or a thick, bulky tendon.
- Re-rupture, which is low but not zero.
What are the risks common to both routes?
Deep vein thrombosis is a risk after any lower-limb immobilisation, and pulmonary embolism is its rare but serious complication. Doctors weigh preventive measures against your own risk. Persistent calf weakness of some degree, compared with the uninjured side, is also frequent for a year or more.
How can you reduce the chance of problems?
Stop smoking, control blood sugar, attend every wound check, and follow weight-bearing and wedge instructions to the letter. Report fever, wound discharge, a sudden new pop or calf pain promptly.
Urgent care
When to seek urgent care for Achilles tendon rupture
- Chest pain, sudden breathlessness or coughing up blood after a leg injury or flight: call emergency services at once, because this may be a clot in the lung.
- A swollen, hot, tender calf, particularly on the injured side: seek same-day medical assessment for a possible deep vein thrombosis.
- Fever, spreading redness, pus or a wound that opens after surgery: contact your surgical team the same day, as this can signal infection.
- A new pop, sudden pain or loss of push-off during rehabilitation: stop loading and arrange an urgent review for a possible re-rupture.
- Numb, cold, pale or blue toes, or severe pain under the cast or boot: loosen the dressing if allowed and get urgent help, since circulation may be compromised.
- Inability to rise on your toes after a snap in the heel cord: have it examined by a doctor within 24 to 48 hours, not after weeks.
Prevention
How to lower your risk of Achilles tendon rupture
You cannot prevent every Achilles tendon rupture, but you can lower your risk with smart training, tendon care and awareness of medicines. The focus is on keeping the tendon conditioned and not asking it to do sudden, maximal work when it is cold or unprepared.
How can you condition the tendon?
Regular calf strengthening, particularly slow heavy heel raises, makes tendon tissue more resilient. Aim for a gradual build over 6 to 12 weeks rather than sudden jumps. Include calf flexibility work and balance training if you play sport.
What training habits help?
- Warm up for 10 minutes before explosive sport, including light jogging and dynamic calf movements.
- Increase running distance or intensity by small steps, roughly 10% per week.
- Rest if heel-cord pain lingers for more than 2 weeks, and have it checked.
- Replace worn shoes and avoid sudden changes in surface or footwear.
Which medicines need caution?
Fluoroquinolone antibiotics carry a tendon warning. If you are prescribed one and develop heel or calf pain, stop heavy activity and call your doctor promptly. Avoid repeated steroid injections near the tendon unless a specialist has advised them.
What cannot be prevented?
Some tears occur in healthy tendons during a freak movement, and age-related tendon change is beyond control. Prevention reduces odds; it never removes them. If you have had one tear, protect the other side too, as the risk in the opposite tendon is higher than in the general population.
How does general health factor in?
Healthy body weight, good blood sugar control, not smoking and treating gout all support tendon quality. These steps help the whole musculoskeletal system as well, including conditions covered in the chronic ankle instability guide.
Outlook
Living with Achilles tendon rupture: outlook and recovery
The outlook after an Achilles tendon rupture is good for most people, with a typical return to normal walking by about 3 months and sport between 6 and 12 months. Recovery is slow because tendon is a low-blood-flow tissue, so patience and structured rehabilitation decide the final result.
What is the Achilles tendon rupture recovery time?
| Stage | Typical timing | Main aims |
|---|---|---|
| Protection | 0 to 2 weeks | Splint or boot, elevation, crutches |
| Early loading | 2 to 8 weeks | Protected weight-bearing, wedge reduction |
| Boot off, walking | 8 to 12 weeks | Normal gait, range of movement |
| Strengthening | 3 to 6 months | Single-leg heel raises, balance, jogging preparation |
| Return to sport | 6 to 12 months | Running, jumping, sport-specific work |
How good is the final result?
Most people regain good function, and many return to their previous sport. Studies commonly show that some calf strength deficit, often around 10% to 20% compared with the other leg, can persist, though many people do not notice it in everyday life. Results are usually better with early loading, steady rehabilitation and no smoking.
When can you drive and return to work?
Driving after a right-sided tear usually waits until you are out of the boot and can brake safely, often 8 to 12 weeks. Desk work may resume within 2 to 4 weeks with the leg raised, while jobs that need standing or climbing may take 3 to 4 months. Your surgeon will advise.
What about long-term care?
Keep calf strengthening as a habit, increase training sensibly and treat any new heel pain early. The risk of a second tear is low, but a regular programme keeps both tendons healthy. If you recovered after treatment abroad, keep your operative report and rehabilitation plan safely for any future clinician. Read about follow-up after returning home to plan this ahead.
Surgeons
Specialists who treat Achilles tendon rupture
FAQ
Achilles tendon rupture: frequently asked questions
What is the main symptom of Achilles tendon rupture?
Can you walk with a torn Achilles tendon?
How is a rupture of this tendon diagnosed?
Does a torn heel cord need surgery?
How long does Achilles tendon rupture recovery take?
Can an Achilles tendon heal on its own?
How soon should surgery happen after the tear?
What are the risks of Achilles tendon repair?
Can I run again after Achilles tendon rupture?
Is treatment for Achilles tendon rupture in turkey safe?
How long should I stay in turkey after Achilles tendon surgery?
Can I get my Achilles tendon surgery in turkey if my tear is old?
What is a torn Achilles tendon likely to feel like months later?
Sources
Sources for this Achilles tendon rupture guide
Peer-reviewed guidance and institutional sources used to write and review this page.
- 01Achilles Tendon Rupture
American Academy of Orthopaedic Surgeons (OrthoInfo), 2022
https://orthoinfo.aaos.org/en/diseases--conditions/achilles-tendon-rupture/
- 02
- 03Achilles tendon rupture
Mayo Clinic, 2023
https://www.mayoclinic.org/diseases-conditions/achilles-tendon-rupture/symptoms-causes/syc-20353234
- 04Achilles Tendon Rupture
StatPearls (NCBI Bookshelf), 2023
https://www.ncbi.nlm.nih.gov/books/NBK430844/
- 05
- 06Foot and Ankle Conditions
American Orthopaedic Foot and Ankle Society (AOFAS), 2023
https://www.aofas.org/