








Key takeaways
- 1A rotator cuff tear is a break in one or more of the four tendons that steady and move the shoulder, and it ranges from a small fraying to a complete detachment from the bone.
- 2The typical picture is an ache on the outer shoulder, pain at night when lying on that side, and weakness when lifting the arm away from the body.
- 3A sudden tear after a fall or heavy lift in a younger, active person is a different problem from a slow age-related tear and is often repaired early.
- 4Many partial and small tears improve with a structured exercise programme over 3 to 6 months, with or without a steroid injection.
- 5Rotator cuff repair, usually done through keyhole surgery, is considered when strength is lost, pain persists or a recent tear is likely to be repaired well.
- 6A massive rotator cuff tear with arthritis may be better treated with a reverse shoulder replacement than with repair.
- 7Treatment of a rotator cuff tear in turkey can suit planned, non-urgent surgery once scans have been reviewed and general fitness is confirmed.
Overview
What is rotator cuff tear?
A rotator cuff tear is damage to the group of tendons that wrap around the top of the upper arm bone and keep the shoulder stable. The tear can be partial or complete, recent or long-standing. This page explains how a rotator cuff tear develops, how it is diagnosed and treated, and how treatment in turkey is organised.
What is a rotator cuff tear?
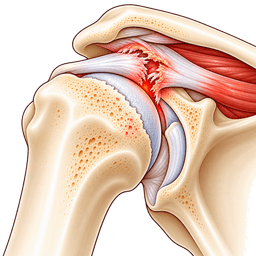
The rotator cuff is a sleeve of four muscles and their tendons. The tendons blend together as they attach to the top of the humerus (upper arm bone). A tear means that part of a tendon has pulled away from its attachment or has split within its substance.
Think of a rope fraying strand by strand. A partial tear leaves some fibres intact. A full-thickness tear passes right through the tendon, leaving a gap between tendon and bone. The edges of a full tear can retract, like a cut rubber band, as the muscle pulls on them.
Who gets a rotator cuff tear?
Tears become more frequent after the age of 50, and by the seventh decade a sizeable minority of people have one, often without realising. Overhead workers such as painters, builders and electricians are at risk, as are swimmers, tennis players and weightlifters. Smokers and people with a close relative who had a tear also seem more prone.
A second group is younger adults who tear the cuff in a single event: a fall on the outstretched arm, a shoulder dislocation, or a heavy lift with a jerk.
How serious is a rotator cuff tear?
A rotator cuff tear is not dangerous to general health, but it can limit sleep, work and independence. A small tear may stay stable for years. A larger one can slowly enlarge, and the muscle can thin and turn fatty, which makes later repair harder. That is why timing and tear size shape the advice you receive.
Pain and weakness do not always match the scan. Some people with a large tear cope well, while others with a small one struggle. Your story and examination guide the plan more than the report alone.
How this page is organised
We move from anatomy and symptoms to causes, tear types, diagnosis and look-alike problems. Next come non-surgical care, self-care exercises, surgical options and the timing of surgery, followed by how treatment abroad works. Complications, prevention, outlook, common questions and sources close the page. For wider context, see our shoulder overview.
Anatomy
What happens in the body with rotator cuff tear
The rotator cuff is made of the supraspinatus, infraspinatus, teres minor and subscapularis muscles, and it keeps the ball of the shoulder pressed into its shallow socket as the arm moves. A cuff tear weakens that steering system. Knowing the layout helps explain why tears hurt in the places they do.
What does the normal shoulder look like?
The shoulder is a ball-and-socket joint. The ball is the head of the humerus. The socket is the glenoid, part of the shoulder blade (scapula), and it is shallow, closer to a golf ball on a tee than a cup. Stability depends on soft tissue far more than on bone shape.
Four cuff tendons surround the ball. The supraspinatus runs over the top and starts lifting the arm. The infraspinatus and teres minor sit at the back and turn the arm outwards. The subscapularis lies at the front and turns it inwards. Together they act like guy ropes on a tent pole.
Above the cuff sits the acromion, a bony roof from the shoulder blade. A thin lubricating pad called the subacromial bursa lies between the roof and the tendon. The long head of the biceps tendon travels through the joint nearby and often becomes sore with a cuff tear.
What changes when the cuff tears?
Once a tendon detaches, the muscle can no longer hold the ball down against the pull of the stronger deltoid. The humeral head may ride upwards and rub on the acromion. Lifting the arm then feels weak, catching or painful in an arc.
Over months, an unrepaired tear may cause the muscle to shrink and fill with fat, a change called fatty infiltration. Retracted tendon edges also become stiff and harder to pull back. This is why surgeons look carefully at muscle quality on MRI before advising repair.
In the longest-standing massive tears, the ball can ride up permanently and the cartilage can wear, leading to rotator cuff tear arthropathy.
Symptoms & causes
Rotator cuff tear symptoms and causes
Common symptoms
- Aching in the outer shoulder and upper arm, often spreading towards the elbow, that rises with reaching or carrying and settles with rest.
- Night pain, especially when lying on the affected side, that wakes you and makes finding a comfortable position difficult.
- Weakness when lifting the arm out to the side or in front, such as struggling to place a cup on a high shelf.
- Difficulty combing hair, fastening a bra or reaching into a back pocket because the arm will not lift or turn easily.
- A catching, clicking or grating feeling on movement, sometimes called crepitus, from the rough tendon edge moving under the bony roof.
- A painful arc, usually between about 60 and 120 degrees of lifting, where pain peaks and then eases as the arm goes higher.
- A sudden tearing sensation or pop after a fall or lift, followed by immediate weakness, which suggests an acute tear.
- Stiffness that develops when you guard the arm, which can resemble frozen shoulder and is worth reporting to your clinician.
- Visible wasting above or below the shoulder blade in long-standing tears, because the unused muscle thins over months.
- Inability to hold the arm out at all, called a drop-arm sign, which points towards a large tear and needs prompt assessment.
Causes and risk factors
- Age-related degeneration: tendon blood supply and quality decline from the 40s onwards, so fibres fray and fail under everyday loads.
- Repetitive overhead activity: years of painting, lifting, swimming or throwing wear the tendon at its attachment.
- Acute injury: a fall onto the arm, a violent pull or a shoulder dislocation can tear a healthy tendon in one event.
- Bone spurs under the acromion: a hooked or spurred roof can rub the tendon, a mechanism linked with <a href='/conditions/shoulder-impingement'>shoulder impingement</a>.
- Smoking: nicotine reduces tendon blood flow and is linked in studies with larger tears and poorer healing.
- Family history: some people appear to inherit weaker tendons, with several relatives developing tears at a similar age.
- Steroid exposure: repeated injections into the same tendon or long-term steroid medicines may weaken tissue.
- Metabolic conditions: diabetes and raised cholesterol are associated with tendon problems and slower healing.
Types
Types and stages of rotator cuff tear
Rotator cuff tears are classified by depth, size, shape, timing and which tendon is involved. These labels matter because they decide whether exercise is likely to be enough or whether repair or replacement should be discussed. Your surgeon will usually describe the tear using several of these terms together.
What is a partial thickness rotator cuff tear?
A partial thickness rotator cuff tear damages only part of the tendon's depth. It may involve the upper (bursal) surface, the lower (articular) surface facing the joint, or run within the tendon. Many partial tears are treated without surgery. If more than about half the thickness is torn, surgeons may consider repair when symptoms persist.
What is a full-thickness tear?
A full-thickness tear passes through the tendon, leaving a gap. Small ones measure under 1 cm, medium tears 1 to 3 cm, large tears 3 to 5 cm, and massive tears over 5 cm or involving two or more tendons. Size is measured on MRI and confirmed during surgery.
What is a massive rotator cuff tear?
A massive rotator cuff tear is a large defect involving more than one tendon. It is not always repairable, because the tendons may be stiff and the muscle replaced by fat. Some people with massive tears function well for years. Others lose active lifting and need advanced options such as a patch, tendon transfer or reverse shoulder replacement.
Acute, chronic and acute-on-chronic tears
An acute tear follows an injury and tends to be painful, weak and a good candidate for early repair because the tissue is healthy. A chronic tear develops slowly and may have been present for years. An acute-on-chronic tear is a sudden injury on top of an already worn tendon, and the plan depends on tissue quality.
| Tear category | Typical description | Common direction of care |
|---|---|---|
| Partial, less than half thickness | Fraying or small split, tendon mostly intact | Exercise, activity changes, sometimes injection |
| Partial, more than half thickness | Deep split, symptoms often persist | Trial of exercise, then consider repair |
| Small to medium full-thickness | Gap under 3 cm, one tendon | Repair if weak or painful, especially if recent |
| Large full-thickness | Gap 3 to 5 cm, may involve two tendons | Repair if muscle quality allows |
| Massive, irreparable | More than 5 cm, retracted, fatty muscle | Specialist options including reverse replacement |
Diagnosis
How is rotator cuff tear diagnosed?
A cuff tear is diagnosed by combining your story, a hands-on shoulder examination and imaging, usually ultrasound or MRI. No single test is perfect, so clinicians look for agreement between them. This approach avoids treating a scan finding that is not actually causing your pain.
What will the doctor ask?
Expect questions about when the pain began, whether a fall or lift started it, which movements hurt, and how nights are going. You will be asked about your hand dominance, job and sport, because these set the demands on the repair. Smoking, diabetes, blood thinners and earlier injections are also relevant.
What does the physical examination involve?
The clinician looks for muscle wasting, compares both shoulders and measures how far the arm moves on its own and when helped. Strength is tested in each cuff muscle. Common manoeuvres include the empty-can test for the supraspinatus, resisted outward rotation for the infraspinatus, and the belly-press and lift-off tests for the subscapularis.
A positive drop-arm test, where you cannot lower the arm smoothly from 90 degrees, suggests a larger tear. Neck problems that refer pain to the shoulder are also screened.
Which imaging is used for a rotator cuff tear?
An X-ray comes first. It cannot show tendon, but it shows arthritis, bone spurs, calcium deposits and the height of the humeral head. A high-riding head hints at a long-standing large tear.
Ultrasound is quick, affordable and good at showing full-thickness tears, and it lets the clinician watch the tendon move. MRI gives more detail: tear size, retraction, muscle quality and associated biceps or labral damage. MR arthrography, with contrast injected into the joint, may be used when finer detail is needed.
What should you send for a remote review?
For an online opinion, prepare your MRI or ultrasound report and the image files on disc or by secure link, plus recent X-rays. Add a short timeline of symptoms, injections, physiotherapy courses and medicines, along with your height, weight and medical conditions. Our medical record review guide explains the steps, and you can start a free case review any time.
Tests you may have
- Shoulder X-ray in three views: checks bone spurs, arthritis, calcium deposits and whether the humeral head sits too high against the acromion.
- Ultrasound scan: shows full-thickness gaps, tendon thickness and bursal swelling, and allows moving assessment of the tendon in real time.
- MRI scan: the main test for tear size, retraction, muscle fat change and related damage to the biceps tendon or labrum.
- MR arthrogram: contrast in the joint outlines partial articular-side tears and labral problems when a standard MRI is unclear.
- CT scan with or without contrast: measures bone shape and glenoid wear when replacement surgery is being planned.
- Strength and range-of-motion testing: compares active and passive movement to separate weakness from stiffness.
- Diagnostic injection of local anaesthetic: temporary relief helps confirm the shoulder, rather than the neck, as the pain source.
- Blood tests before surgery: check blood count, kidney function and sugar control to assess fitness for anaesthesia.
Look-alikes
Conditions that can feel like rotator cuff tear
Several shoulder and neck problems mimic a cuff tear, and some coexist with it. A cuff tear is more likely when there is real weakness in lifting or rotating the arm, not just pain. The table below compares the common look-alikes and how clinicians tell them apart.
| Look-alike condition | How it differs | How doctors tell |
|---|---|---|
| Shoulder impingement | Pain with overhead arc but usually little true weakness | Painful arc, impingement signs, intact tendon on ultrasound or MRI |
| Frozen shoulder | Stiffness in all directions, passive movement also limited | Passive range reduced on exam, X-ray normal, capsule thickening on MRI |
| Shoulder osteoarthritis | Deep ache, grinding, loss of rotation, worse with use | Joint space narrowing and bone spurs on X-ray |
| Calcific tendinitis | Sudden severe pain, often at rest, in younger adults | Chalky deposit visible on X-ray or ultrasound |
| Cervical radiculopathy | Neck pain, arm tingling or numbness, pain below the elbow | Neck movement reproduces symptoms, nerve signs, neck MRI |
| Labral or SLAP tear | Deep clicking or catching, often with overhead throwing | Specific biceps-labral tests, MR arthrogram |
| Shoulder instability | Feeling the shoulder may slip, apprehension at the extreme of movement | Apprehension and relocation tests, history of dislocation |
Why does the distinction matter for a rotator cuff tear?
Treatment differs. A stiff shoulder needs stretching and perhaps a hydrodilatation, while a torn tendon needs strengthening or repair. Treating stiffness with heavy strengthening can worsen it. Treating a true tear with only rest can allow it to enlarge. Often a person has more than one problem, such as a cuff tear with impingement or with arthritis.
What about incidental tears?
Scans of people with no shoulder pain show cuff tears in a meaningful share of those over 60. A tear on imaging therefore does not prove it is your pain source. Clinicians weigh the scan against your examination, which is why a shoulder specialist should read the images alongside your story.
Non-surgical
Non-surgical treatment for rotator cuff tear
Non-surgical care is the first step for most people with a cuff tear, particularly partial tears, small degenerative tears and tears in people who are not limited in daily life. Structured physiotherapy often gives results close to surgery for pain in the first 1 to 2 years in many studies of degenerative tears. Surgery stays available if progress stalls.
What is the usual order of non-surgical care?
Care normally follows a stepwise ladder. First, calm the shoulder by adjusting activities. Next, begin guided exercise. Add pain relief and, if needed, an injection to let you exercise. Review progress at 6 to 12 weeks and again at around 3 to 6 months.
Activity modification
You do not need to stop using the arm. Reduce the movements that spike pain, such as reaching above shoulder height with heavy loads, and keep the elbow close to the body for lifting. Avoid sleeping on the sore side and use a pillow under the arm to take weight off the tendon. Short, frequent movement is better than long rest, which risks stiffness.
Physiotherapy for a rotator cuff tear
A physiotherapist will usually begin with posture and shoulder-blade control, because the scapula is the base the cuff works from. Then they build rotator cuff and deltoid strength gradually. Programmes typically run 3 times a week for 6 to 12 weeks, then continue as home exercises. Large trials suggest that many people with partial or small full-thickness tears avoid surgery with this approach.
Medicines
Simple analgesics such as paracetamol are the usual start. Non-steroidal anti-inflammatory drugs (NSAIDs) can ease pain for short courses if your kidneys, stomach and heart allow. Topical gels carry less risk. Discuss any medicine with your clinician, especially if you take blood thinners. Opioids are generally avoided for long-term shoulder pain.
Injections
A corticosteroid injection into the subacromial space can reduce pain for several weeks and make exercise easier. Repeated injections may weaken tendon, so most clinicians limit them, and many avoid them in the 3 months before surgery. Platelet-rich plasma and hyaluronic acid are sometimes offered, but evidence for repairing a torn tendon is still limited, so ask about the reasoning.
What do the studies suggest?
Randomised trials of small to medium degenerative tears suggest that early surgery and structured physiotherapy often give similar pain relief at 1 to 2 years, although some people in the physiotherapy groups later choose surgery. Acute tears in active younger people tend to do better with early repair. Treatment should therefore be personalised, not driven by the scan alone.
Signs that non-surgical care is not enough
Ask your specialist to reassess if pain has not improved after 3 months of well-delivered exercise, if strength is falling, if night pain stops sleep, or if a tear is shown to be enlarging on repeat imaging.
Self-care
Exercises and self-care for rotator cuff tear
Gentle, regular exercise is the most useful self-care for a cuff tear, provided you check with your doctor or physiotherapist first. The aim is to keep the joint moving, build the supporting muscles and avoid positions that irritate the tendon. Pain should stay mild, around 3 out of 10, and settle within an hour.
Which rotator cuff tear exercises are usually used?
Rotator cuff tear exercises are normally introduced in phases. Early movement comes first, followed by controlled strength work. A physiotherapist will tailor the order to the tear and to whether you have had surgery.
- Pendulum swings: lean forward, let the arm hang, and make small circles for 1 minute, 2 to 3 times a day.
- Table slides: rest the forearm on a table and slide forwards, easing the arm upwards without lifting through the shoulder.
- Scapular squeezes: draw the shoulder blades gently back and down, hold for 5 seconds, repeat 10 times.
- Isometric rotations: press the back of the hand into a wall without moving, holding 10 seconds, building to 10 repetitions.
- Band external rotation: with the elbow tucked to your side, rotate outward against a light band for 2 sets of 10.
- Band row: pull a band towards the waist to strengthen the muscles between the shoulder blades.
How should exercises progress?
Move forward only when the current stage is easy for 2 to 3 sessions in a row. Progress from supported to unsupported movement, from low to higher reach, and from light band resistance to light weights. Do not jump straight to overhead lifting. If the shoulder is sore the next morning, drop back one step for several days.
Everyday habits that help
Keep frequently used items between waist and shoulder height. Carry loads close to the body and share them between arms. Sit with the shoulder blades supported and avoid slumped desk posture. Take micro-breaks from overhead work every 30 to 45 minutes. A heat pack before exercise and an ice pack after can ease soreness.
What to avoid
Avoid heavy overhead pressing, lifting a heavy object away from your body, sudden jerks and prolonged sleeping on the sore side. Do not push through sharp pain. If you feel a sudden pop, new weakness, or numbness spreading down the arm, stop and seek assessment.
Check with your doctor or physiotherapist before starting new exercises, and stop any movement that causes sharp pain.
Treatment
Rotator cuff tear treatment options
Surgery for a cuff tear aims to reattach the tendon to bone, or, when repair is not possible, to restore function by other means. The right choice depends on tear size, tendon and muscle quality, age, activity and shoulder arthritis. Options are summarised below, with links to the detailed procedure pages.
Rotator cuff repair
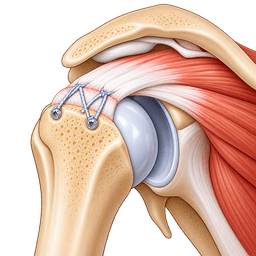
Rotator cuff repair is the standard operation for a tear that can be pulled back to its footprint on the bone. The surgeon secures the tendon with small anchors and strong sutures, placed through keyhole incisions. Most repairs take 1 to 2 hours. Rotator cuff repair surgery in turkey is described on our rotator cuff repair in turkey page, and see the rotator cuff repair cost guide for how prices are assembled.
Shoulder arthroscopy
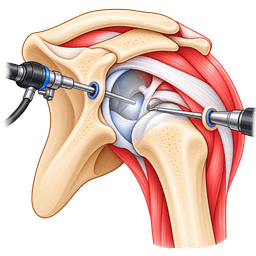
Shoulder arthroscopy is the keyhole technique in which a camera and small instruments are used to inspect and treat the joint. For a partial tear, the surgeon may smooth (debride) the frayed tendon, treat the biceps tendon or remove bone spurs. Details for patients travelling are on shoulder arthroscopy in turkey, with a matching cost guide.
Options for large or irreparable tears
When a massive tear cannot be fully repaired, surgeons may perform a partial repair, add a graft or patch for reinforcement, move a nearby tendon to take over lost function, or place a balloon-type spacer under the acromion. Each has trade-offs and limited long-term data, so ask about the evidence behind your surgeon's preferred method.
Reverse shoulder replacement
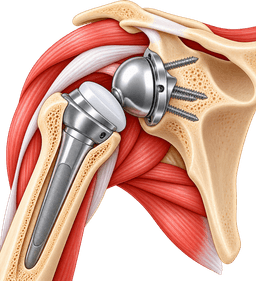
If the tear is massive and the shoulder has lost its ability to lift, or arthritis has developed, a reverse shoulder replacement may be advised. This implant flips the ball and socket so that the deltoid, rather than the torn cuff, powers the arm. It often restores lifting in people with irreparable tears. See reverse shoulder replacement in turkey and the cost guide.
How do the options compare?
| Option | Best suited to | Main trade-off |
|---|---|---|
| Arthroscopic debridement | Partial tears with a clear pain source, such as the biceps | Does not restore a torn tendon's attachment |
| Arthroscopic repair | Repairable full-thickness tears, good muscle quality | Tendon can fail to heal, especially in large tears; sling and slow rehabilitation |
| Graft or tendon transfer | Younger patients with irreparable tears | Specialised, longer recovery, less certain results |
| Reverse replacement | Older patients with massive tears, weakness or arthritis | Implant lifespan and lifting restrictions |
When surgery is considered
Consider surgery for a cuff tear when strength loss or pain continues despite a proper trial of non-surgical care, or when the tear is recent and the tissue is healthy. A specialist opinion is worthwhile earlier if you are young, active or have a sudden injury. The decision is shared between you and your surgeon.
Which situations favour early repair?
Early repair is often discussed for an acute full-thickness tear in a person under about 65 with a physically demanding life. Prompt surgery matters because tendons retract and muscles lose quality as months pass. A tear after a dislocation, particularly in older patients, deserves quick review.
Which situations favour waiting?
Waiting with exercise is reasonable for a partial tear, a small degenerative tear with good function, or tears in people whose daily demands are modest. Many people stay comfortable. Regular review, with repeat ultrasound if symptoms change, allows you to move to surgery if the tear enlarges.
Which factors make repair less likely to succeed?
Larger size, severe fatty muscle change, older age, smoking, diabetes and poor-quality tendon reduce the chance of healing. Your surgeon will discuss them honestly. Stopping smoking at least 4 to 6 weeks before surgery improves odds, and good blood sugar control also helps.
What should you ask before agreeing to surgery?
- How large is my tear, and is it repairable with my muscle quality?
- What is the chance that the tendon will heal, and what does a failed repair mean for me?
- What happens if I wait 6 months?
- How long will I wear a sling, and when can I drive and return to work?
- What alternatives exist if repair is not possible?
Our questions to ask before surgery abroad guide offers a fuller checklist.
Procedures
Procedures that may treat rotator cuff tear
Costs
Rotator cuff tear treatment cost in Turkey
| Procedure | Turkey package | US self-pay | Saving |
|---|---|---|---|
| Reverse Shoulder Replacement | $10,000 – $15,500 | $50,475 | ~75% |
| Shoulder Arthroscopy | $3,000 – $5,500 | $17,350 | ~76% |
| Rotator Cuff Repair | $4,500 – $7,500 | $24,513 | ~76% |
Packages are contracted partner prices with validity dates; benchmarks are source-backed estimates. Open a cost guide for the full country comparison.
In Turkey
Treating rotator cuff tear in Turkey
Rotator cuff tear treatment in turkey can suit people with a planned, non-urgent tear who have recent scans and want an orthopedic team experienced in shoulder surgery. Safe care depends on a careful remote review before travel, clear after-care arrangements and honest advice on whether the trip is sensible. Our turkey orthopedics overview explains the wider system.
When does treatment abroad make sense?
Treatment abroad can make sense when you have a confirmed tear, have tried or understand the non-surgical options, and your surgery is elective. It suits patients seeking a repair or reverse replacement who are healthy enough to fly. It is not appropriate for an acutely unwell person, and anyone with a fresh injury must first receive urgent local assessment.
What does the pathway look like?
- Records review: you send scans, reports and a symptom timeline for a surgeon's opinion through our free case review.
- Plan: the team proposes repair, arthroscopy or replacement and outlines the stay, anaesthetic and rehabilitation.
- Travel and admission: you arrive a few days before surgery for examination and pre-operative tests.
- Surgery and early recovery: arthroscopic repair is often a day case or 1-night stay; replacement usually 2 to 3 nights.
- Follow-up: a wound and sling check before you fly, then rehabilitation at home with remote reviews.
What should you send for assessment?
Send the latest MRI or ultrasound images and report, X-rays, a list of medicines, your allergies and previous operations, and a short account of how the shoulder limits you. Ask your local physiotherapist for notes. The treatment planning guide shows what a typical plan includes.
How do you check accreditation and surgeon experience?
Ask whether the hospital holds national health-ministry licensing and international accreditation, such as JCI. Ask the surgeon how many shoulder operations they perform per year, what proportion are arthroscopic repairs, and how they measure healing. Request the implant brand and ask how complications are handled. Avoid any provider that refuses to answer.
What are realistic travel and timing considerations?
Plan on 5 to 7 days in the country for a repair and 7 to 10 days for a replacement, with a companion if you can. Flying is usually possible once the surgeon clears you, and our flying after surgery guide covers sling use and clots. Cities such as Istanbul offer major orthopedic centres and direct flights. Read our rehabilitation guide before you book.
When should you not travel?
Postpone travel if you have a new injury needing local care, an uncontrolled medical illness, an active infection, or if the surgeon cannot confirm the plan after reviewing your images. Longer flights soon after other recent surgery or untreated clots also need medical clearance.
Ask about the cost of each stage through the cost guide, which explains inclusions without quoting figures here.
Complications
Complications of rotator cuff tear
A cuff tear that is left alone may enlarge, and surgery carries its own small risks, so both paths need honest discussion. Most people do well, but a clear view of what can go wrong helps you decide. The figures below are approximate and vary with tear size and patient health.
What can happen if a rotator cuff tear is not treated?
Some tears stay stable for years. Others grow, particularly when symptoms are present. As a tear enlarges, the muscle may thin and fill with fat, making repair harder or impossible. The humeral head can drift upwards and, in time, arthritis can develop, which is the pathway to rotator cuff tear arthropathy.
Ongoing weakness may reduce independence, interfere with sleep and increase strain on the neck and the other shoulder.
What are the risks of rotator cuff repair?
- Re-tear or failure to heal: a repaired tendon does not always knit to bone, and failure is more common in large tears and in older patients, roughly 1 in 4 or more across large series.
- Stiffness: scar tissue can limit movement in some people, often settling with physiotherapy.
- Infection: uncommon, below 1 in 100 for keyhole surgery.
- Nerve irritation or injury: temporary numbness is possible, with lasting injury rare.
- Blood clots: rare after shoulder surgery, but mobility and hydration matter after flights.
- Anaesthetic risks: reviewed in advance, with age and other illnesses taken into account.
What are the risks of reverse replacement?
Risks include dislocation of the implant, infection, loosening over many years, a fracture of the shoulder blade and nerve injury. Implants generally last 10 or more years in many people, but revision may be needed. Lifting limits are advised to protect the new shoulder.
How can complications be reduced?
Stop smoking, control blood sugar, follow sling and exercise instructions, report fever or wound discharge quickly, and attend follow-up. Choosing an experienced team with a clear after-care plan reduces risk.
Urgent care
When to seek urgent care for rotator cuff tear
- A sudden pop or tearing after a fall with immediate loss of arm lifting: seek urgent local assessment the same day.
- Hot, red, swollen shoulder with fever or chills: this may be infection, so go to emergency care straight away.
- Numbness, tingling or weakness spreading down the arm or into the hand: get urgent review, as a nerve or neck problem may be involved.
- Chest pain, breathlessness or pain spreading to the jaw or left arm: call emergency services, as it may be heart-related.
- After surgery, increasing pain, wound discharge or fever above 38 degrees C: contact your surgical team promptly.
- Calf swelling or sudden breathlessness after a flight: seek emergency help because of clot risk.
- Constant night pain with weight loss or a history of cancer: arrange prompt medical review to exclude other causes.
Prevention
How to lower your risk of rotator cuff tear
You cannot prevent every cuff tear, because age-related tendon change is common, but you can lower risk and slow progression. Sensible loading, shoulder-blade strength and healthy habits all help. If you already have symptoms, prevention means protecting the tear from enlarging.
How can you protect your shoulders from a rotator cuff tear?
Strengthen the rotator cuff and the muscles around the shoulder blade 2 to 3 times each week, and keep the shoulder mobile. Warm up before sport or heavy work. Build load slowly, adding no more than around 10% a week in gym or throwing programmes, so tendons can adapt.
What workplace and sport changes help?
Use steps or platforms rather than reaching overhead, share heavy lifts and keep tools close to the body. Swimmers and throwers benefit from technique coaching and rest days. Rotate overhead tasks when possible and take regular breaks. If you play tennis or golf, check your technique after any shoulder pain.
Which health habits matter?
Stopping smoking improves tendon blood flow and healing. Controlling diabetes and cholesterol supports tendon health. Maintaining a healthy weight reduces overall joint load, and good sleep posture reduces night strain on the shoulder.
What cannot be prevented?
Tendon ageing, family tendency and unexpected falls cannot be prevented. Reduce fall risk at home with good lighting, secure rugs and sensible footwear. Early assessment of a painful shoulder, rather than months of pushing through, can limit damage to the tendon.
Can you stop a small tear from getting larger?
Evidence is incomplete, but staying active in a pain-guided way, working on strength, avoiding repeated heavy overhead loads and reviewing symptoms with a specialist all seem sensible. A repeat scan is often suggested if pain increases or strength falls.
Outlook
Living with rotator cuff tear: outlook and recovery
The outlook for a cuff tear is generally good, whether it is treated with exercise or surgery, though the road is slower than many expect. Pain usually improves long before strength does. Your result depends on tear size, tendon quality, age and how closely you follow the rehabilitation plan.
What is the natural history without surgery?
Many small and partial tears settle into a stable, tolerable state. Over several years, a proportion enlarge, and symptoms can increase when that happens. People who keep strength and movement tend to cope better. Regular reviews are wise if you have chosen not to operate.
What is the typical rotator cuff tear recovery time after repair?
Rotator cuff tear recovery time after repair is measured in months. A typical timeline is shown below, though surgeons vary in how fast they progress.
| Stage | Typical timing | What happens |
|---|---|---|
| Protection | 0 to 6 weeks | Sling worn, gentle passive movement, hand and elbow exercises |
| Active movement | 6 to 12 weeks | Sling weaned, active lifting begins, light daily use |
| Strengthening | 3 to 6 months | Resistance exercises added gradually |
| Return to activity | 6 to 12 months | Heavier work and sport, with continuing improvement up to a year |
When can you drive, work and play sport?
Desk work is often possible within 2 to 4 weeks. Driving usually returns around 6 weeks once you can control the wheel safely and are off strong painkillers. Heavy manual jobs and overhead sport commonly wait 4 to 6 months or longer, with swimming and throwing often at 6 to 9 months.
What are the long-term results?
Most people who have a successful repair report less pain and better function that lasts for many years. Even when the tendon does not fully heal, many patients are still more comfortable than before. For massive tears with arthritis, reverse replacement often restores comfortable lifting for a decade or more, though overhead strength is not fully normal.
What helps you do well?
Attending every physiotherapy session, keeping within sling and lifting limits, sleeping in a supported position and being patient with progress all help. Ask your team for written milestones so you can see progress, and keep in touch after returning home using our follow-up guide.
Surgeons
Specialists who treat rotator cuff tear
FAQ
Rotator cuff tear: frequently asked questions
Can a rotator cuff tear heal on its own?
What are the first signs of a rotator cuff tear?
How is a rotator cuff tear diagnosed?
Do all rotator cuff tears need surgery?
How long is rotator cuff tear recovery time after surgery?
What exercises help a rotator cuff tear?
Is a partial thickness rotator cuff tear serious?
What is a massive rotator cuff tear?
Can I sleep on my side with a rotator cuff tear?
Is rotator cuff tear treatment in turkey safe?
How do I know if rotator cuff tear surgery in turkey is suitable for me?
What should I send for a remote review?
When should I see a doctor urgently?
Sources
Sources for this rotator cuff tear guide
Peer-reviewed guidance and institutional sources used to write and review this page.
- 01Rotator Cuff Tears
American Academy of Orthopaedic Surgeons OrthoInfo, 2023
https://orthoinfo.aaos.org/en/diseases--conditions/rotator-cuff-tears/
- 02Rotator cuff tear overview
Cleveland Clinic, 2023
https://my.clevelandclinic.org/health/diseases/8291-rotator-cuff-tear
- 03Rotator cuff tear
Mayo Clinic, 2022
https://www.mayoclinic.org/diseases-conditions/rotator-cuff-injury/symptoms-causes/syc-20350225
- 04
- 05
- 06Shoulder injuries and disorders
MedlinePlus, 2023
https://medlineplus.gov/shoulderinjuriesanddisorders.html
- 07Surgery versus conservative management of degenerative rotator cuff tears
PubMed, 2022
https://pubmed.ncbi.nlm.nih.gov/?term=rotator+cuff+tear+physiotherapy+versus+surgery