Key takeaways
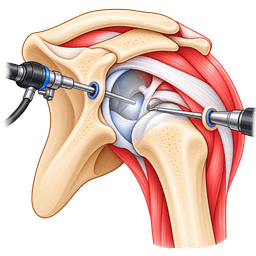
- 1Shoulder Arthroscopy is minimally invasive keyhole surgery that allows a surgeon to see inside the shoulder using a small camera and treat selected problems through several small portals.
- 2It is a surgical approach rather than one single operation. Arthroscopy can be used for rotator cuff repair, labral repair, shoulder stabilization, biceps procedures, capsular release, bursectomy, distal clavicle excision, loose-body removal and other selected treatments.
- 3A purely diagnostic arthroscopy is less common today because MRI, ultrasound and CT can diagnose many shoulder problems before surgery. Arthroscopy is most valuable when the surgeon expects to treat a confirmed or strongly suspected problem during the same operation.
- 4How long does a shoulder arthroscopy take? A relatively limited procedure may take approximately 30–60 minutes, while repair of the rotator cuff, labrum or multiple structures can take one to three hours or longer.
- 5Most shoulder arthroscopies are performed as outpatient surgery, with discharge on the same day once pain, nausea and medical status are controlled.
- 6How long do you wear a sling after shoulder arthroscopy? It can range from little or no sling use after a diagnostic arthroscopy to 2–6 weeks or longer when tissue has been repaired.
- 7Arthroscopy of the shoulder recovery time varies from days to many months. Debridement or diagnostic procedures recover much faster than tendon or labral repair.
- 8Small incisions do not mean the internal operation is minor. A tendon secured to bone still requires biological healing even when the repair was performed through tiny portals.
- 9Shoulder arthroscopy generally has a low rate of major complications, but risks include infection, stiffness, nerve injury, blood-vessel injury, blood clots, fluid extravasation, persistent symptoms and procedure-specific repair failure.
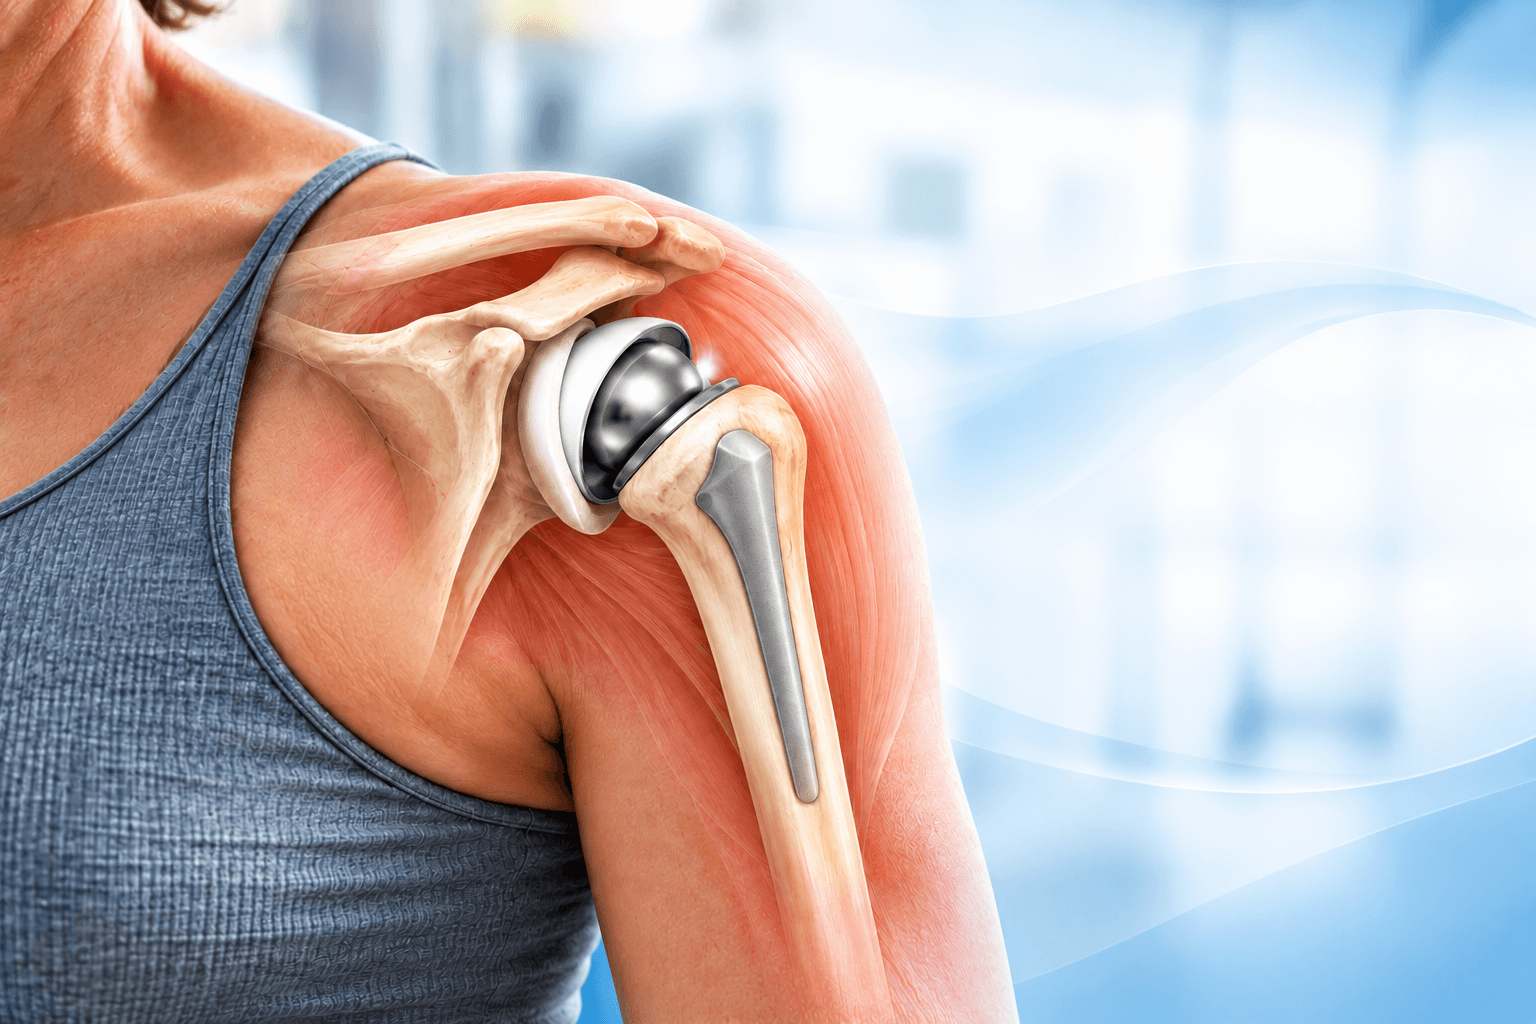
- 10Arthroscopy is not automatically appropriate for every painful shoulder. Significant arthritis, irreparable cuff disease or structural bone deficiency can require another operation such as shoulder replacement or open reconstruction.
- 11Rehabilitation should follow the actual procedure performed, not a generic “shoulder arthroscopy protocol.”
- 12Patients traveling for shoulder arthroscopy should receive an operative report, rehabilitation protocol and clear instructions about sling use, physiotherapy and follow-up before returning home.
Overview
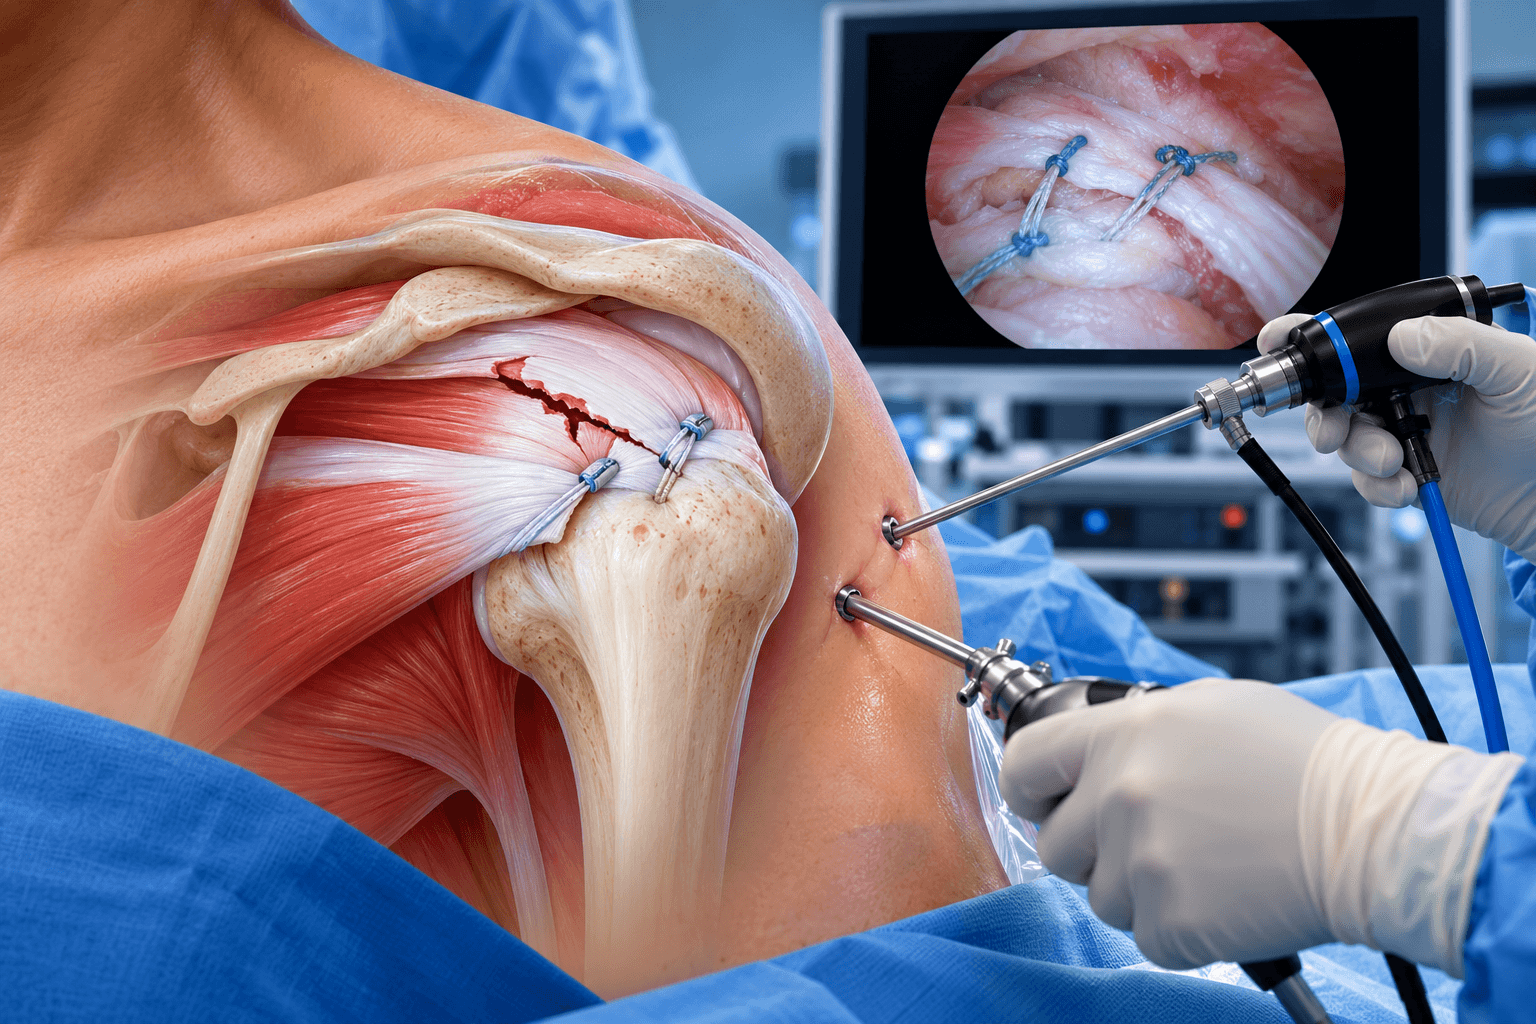
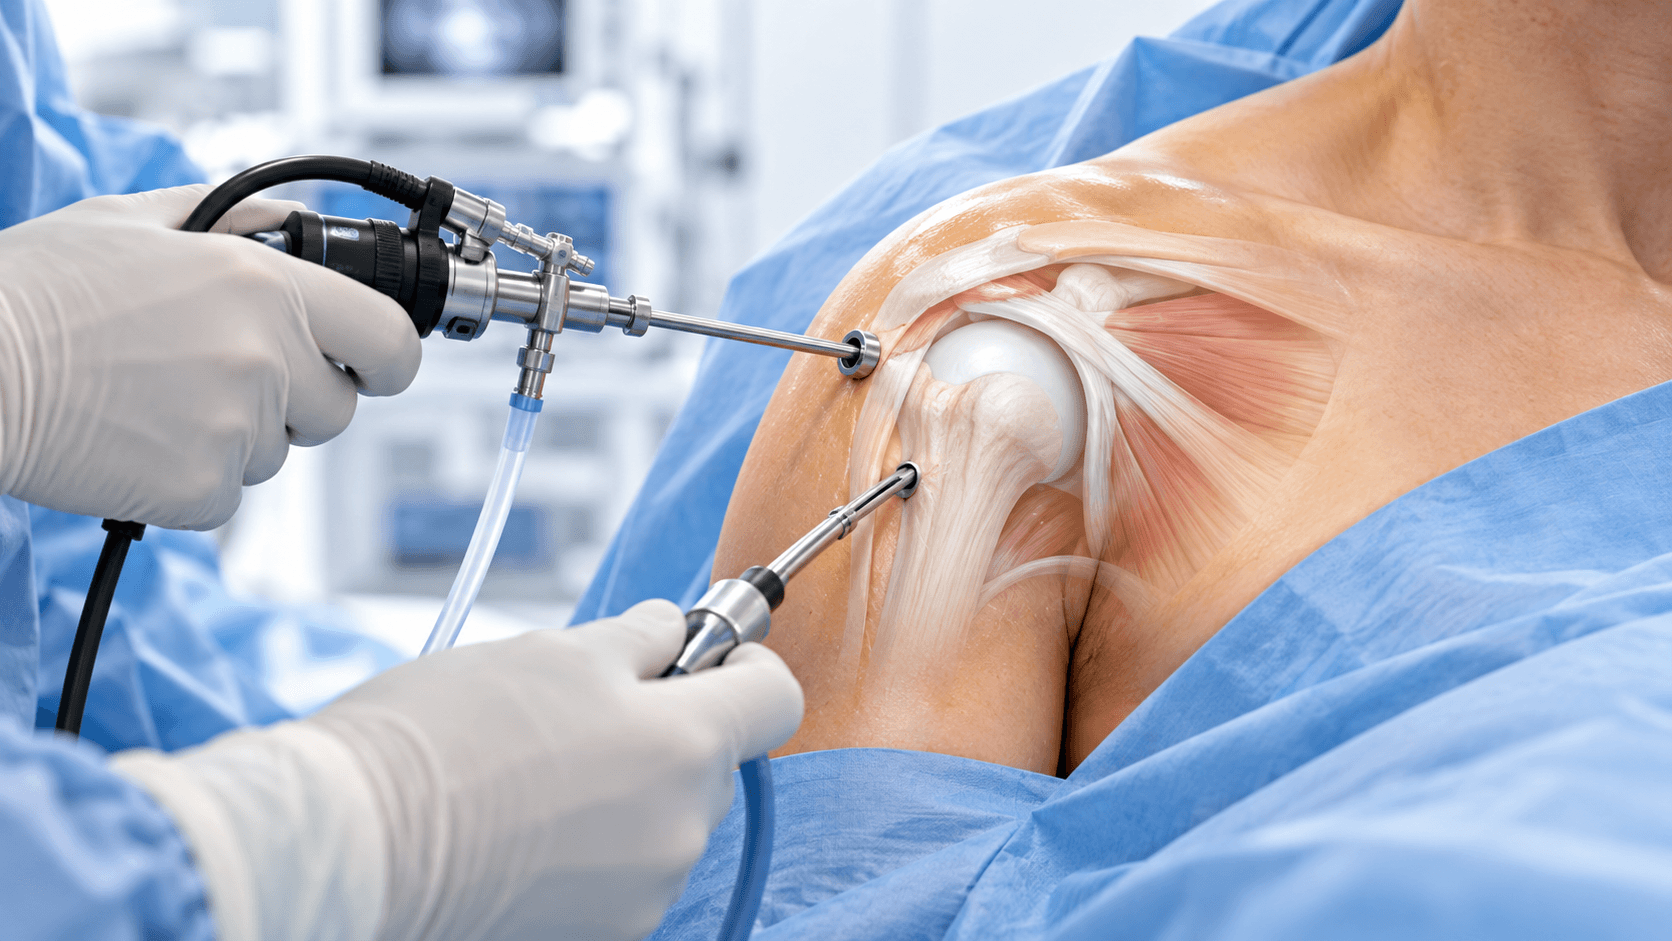
Shoulder Arthroscopy is a minimally invasive surgical technique in which an orthopedic surgeon places a small camera into the shoulder through a small incision and views the inside of the joint on a monitor. Additional instruments can be inserted through separate small portals to repair damaged tissue, remove inflamed tissue or perform other procedures.
The arthroscope contains a light source and camera. Sterile fluid is circulated through the shoulder to expand the working space and improve visibility. The surgeon can inspect structures in far greater detail than would be possible simply by looking through a small skin incision.
Arthroscopy can evaluate the articular cartilage, labrum, long head of the biceps tendon, rotator cuff, joint capsule and other structures inside the glenohumeral joint. The surgeon can also move the camera into the subacromial space above the rotator cuff to treat bursal and tendon pathology.
What Does “Arthroscopy Shoulder” Mean?
People searching terms such as “arthroscopy shoulder” or “shoulder surgery arthroscopy” are usually referring to keyhole shoulder surgery.
The word arthroscopy comes from terms meaning to look inside a joint.
The important distinction is that “Shoulder Arthroscopy” describes how the surgeon accesses the shoulder, not the exact condition being treated.
Two patients can both be told they are having shoulder arthroscopy while undergoing completely different operations. One may have inflamed tissue removed and return to ordinary activity within weeks, while another may undergo a multi-tendon rotator cuff repair followed by six months or more of rehabilitation.
What Is an Arthroscope?
An arthroscope is a narrow rigid camera system designed for surgery inside a joint.
The camera sends magnified images to a high-definition monitor.
Different viewing angles can be used to inspect different areas of the shoulder.
The arthroscope is much smaller than the incision required for traditional open joint exposure, which is why arthroscopy is often described as keyhole surgery.
Is Shoulder Arthroscopy the Same as Open Shoulder Surgery?
No.
Open surgery uses a larger incision to expose the shoulder directly.
Arthroscopy uses several small portals and a camera.
Many shoulder conditions can now be treated arthroscopically, but open surgery remains appropriate for selected fractures, tendon transfers, major bone reconstruction, shoulder replacement and certain complex instability procedures.
The best operation depends on the pathology rather than on trying to make every procedure minimally invasive.
Is Arthroscopic Surgery Automatically Better Than Open Surgery?
Not necessarily.
Arthroscopy can reduce soft-tissue disruption, provide excellent visualization and create smaller scars.
However, an operation should be selected according to the condition being treated.
An open procedure can be safer or more effective when large bone grafts, prostheses or major reconstructions are required.
A technically difficult arthroscopic operation should not be chosen purely because it sounds more modern.
The objective is successful treatment, not simply the smallest incision.
Diagnostic Shoulder Arthroscopy
Diagnostic arthroscopy means looking inside the joint to identify pathology.
Historically, it was used more frequently because imaging techniques were less accurate.
Modern MRI, ultrasound and CT allow many shoulder conditions to be diagnosed before surgery.
As a result, an operation performed solely to “look around” is less common today.
Diagnostic arthroscopy remains useful when symptoms remain unexplained despite appropriate assessment or when the surgeon expects to confirm and treat pathology during the same procedure.
Therapeutic Shoulder Arthroscopy
Most modern shoulder arthroscopy is therapeutic.
The surgeon enters the shoulder because there is a specific problem that can potentially be treated.
Examples include a torn rotator cuff, detached labrum, unstable shoulder, diseased biceps tendon, contracted capsule or loose body.
This distinction matters because therapeutic surgery creates different healing requirements depending on what is repaired.
Anatomy Seen During Shoulder Arthroscopy
The shoulder is not simply one open space.
The main joint is the glenohumeral joint, formed by the humeral head and glenoid.
The labrum surrounds the glenoid rim and deepens the socket.
The long head of the biceps tendon attaches near the superior labrum and passes through the joint.
The rotator cuff tendons surround the humeral head.
Above the cuff lies the subacromial bursa beneath the acromion.
Arthroscopy allows the surgeon to move between these different anatomical regions through carefully positioned portals.
Glenohumeral Joint Arthroscopy
The surgeon commonly starts inside the glenohumeral joint.
The humeral and glenoid cartilage are inspected.
The labrum is examined around the socket.
The biceps tendon and its attachment are evaluated.
The undersurface of the rotator cuff can also be seen.
Any unexpected cartilage damage, synovitis or loose fragments can be identified.
Subacromial Arthroscopy
The arthroscope can then be placed into the subacromial space.
This area lies between the rotator cuff and the underside of the acromion.
Inflamed bursal tissue can be removed to improve visualization.
The outer surface of the rotator cuff can be examined.
Rotator cuff tears are commonly repaired from this space.
Selected acromial or acromioclavicular procedures can also be performed arthroscopically.
What Conditions Can Shoulder Arthroscopy Treat?
Shoulder arthroscopy can treat multiple problems, including rotator cuff tears, labral injuries, shoulder instability, certain SLAP lesions, biceps tendon disease, symptomatic loose bodies, selected cartilage lesions, frozen shoulder, synovitis and symptomatic acromioclavicular joint pathology.
It can also be used in selected cases of shoulder impingement or subacromial pathology.
However, not every imaging abnormality should be treated simply because arthroscopy provides access to it.
The surgeon should identify which findings actually explain the patient's symptoms.
Rotator Cuff Repair
Rotator cuff repair is one of the major arthroscopic shoulder procedures.
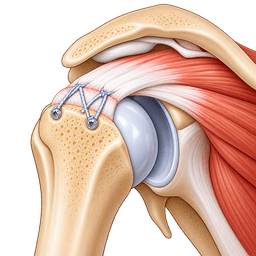
The surgeon identifies the torn tendon, prepares the area of the greater tuberosity where the tendon originally attached and uses suture anchors to secure the tendon back to bone.
Although the skin incisions are small, the internal repair is significant.
The tendon requires months to biologically heal to bone.
For this reason, rotator cuff repair has one of the longest recovery periods among shoulder arthroscopy procedures.
Partial Rotator Cuff Tears
Some partial-thickness tears do not require repair.
The surgeon can remove unstable frayed fibers in selected lower-grade tears.
High-grade partial tears may require actual tendon repair.
The operation can involve completing the tear before repair or repairing it while preserving intact fibers.
The rehabilitation difference between simple debridement and repair is substantial.
Labral Repair
The labrum is a rim of fibrocartilage around the glenoid.
It contributes to shoulder stability and provides attachment for ligaments and the biceps tendon.
Trauma or repeated instability can detach the labrum from bone.
During arthroscopic labral repair, the surgeon places small anchors into the glenoid and uses sutures to restore the labrum to its attachment.
The capsule can also be tightened when excessive laxity contributes to instability.
Bankart Repair
A Bankart lesion is a tear of the anterior-inferior labrum commonly associated with anterior shoulder dislocation.
Arthroscopic Bankart repair reattaches the labrum and retensions the capsule.
The surgeon places several small anchors around the glenoid rim.
The repair needs protection while the labrum and capsule heal.
Sling use therefore commonly lasts several weeks rather than only a few days.
Shoulder Stabilization Surgery
Shoulder instability can involve more than one lesion.
The surgeon assesses the labrum, capsule and glenoid bone.
Arthroscopic stabilization is effective in appropriately selected patients with limited bone loss.
Significant glenoid bone loss or an engaging humeral-head defect can require additional procedures.
A patient with major bone deficiency may be better treated with a bone-transfer or other stabilization procedure rather than an isolated soft-tissue Bankart repair.
Remplissage
Remplissage is an arthroscopic technique used with selected Hill-Sachs defects in recurrent anterior instability.
The surgeon attaches the posterior capsule and infraspinatus tendon into the humeral-head defect.
This reduces the chance that the defect will engage the glenoid rim during vulnerable positions.
Remplissage can be combined with Bankart repair.
The surgeon considers the degree of bone loss and the patient's sport before deciding whether this is appropriate.
SLAP Repair
A SLAP tear involves the superior labrum around the attachment of the long head of the biceps.
Some symptomatic lesions can be repaired arthroscopically.
Small anchors and sutures reattach the superior labrum.
However, not every SLAP abnormality requires repair.
Age, activity, tear pattern and biceps health matter.
Biceps tenodesis can be a more appropriate treatment in many adults with symptomatic superior labral and biceps disease.
Biceps Tenodesis
Biceps tenodesis treats pathology of the long head of the biceps tendon.
The tendon is released from its damaged attachment and fixed to the humerus at another location.
The intra-articular part can be managed arthroscopically.
Fixation can be performed arthroscopically or through a small additional incision depending on technique.
Rehabilitation protects the tendon fixation, particularly from resisted elbow flexion and supination during early healing.
Biceps Tenotomy
Biceps tenotomy releases the long head of the biceps without fixing it elsewhere.
It can provide effective pain relief in selected patients.
The operation is relatively simple and does not require healing of a new fixation site.
Some patients develop a visible “Popeye” contour or cramping.
The decision between tenotomy and tenodesis depends on age, activity, cosmetic preference and tendon condition.
Subacromial Bursectomy
The subacromial bursa can become inflamed and painful.
During arthroscopy, inflamed bursal tissue can be removed when clinically appropriate.
Bursectomy is also commonly performed to create visualization during rotator cuff surgery.
Removing bursal tissue for surgical access should not automatically be interpreted as a separate major treatment.
The underlying tendon and shoulder mechanics remain more important.
Subacromial Decompression
Subacromial decompression historically became a common operation for shoulder impingement.
It can include removal of inflamed bursa and reshaping part of the acromion.
Modern evidence has made routine decompression for atraumatic subacromial pain more controversial.
For many patients without a repairable structural lesion, high-quality rehabilitation should be emphasized before surgery.
Acromial reshaping remains useful in selected anatomical or combined surgical situations rather than as an automatic step in every arthroscopy.
Acromioplasty
Acromioplasty means reshaping part of the underside of the acromion.
It can be performed with an arthroscopic burr.
It was once commonly combined with nearly every rotator cuff operation.
Current evidence does not support routine acromioplasty for every rotator cuff tear.
The surgeon should have a specific reason for including it.
Distal Clavicle Excision
The acromioclavicular joint can become painful because of arthritis or other pathology.
Arthroscopic distal clavicle excision removes a small amount of bone from the end of the clavicle.
A gap remains between the clavicle and acromion, reducing painful bone contact.
The procedure should be performed because the AC joint is clinically symptomatic rather than because arthritis is visible on an X-ray.
Many people have asymptomatic AC joint degeneration.
Frozen Shoulder Capsular Release
Frozen shoulder, or adhesive capsulitis, causes severe restriction of the joint capsule.
Most cases improve without surgery.
When prolonged stiffness remains disabling despite appropriate treatment, arthroscopic capsular release can divide selected tight portions of the capsule.
Unlike tendon repair, recovery emphasizes maintaining the new range of motion.
Physical therapy usually begins early because allowing the shoulder to become immobilized again would undermine the purpose of the procedure.
Manipulation Under Anaesthesia
Capsular release can be combined with manipulation under anaesthesia.
The surgeon carefully moves the shoulder through restricted ranges while the patient is anaesthetized.
The purpose is to stretch or release contracted tissue.
Manipulation needs to be controlled because excessive force can cause fracture or soft-tissue injury.
Arthroscopic visualization allows the surgeon to release specific capsule areas directly.
Loose Body Removal
Fragments of cartilage or bone can become loose within the joint.
They may cause catching, locking or pain.
Arthroscopy allows the surgeon to locate and remove these fragments.
The underlying reason the loose body formed is also important.
If severe arthritis is producing repeated fragments, removing one loose body cannot reverse the overall degenerative condition.
Cartilage Lesions
Focal cartilage damage can sometimes be treated arthroscopically.
The surgeon can stabilize loose cartilage edges or use selected marrow-stimulation techniques for small contained defects.
Large diffuse cartilage loss is different.
Arthroscopy cannot restore a severely arthritic shoulder to normal cartilage.
Patients with advanced joint degeneration may obtain more predictable benefit from shoulder replacement when symptoms become severe.
Synovectomy
Synovitis means inflammation of the joint lining.
Selected inflammatory or proliferative synovial conditions can be treated with arthroscopic synovectomy.
The surgeon removes abnormal inflamed tissue.
The underlying cause still needs medical treatment when systemic inflammatory disease is present.
Arthroscopy treats the local joint problem rather than curing the systemic disorder.
Calcific Tendinitis
Calcium deposits can form within rotator cuff tendons.
Many cases improve with nonsurgical treatment.
Persistent severe cases can occasionally undergo arthroscopic removal.
The surgeon opens the tendon region containing calcium and removes as much deposit as clinically appropriate.
Large defects created during removal can require tendon repair.
Shoulder Arthritis
Arthroscopy has only a limited role in advanced shoulder arthritis.
Selected younger patients with mild disease, loose bodies or mechanical symptoms can sometimes obtain temporary improvement from debridement.
Arthroscopy does not replace lost cartilage across an entire arthritic joint.
When bone-on-bone arthritis is advanced, shoulder replacement generally provides more definitive treatment.
Why Arthroscopy Can See More Than Imaging
MRI and ultrasound are extremely useful, but arthroscopy allows direct inspection of tissue.
The surgeon can probe the labrum, evaluate cartilage texture and assess tendon quality dynamically.
An abnormal MRI finding can look less significant at arthroscopy, while additional pathology can occasionally be discovered.
This does not mean arthroscopy should replace diagnostic imaging.
The strongest treatment decisions combine history, examination, imaging and surgical findings.
Is Diagnostic Arthroscopy Still Necessary?
Purely diagnostic arthroscopy is uncommon in routine modern practice.
It can still be useful when symptoms remain significant and imaging cannot adequately explain them.
However, surgery should not be used simply because uncertainty exists.
The patient should understand what the surgeon expects to find and what treatment might be performed if pathology is confirmed.
Who it's for
- Repairable rotator cuff tears causing persistent pain, weakness or functional limitation
- Acute traumatic rotator cuff tears in appropriate patients
- Symptomatic high-grade partial rotator cuff tears after appropriate nonsurgical treatment
- Recurrent anterior shoulder instability suitable for arthroscopic Bankart repair
- Labral tears associated with clinically important instability
- Selected SLAP lesions requiring repair
- Long-head biceps tendon disease requiring tenodesis or tenotomy
- Persistent symptomatic loose bodies within the shoulder
- Selected focal cartilage lesions
- Frozen shoulder that remains severely restricted despite appropriate nonsurgical management
- Symptomatic acromioclavicular joint arthritis requiring distal clavicle excision
- Selected subacromial pathology when surgery is clinically justified
- Calcific tendinitis that remains severely symptomatic despite nonsurgical treatment
- Synovial disorders suitable for arthroscopic synovectomy
- Selected cases requiring direct diagnostic inspection after appropriate imaging remains inconclusive
- Combined shoulder pathology that can be addressed during one arthroscopic procedure
Good candidates
A good candidate has a clearly identified shoulder problem that is likely to improve with an arthroscopic procedure.
The surgeon should be able to explain what structure is causing the symptoms and what will actually be treated.
An MRI abnormality alone is not enough.
Rotator cuff tears, labral changes and AC joint arthritis can exist in people without pain.
The examination and symptoms need to correlate with the proposed surgery.
Patients With Rotator Cuff Tears
Many cuff tears can initially be treated without surgery.
A patient becomes a stronger surgical candidate when persistent pain, significant weakness, traumatic injury, progressive functional limitation or repairable structural pathology justify reconstruction.
The surgeon also evaluates tear size, retraction and muscle quality.
A repairable tendon is different from a massive chronic tear with severe fatty degeneration.
Patients With Recurrent Shoulder Dislocation
Arthroscopic stabilization is commonly used when repeated instability is caused primarily by labral and capsular injury and glenoid bone loss remains limited.
The surgeon should assess bone carefully.
A patient with substantial glenoid deficiency or a large engaging Hill-Sachs lesion can have a high recurrence risk after soft-tissue repair alone.
CT can be useful when bone loss is suspected.
Patients With Labral Tears
Not every labral tear requires surgery.
The labrum changes with age and repetitive activity.
The surgeon determines whether the tear creates instability, mechanical symptoms or pain that matches the patient's clinical presentation.
Young athletes with traumatic instability represent a different population from middle-aged adults with degenerative superior labral changes.
Overhead Athletes
Throwers, swimmers, volleyball players and racquet athletes place extreme demands on the shoulder.
The surgeon should distinguish adaptive changes from true pathology.
Surgical repair can affect motion that is important for performance.
Return to competitive overhead sport therefore requires both careful indication and highly sport-specific rehabilitation.
Patients With Biceps Disease
Persistent anterior shoulder pain can arise from the long head of the biceps.
Biceps tenodesis or tenotomy can be performed arthroscopically when the tendon is clearly an important pain generator.
The surgeon also evaluates the superior labrum and subscapularis because these structures interact closely with the biceps.
Patients With Frozen Shoulder
Most frozen shoulders eventually improve without surgery.
Arthroscopic release is reserved for severe persistent stiffness that remains functionally unacceptable after appropriate nonsurgical treatment.
Patients with diabetes can have a more resistant course.
After release, rehabilitation must begin promptly to preserve motion.
Patients With Advanced Arthritis
Advanced bone-on-bone glenohumeral arthritis is generally a poor indication for simple arthroscopy.
The surgeon can remove loose bodies or treat limited mechanical symptoms, but the operation cannot restore the entire worn cartilage surface.
If the primary problem is end-stage arthritis, arthroplasty may offer more durable pain relief.
Older Patients
Age alone does not prevent arthroscopy.
The important issue is whether the tissue and diagnosis make the intended procedure useful.
An older patient with a repairable symptomatic cuff tear can benefit from arthroscopic repair.
Another patient of the same age with severe cuff tear arthropathy may be better treated with reverse shoulder replacement.
Younger Patients
Arthroscopy is particularly attractive for joint-preserving surgery in younger adults.
Stabilization, labral repair and selected cuff procedures can restore anatomy without replacing the joint.
However, the surgeon should still avoid surgery for incidental imaging abnormalities.
The long-term benefit needs to justify the recovery.
Smokers
Smoking can negatively affect tendon and bone healing.
This is particularly important when rotator cuff or labral tissue is being secured to bone.
Stopping nicotine before surgery is strongly encouraged.
A simple diagnostic arthroscopy has less biological healing demand than a tendon repair, but smoking cessation still benefits anaesthesia and wound healing.
Diabetes
Diabetes can increase the risk of postoperative stiffness and can influence tendon healing.
Good glucose control is important.
Diabetes does not automatically prevent arthroscopic surgery.
The surgeon adjusts expectations and rehabilitation according to the patient's overall condition.
Before surgery
Establishing the Diagnosis
The surgeon begins with the history.
Pain location, instability episodes, traumatic injury, weakness, clicking and activity limitations provide important clues.
Night pain can occur with rotator cuff disease.
A sense of slipping or apprehension can indicate instability.
Mechanical catching can suggest labral pathology or loose bodies.
The surgeon then uses examination and imaging to determine whether arthroscopy is likely to help.
Shoulder Examination
The shoulder is examined for active and passive motion.
Rotator cuff strength is tested.
Instability maneuvers can evaluate the labrum and capsule.
The AC joint and biceps are palpated and stressed selectively.
The neck is examined because cervical nerve disease can mimic shoulder pain.
A complete examination reduces the risk of treating an imaging abnormality that is not actually causing symptoms.
X-Rays
X-rays remain important even though arthroscopy treats soft tissue.
They show arthritis, fractures, calcification and bone anatomy.
Instability radiographs can demonstrate certain bony defects.
AC joint degeneration can also be seen.
The surgeon should interpret these findings in combination with symptoms because radiographic changes can be asymptomatic.
MRI
MRI is one of the main preoperative tests.
It evaluates rotator cuff tendons, labrum, biceps, cartilage and muscle quality.
Contrast arthrography can sometimes improve evaluation of selected labral pathology, though it is not required for every patient.
Imaging helps the surgeon plan which instruments, anchors and procedures may be needed.
Ultrasound
Ultrasound is particularly useful for rotator cuff and biceps evaluation.
It can show tendon motion in real time.
High-quality ultrasound can identify many full- and partial-thickness cuff tears.
It is operator dependent.
Labral and deep intra-articular pathology are generally better characterized with other imaging methods.
CT
CT provides detailed bone assessment.
It is particularly valuable for recurrent shoulder instability when glenoid or humeral-head bone loss can influence the surgical strategy.
Three-dimensional reconstruction can help quantify defects.
A patient with major bone loss may need a different operation from an isolated arthroscopic Bankart repair.
Trial of Nonsurgical Treatment
Many shoulder conditions should initially be treated without surgery.
Physical therapy can improve rotator cuff strength, scapular mechanics and mobility.
Medication can help control symptoms.
Activity modification can reduce painful loading.
Injections can be used selectively.
Arthroscopy becomes more appropriate when a structural problem remains sufficiently symptomatic despite reasonable conservative care or when an acute injury has a strong indication for repair.
Physical Therapy Before Surgery
Preoperative rehabilitation can improve motion and strengthen surrounding muscles.
A stiff shoulder can be more difficult to rehabilitate after tendon repair.
However, not every traumatic tear should be delayed for prolonged therapy.
The balance depends on the diagnosis.
Patients should follow the surgeon's plan rather than assuming that everyone needs a fixed number of therapy sessions before arthroscopy.
Corticosteroid Injections
Corticosteroid injections can reduce inflammation and pain.
They do not mechanically repair a torn tendon or labrum.
Repeated injections around damaged tendons require caution.
Timing before surgery is also relevant because recent injections can influence infection and tissue-healing considerations.
Patients should provide the exact date and location of prior injections.
Preparing for Anaesthesia
Most shoulder arthroscopy is performed under general anaesthesia.
An interscalene nerve block is frequently added.
The anaesthesia team reviews respiratory problems, heart disease, allergies and previous anaesthetic complications.
Because the interscalene block can temporarily affect nearby nerves and breathing mechanics, individual risk assessment is important.
Blood Tests
Young healthy patients undergoing routine outpatient arthroscopy may need limited laboratory testing.
Older or medically complex patients can require more extensive assessment.
The hospital follows its own preoperative protocol.
Testing should be tailored to health status rather than performed solely because the surgery involves an operating room.
Medications
The surgeon needs a complete list of prescription medication, over-the-counter medication and supplements.
Anticoagulants and antiplatelet drugs require individualized instructions.
Patients should not stop important medication without advice.
Diabetes medication also commonly requires adjustments around fasting and anaesthesia.
Smoking
Nicotine cessation is especially important for repairs that depend on tendon-to-bone or labrum-to-bone healing.
Smoking can impair biological healing.
Stopping before surgery also benefits respiratory and wound risk.
The earlier cessation begins, the more useful it can be.
Planning the Sling
Patients should know whether their specific procedure requires a sling.
A diagnostic arthroscopy can require little more than comfort use.
A rotator cuff or labral repair commonly requires several weeks of protection.
The patient should not assume that another person's sling duration applies to their procedure.
Planning Clothing
Loose front-opening shirts are practical.
Patients should avoid clothing that requires active overhead movement immediately after surgery.
A sling can make ordinary dressing difficult.
Preparing suitable clothes before the operation reduces frustration.
Home Preparation
Food, medication and commonly used objects should be positioned where they can be reached with the unoperated arm.
Patients living alone may require temporary assistance.
If the dominant arm is being operated on, writing, computer work and personal care can be particularly awkward.
Sleeping Preparation
Many patients find it uncomfortable to lie flat after shoulder surgery.
A recliner, wedge pillow or multiple bed pillows can support the upper body.
A pillow under the elbow can reduce tension.
The sleeping arrangement should be prepared before surgery.
Work Planning
Time off work should be planned according to the actual arthroscopic procedure.
A person undergoing diagnostic arthroscopy can sometimes return to desk work within days.
A rotator cuff repair can prevent manual work for months.
The patient's job demands are therefore as important as the word “arthroscopy.”
Planning Physiotherapy
The therapist needs to know exactly what was done.
After a capsular release, early movement is essential.
After a rotator cuff repair, movement can be deliberately restricted.
After a stabilization procedure, external rotation can be limited initially.
A generic shoulder programme can therefore be inappropriate.
How the operation is performed
Shoulder Arthroscopy is performed by inserting a narrow camera through a small portal and using additional keyhole instruments through other portals to inspect and treat shoulder structures while viewing the operation on a monitor.
The surgeon first evaluates the joint systematically.
The exact surgical steps then depend on the diagnosed problem.
Repair can involve suture anchors, sutures, shavers, radiofrequency devices, burrs and other specialized arthroscopic instruments.
Anaesthesia
General anaesthesia is common because the operation requires precise positioning and can last from less than an hour to several hours.
A regional interscalene block can provide substantial postoperative pain relief.
The block can leave the arm temporarily numb and weak.
Patients receive instructions on protecting the numb limb until sensation returns.
Beach-Chair Position
One common position places the patient semi-seated.
The surgeon can move the arm freely.
Anatomical orientation resembles the upright position.
The anaesthesia team carefully manages blood pressure and positioning.
Pressure points are protected.
Lateral Decubitus Position
Another common technique positions the patient on the opposite side.
Gentle traction can be applied to the operated arm to open the joint.
This creates excellent access to several regions.
Both beach-chair and lateral positions are established approaches.
The surgeon's experience and planned procedure usually determine the choice.
Exam Under Anaesthesia
Before inserting the camera, the surgeon can assess range of motion and stability while muscles are relaxed.
This is particularly useful in instability and frozen shoulder surgery.
The findings are interpreted together with the patient's awake examination.
Forceful manipulation is avoided unless it forms part of a carefully planned procedure.
Creating the First Portal
A small posterior incision is commonly created.
A blunt instrument enters the joint.
The arthroscope is then inserted.
The surgeon confirms the position before continuing.
Sterile fluid expands the joint and clears the visual field.
Arthroscopic Fluid
Fluid is continuously pumped through the shoulder.
It improves visualization and helps control minor bleeding.
Pressure is carefully managed.
Some fluid inevitably moves into surrounding soft tissue.
Excessive extravasation can produce substantial swelling, which is why surgical time, pump pressure and soft-tissue appearance are monitored.
Diagnostic Survey
The surgeon systematically inspects the joint rather than going directly to one MRI finding.
The humeral head cartilage, glenoid cartilage, labrum, biceps tendon, subscapularis, supraspinatus and capsule are examined.
A probe can test whether tissue is stable.
The surgeon can then confirm the preoperative plan or modify it based on direct findings.
Additional Portals
Working portals are created according to the area being treated.
A needle can first identify the safest trajectory.
Small cannulas allow instruments and sutures to pass repeatedly without damaging surrounding soft tissue.
Portal placement is important because nerves and blood vessels surround the shoulder.
Arthroscopic Shaver
A powered shaver removes frayed tissue, inflamed bursa or unstable fragments.
Different blade shapes and sizes are available.
The surgeon uses suction and direct visualization.
Healthy tissue should be preserved.
The goal is controlled treatment rather than simply removing everything that looks irregular.
Radiofrequency Instrument
Radiofrequency devices can remove soft tissue and control bleeding.
They are useful for capsular work, synovectomy and visualization.
Excessive heat can damage tissue.
The surgeon therefore uses the device selectively and maintains adequate fluid circulation.
Arthroscopic Burr
A burr removes bone when necessary.
It can be used for selected acromioplasty, distal clavicle excision or preparation of a tendon footprint.
Removing too much bone can create its own problems.
Modern shoulder arthroscopy increasingly emphasizes preservation of anatomy unless bone removal has a clear purpose.
Suture Anchors
Anchors provide fixation in bone.
They are used for rotator cuff, labral and other soft-tissue repairs.
Different designs include all-suture, polymer, biocomposite and other materials.
High-strength sutures or tapes pass through the tissue.
Anchor material is less important than proper indication, positioning and tissue quality.
Arthroscopic Rotator Cuff Repair Technique
The surgeon examines the tear from the joint and subacromial sides.
Adhesions are released when necessary.
The greater tuberosity is prepared.
Anchors are placed in bone.
Sutures are passed through the tendon.
The tendon is secured against the bone using single-row, double-row or another repair configuration according to tear size and tissue quality.
Arthroscopic Bankart Repair Technique
The detached labrum is mobilized.
The glenoid rim is prepared to create a healing surface.
Anchors are inserted around the anterior-inferior glenoid.
Sutures capture the labrum and capsule.
Tying or securing the sutures restores the labrum to the rim and tightens the capsule.
The shoulder is then assessed for stability.
SLAP Repair Technique
The superior labrum is evaluated to confirm that repair is truly indicated.
The glenoid surface is prepared.
Small anchors are placed near the superior labrum.
Sutures secure the labrum while protecting the biceps anchor appropriately.
Because superior labral abnormalities are common with aging, the surgeon should repair only clinically meaningful unstable lesions.
Biceps Tenodesis Technique
The diseased biceps is detached from its superior labral origin.
It is fixed to the humerus lower down.
Different techniques use anchors, screws or other fixation.
The exact location can be above or below the pectoralis depending on technique.
The fixation needs time to heal before resisted biceps loading.
Biceps Tenotomy Technique
The tendon is released at its origin.
No new fixation is required.
The tendon retracts to a resting position.
The procedure is relatively quick.
The trade-offs include possible cosmetic contour change and cramping in some patients.
Capsular Release Technique
The tight capsule is divided using controlled arthroscopic instruments.
The surgeon releases the areas necessary to restore motion while protecting nearby nerves.
The arm can then be gently moved to assess improvement.
The key postoperative priority is maintaining regained motion.
Therapy therefore begins much earlier and more aggressively than after a tendon repair.
Distal Clavicle Excision Technique
The surgeon enters the subacromial region and identifies the AC joint.
A small portion of the distal clavicle is removed.
The objective is to eliminate painful bone contact while preserving important stabilizing structures.
Removing excessive bone can create AC instability.
Accurate resection is therefore more important than maximizing the amount removed.
Loose Body Removal
Loose fragments are located with the camera.
A grasper removes them through a portal.
Large fragments may require enlargement of an incision.
The joint is then inspected for the source of the fragment.
If advanced arthritis is present, the surgeon explains that loose-body removal may relieve mechanical symptoms without curing the underlying degeneration.
Synovectomy Technique
Inflamed synovial tissue is removed with shavers and radiofrequency instruments.
The surgeon works carefully around cartilage and tendons.
Samples can be sent to pathology when diagnosis is uncertain.
Infection or unusual synovial disorders can also require microbiological or histological evaluation.
Closing the Portals
The instruments and fluid are removed.
The small incisions are closed with sutures, adhesive strips or another method.
Sterile dressings are applied.
The arm is placed in a sling when indicated.
Swelling from irrigation fluid can make the shoulder appear larger immediately after surgery and generally decreases as the fluid is absorbed.
How Long Does a Shoulder Arthroscopy Take?
A Shoulder Arthroscopy can take approximately 30 minutes to several hours depending on what is performed.
A diagnostic procedure or limited debridement can be relatively short.
A rotator cuff repair or stabilization procedure often takes longer.
Multiple combined procedures add operating time.
As a general CMS value, approximately 60 minutes is reasonable for generic shoulder arthroscopy, but this should always be accompanied by the explanation that complex repair can take two to three hours or more.
How Long Is Shoulder Arthroscopy Surgery?
Patients searching “how long is shoulder arthroscopy surgery?” should distinguish the actual operation from total hospital time.
The patient arrives before surgery for preparation and anaesthesia.
After the operation, time is spent in recovery while pain, nausea and alertness are monitored.
A one-hour operation can therefore still involve much of the day at the surgical facility.
Hospital stay
Is Shoulder Arthroscopy Outpatient?
Most Shoulder Arthroscopy is performed as outpatient or day-case surgery.
Patients generally return home the same day once they are awake, medically stable and able to manage pain and nausea.
Selected people can stay overnight because of medical conditions, late surgical timing, uncontrolled symptoms or complex procedures.
Recovery Room
After surgery, the patient moves to a monitored recovery area.
Blood pressure, oxygen, pain and nausea are assessed.
The operated arm can be numb if an interscalene block was used.
The shoulder can appear swollen because of arthroscopic fluid.
The swelling typically decreases after surgery.
Pain After Shoulder Arthroscopy
Pain varies dramatically according to procedure.
Diagnostic arthroscopy or simple debridement can cause relatively mild short-term soreness.
Rotator cuff repair can be significantly painful during the first several days.
A nerve block can make the immediate postoperative period much easier.
Patients should begin prescribed oral medication according to instructions as the block wears off rather than waiting for severe pain.
Interscalene Nerve Block
The interscalene block numbs nerves supplying much of the shoulder.
It can provide strong analgesia for several hours.
The arm may temporarily feel heavy or completely numb.
Temporary effects involving nearby nerves can occur.
The anaesthetist discusses these risks individually.
Sling After Surgery
Sling requirements depend entirely on what was performed.
A diagnostic arthroscopy may use a sling only for comfort or not at all.
Simple debridement can require brief use.
Labral and rotator cuff repairs generally need much longer protection.
The discharge documentation should state the exact sling plan.
Wound Care
Arthroscopy creates several small portal wounds.
They are covered with dressings.
Minor blood-stained drainage can occur early.
Increasing redness, pus, fever or persistent drainage should be reported.
The patient should follow the facility's showering and dressing instructions.
Eating and Drinking
Patients begin drinking once nausea is controlled.
Food is introduced gradually.
General anaesthesia can temporarily reduce appetite.
Good hydration is encouraged unless a medical condition requires fluid restriction.
Going Home
An adult should take the patient home after general anaesthesia.
The patient should not drive.
Medication, sling and wound instructions should be understood before discharge.
The patient should know who to contact if pain becomes uncontrolled or the hand develops unexpected color, temperature or neurological changes.
Recovery
The recovery time after Shoulder Arthroscopy depends primarily on what is treated rather than on the arthroscopy itself.
A patient undergoing a diagnostic scope can return to many activities within days.
A patient undergoing capsular release may begin aggressive mobility almost immediately.
A patient having rotator cuff repair follows almost the opposite strategy, protecting the repair for weeks before active strengthening.
For this reason, generic online statements that shoulder arthroscopy takes “a few weeks to recover” can be seriously misleading.
Arthroscopy of the Shoulder Recovery Time
For a simple diagnostic procedure or minor debridement, recovery can be relatively rapid.
Pain and swelling may improve over several days.
Normal movement can return as comfort permits.
Desk work can sometimes resume within days.
For a more substantial but non-reconstructive arthroscopy such as selected bursectomy or distal clavicle excision, recovery commonly extends over several weeks.
Labral stabilization or tendon repair often requires four to six months or longer for high-demand activities.
How Long Is Recovery From Shoulder Arthroscopy?
A practical answer is:
A diagnostic arthroscopy can recover in days to a few weeks.
A simple debridement or bursectomy commonly requires several weeks.
A capsular release can regain useful function over weeks but needs intensive early therapy.
A labral or instability repair commonly requires several months.
A rotator cuff repair often takes four to six months for major function, with improvement continuing for six to twelve months.
This range is why the procedure performed must always be named alongside the phrase Shoulder Arthroscopy.
First 24 Hours
The nerve block can keep the arm numb.
Patients rest with the shoulder supported.
Finger, wrist and elbow movement is usually encouraged where appropriate.
Ice is used according to instructions.
The patient should avoid testing shoulder strength while numb.
Days 2–7
Postoperative swelling begins to settle.
Pain becomes easier to manage.
The patient starts the exercises permitted for the procedure.
Simple arthroscopy patients can move the shoulder more freely.
Repair patients remain protected.
The portal dressings are monitored for drainage.
Weeks 1–2
The first postoperative appointment commonly reviews wound healing and surgical findings.
This is an important visit because the final rehabilitation plan is based on what the surgeon actually saw and treated.
An operation that was expected to be simple can occasionally involve an unexpected repair, changing recovery substantially.
Weeks 2–6
Recovery diverges strongly according to procedure.
A debridement patient can be returning to normal activity.
A frozen-shoulder patient can be working intensively on motion.
A labral or cuff-repair patient can still be in a sling.
The same time point therefore has very different meanings across shoulder arthroscopy procedures.
How Long Do You Wear a Sling After Shoulder Arthroscopy?
Sling duration can range from no routine sling after diagnostic arthroscopy to approximately 2–6 weeks or longer after tissue repair.
For comfort-only procedures, the sling is removed quickly to encourage movement.
After labral repair, the sling commonly protects the capsule and repaired labrum for several weeks.
After rotator cuff repair, approximately four to six weeks is common, with larger repairs sometimes protected longer.
The exact instructions from the surgeon take priority.
Sling After Diagnostic Arthroscopy
A sling may be used only for comfort.
Some centers do not require one routinely.
The patient can begin using the arm as pain allows.
This rapid recovery should not be extrapolated to repaired structures.
Sling After Labral Repair
Labral tissue needs time to heal back to the glenoid.
A sling is therefore commonly maintained for several weeks.
External rotation and elevation can also be limited.
The rehabilitation programme gradually restores motion while protecting the repaired capsule and labrum.
Sling After Rotator Cuff Repair
The sling protects the repaired tendon.
An abduction pillow can position the arm away from the body to reduce tension.
Four to six weeks is common, but tear size and tissue quality influence duration.
Sling removal is usually gradual.
Passive Motion
Passive motion means that the repaired shoulder is moved without strong active muscle contraction.
Another person, the opposite arm or a device provides assistance.
Passive exercises are frequently used after rotator cuff repair.
The aim is to maintain selected mobility while limiting load on the tendon.
Active-Assisted Motion
Active-assisted exercises bridge passive and active movement.
The recovering muscles begin contributing while the arm receives support.
This phase is especially important after repair surgery.
The therapist monitors compensation and protects restricted directions.
Active Motion
Active motion requires the patient's muscles to move the arm independently.
It returns early after simple debridement but is delayed after many repairs.
A patient should not assume that painless movement is safe simply because they can physically lift the arm.
Biological healing can remain incomplete.
Strengthening
Strengthening follows the healing needs of the procedure.
After debridement, light strengthening can begin relatively early.
After a cuff repair, meaningful resisted exercise is usually delayed until tendon healing has progressed.
After stabilization, strength is introduced gradually while restoring controlled range.
Pain During Recovery
Pain should generally follow a downward trend.
Therapy can create temporary muscular soreness.
Night discomfort is common after shoulder surgery.
A sudden large increase in pain after a fall or lifting incident deserves assessment.
New weakness can be particularly important after tendon repair.
Swelling
Shoulder and upper-arm swelling can occur because arthroscopy uses irrigation fluid.
Some fluid can track into the chest wall.
Most postoperative swelling resolves as fluid is absorbed.
Rapidly progressive neck or chest swelling, breathing difficulty or other major symptoms require urgent evaluation because severe fluid extravasation is a rare but potentially serious complication.
Bruising
Bruising can extend down the arm.
Gravity moves blood and fluid away from the surgical site.
This can look dramatic without indicating a problem.
Increasing tense swelling or neurological symptoms should still be assessed.
Sleeping After Shoulder Arthroscopy
Many patients sleep partly upright initially.
A recliner or wedge pillow can be useful.
The elbow can be supported with a pillow.
Repair patients frequently sleep in the sling during the protection period.
A simple arthroscopy patient can return to ordinary sleep positions much sooner.
When Can You Sleep on the Operated Shoulder?
Direct pressure is usually uncomfortable early.
The timing depends on procedure.
After simple arthroscopy, side sleeping can return as wounds and pain permit.
After repair surgery, many patients wait considerably longer.
The patient should avoid forcing a position simply to meet a calendar date.
Showering
The shoulder can be showered once the wound and dressing protocol allows it.
The small portal incisions should not be soaked until healed.
Baths, pools and hot tubs are delayed until the wounds are fully closed.
Repair patients should avoid actively raising the arm simply to wash.
Dressing
Front-opening clothing simplifies early recovery.
The operated arm is placed into the sleeve first.
A sling can make tight clothing difficult.
After repair, dressing strategies should avoid prohibited shoulder positions.
Driving
Driving should not resume while the arm is immobilized in a sling, while sedating pain medication is being used or before the patient can safely control the vehicle.
A simple arthroscopy patient can return sooner than a cuff-repair patient.
Local insurance and licensing requirements can also matter.
The ability to turn a steering wheel comfortably in a clinic does not guarantee safe emergency reaction.
How Long Off Work After Shoulder Arthroscopy?
Time away from work depends on the procedure and the job.
After diagnostic arthroscopy or simple debridement, a desk-based worker can sometimes return within several days to approximately one week.
After more painful procedures, one to three weeks can be more realistic for office work.
After rotator cuff or labral repair, desk work can sometimes resume relatively early if the arm remains protected, but manual work involving lifting, pushing, pulling or overhead use can require three to six months or longer.
The surgeon should provide restrictions based on actual job duties.
Desk Work
Computer use can resume when pain allows and the arm can be supported.
A sling makes prolonged typing difficult.
Working from home can permit an earlier gradual return.
Driving restrictions can delay office attendance even when keyboard work itself is possible.
Manual Work
Manual workers need enough shoulder strength to perform tasks safely.
A laborer cannot return simply because the skin wounds have healed.
Tendon repair, stabilization and other reconstructions can remain vulnerable for months.
Modified duty is often useful.
Heavy Overhead Work
Overhead work is among the last occupational activities to return after cuff and labral surgery.
The shoulder needs strength, endurance and control.
Repeated overhead loading creates greater force than ordinary waist-level work.
Return should be based on function as well as time.
Return to the Gym
Lower-body exercise can often resume early if the shoulder is protected.
Upper-body training depends on procedure.
A diagnostic arthroscopy patient can progress relatively quickly.
A cuff-repair patient must avoid heavy resistance for months.
Bench pressing, pull-ups and overhead pressing are not universal early rehabilitation exercises.
Running
Running can return when arm movement and fall risk are acceptable.
A patient in a sling may find running uncomfortable and less balanced.
After major repair, the concern includes accidental falls.
Walking and stationary cardiovascular exercise are often easier early alternatives.
Swimming
Swimming demands repetitive shoulder elevation and rotation.
It therefore returns later than ordinary daily activity.
A debridement patient can resume sooner than a labral or cuff-repair patient.
A gradual swimming programme should begin only after adequate motion and strength are restored.
Golf
Putting can return before full swings.
A golf swing creates rotational force through both shoulders.
The patient should regain adequate motion and strength before progressing.
Repair procedures need more healing time than simple arthroscopy.
Tennis and Racquet Sports
Groundstrokes are usually less demanding than serving.
Overhead serves place significant load on the shoulder.
Return depends on repair type and sport level.
Competitive players require a more structured progression than recreational doubles players.
Throwing
Throwing is one of the highest-demand shoulder activities.
After stabilization or labral repair, an interval throwing programme commonly begins only after motion, strength and dynamic stability meet criteria.
Throwing athletes can require many months to recover fully.
Returning to play is different from returning to preinjury performance.
Return to Sport After Rotator Cuff Arthroscopy
Rotator cuff repair requires long biological healing.
Recreational sport often returns over several months.
Overhead sport can require six months or longer.
Recent systematic evidence confirms that pain and clinical scores continue improving substantially between three months, six months and one year after arthroscopic cuff repair.
Patients should therefore not judge the final result early.
Intimacy After Shoulder Arthroscopy
Sexual activity can resume when pain is controlled and the shoulder can remain within restrictions.
After repair, the operated arm should not support body weight.
Positions requiring forceful extension, rotation or reaching behind the body should be avoided early.
Simple arthroscopy generally permits faster return.
Scar Appearance
Arthroscopy commonly leaves several small portal scars.
They can initially appear red or raised.
Scars usually soften over time.
Sun protection reduces pigmentation changes.
A small scar does not indicate that the internal operation was small.
When Is Full Recovery Reached?
Full recovery depends on the goal.
A diagnostic arthroscopy patient can feel normal in a relatively short period.
A cuff-repair patient can continue improving for a year.
A throwing athlete can regain daily function long before recovering sport-specific performance.
The surgeon should therefore define recovery in terms of pain, motion, work and sport separately.
Recovery timeline
- Control pain, protect any repaired tissue and begin procedure-appropriate movement.1Control pain, protect any repaired tissue and begin procedure-appropriate movement.
Days 0–14
Simple arthroscopy patients can progressively use the arm as comfort permits. Patients with rotator cuff or labral repair use a sling and follow movement limits. Hand, wrist and permitted elbow motion usually begin immediately. Wounds are monitored while postoperative swelling resolves.
- Restore safe mobility while respecting tissue heali2Restore safe mobility while respecting tissue heali
Weeks 2–6
Debridement and diagnostic patients can already be close to ordinary activity. Capsular-release patients continue frequent range-of-motion exercises. Repair patients remain more protected, often using a sling and passive or assisted exercises only. The exact protocol now depends almost entirely on the procedure performed.
- Transition toward active shoulder control.3Transition toward active shoulder control.
Weeks 6–12
Most patients with repair begin increasing active-assisted and active motion according to the surgeon's protocol. Simple arthroscopy patients are usually strengthening and returning to broader activity. The therapist focuses on scapular mechanics and smooth shoulder movement.
- Rebuild strength, endurance and occupational or recreational function.4Rebuild strength, endurance and occupational or recreational function.
Months 3–6
Labral and cuff-repair patients advance strengthening. Sport-specific rehabilitation can begin when appropriate. Manual workers progressively reintroduce lifting. Simple arthroscopy patients have generally completed formal recovery well before this stage.
- Reach mature recovery after major arthroscopic reconstruction.5Reach mature recovery after major arthroscopic reconstruction.
Months 6–12
Large cuff repairs, complex instability surgery and overhead athletes can continue improving throughout this period. Advanced strength, throwing and sport-specific training progress according to objective function rather than time alone.
Outcomes and success rates
How Successful Is Shoulder Arthroscopy?
There is no useful single success rate for Shoulder Arthroscopy because the term includes many different operations.
A diagnostic arthroscopy is judged by whether it accurately identifies pathology.
Rotator cuff repair is judged by pain, function and tendon healing.
Bankart repair is judged partly by stability and recurrence.
Capsular release is judged by motion.
Biceps surgery is judged largely by pain relief.
The outcome should therefore always be discussed for the procedure being performed.
Outcomes After Simple Arthroscopy
Patients undergoing minor debridement, loose-body removal or another limited procedure often recover quickly.
Pain improvement depends on whether the removed tissue was actually the source of symptoms.
Arthroscopy cannot compensate for advanced arthritis or major untreated instability.
Correct diagnosis is therefore central to success.
Rotator Cuff Repair Outcomes
Arthroscopic rotator cuff repair generally improves pain and function in appropriately selected patients.
Structural healing is influenced by age, tear size, tissue quality, retraction and fatty degeneration.
A small acute tear has a different prognosis from a chronic massive tear.
Recent systematic evidence shows that pain improves substantially within the first months while range and broader clinical recovery continue through six months and one year.
Labral Repair Outcomes
Arthroscopic stabilization can provide excellent results in patients with appropriate anatomy.
Recurrence risk increases when bone loss is underestimated, in young contact athletes and in other high-risk instability patterns.
The surgeon should therefore evaluate the bony anatomy rather than treating every dislocation with the same soft-tissue repair.
SLAP Repair Outcomes
Results vary according to age, sport and associated pathology.
Young patients with a clear traumatic superior labral lesion can benefit.
Older patients with biceps-related pain can do better with biceps tenodesis than formal SLAP repair in many circumstances.
The operation should therefore reflect the patient's actual pathology rather than the MRI label alone.
Capsular Release Outcomes
Arthroscopic capsular release can improve severe refractory stiffness.
Postoperative therapy is crucial.
Motion gained during surgery can be lost if rehabilitation is inadequate.
Patients with diabetes or long-standing stiffness can have a slower recovery.
The procedure treats the mechanical contracture but still requires prolonged participation in therapy.
Distal Clavicle Excision Outcomes
Results are generally favorable when the AC joint is correctly identified as the pain generator.
Poorer outcomes can occur when surgery is performed for an incidental radiographic abnormality.
Accurate diagnosis through examination and sometimes targeted injection improves patient selection.
Subacromial Decompression Outcomes
Routine decompression for nonspecific atraumatic subacromial pain has become controversial.
High-quality studies have challenged the assumption that acromial bone removal produces meaningful additional benefit in many patients without another structural indication.
Current practice should therefore emphasize careful selection rather than automatically treating “impingement” with surgery.
Persistent Pain After Arthroscopy
Pain can persist when the original diagnosis was incomplete, tissue fails to heal or arthritis is more advanced than expected.
Stiffness can also become a dominant postoperative problem.
Nerve disease or cervical spine pathology can contribute.
Persistent pain does not automatically mean the arthroscopy was technically unsuccessful, but it deserves reevaluation.
Repeat Arthroscopy
Some conditions can be treated with another arthroscopic procedure.
Examples include stiffness, selected recurrent labral pathology or certain cuff retears.
Revision surgery is generally less predictable than primary surgery.
The surgeon needs to understand why the original treatment failed before repeating it.
Conversion to Open Surgery
Occasionally an arthroscopic procedure cannot be completed safely or effectively through portals.
The surgeon can convert to a larger open approach.
This is uncommon for routine procedures but should be included in consent when relevant.
Conversion is a surgical strategy rather than automatically a complication.
Long-Term Results
Long-term outcome is determined by the underlying condition.
A repaired traumatic instability lesion can remain stable for years.
A degenerative cuff can develop additional tearing over time.
Arthroscopy does not stop normal aging of cartilage, tendons or bone.
A good operation treats the current mechanical problem while preserving as much normal tissue as possible.
Implants and technology
Arthroscope
The arthroscope is the central technology.
Modern cameras produce high-resolution images that are enlarged on a monitor.
Different viewing angles help the surgeon inspect difficult areas.
Image quality can make subtle cartilage and tendon pathology easier to evaluate.
Arthroscopic Cannulas
Cannulas create controlled pathways through the soft tissues.
Instruments and sutures can pass through them repeatedly.
This reduces unnecessary trauma to the skin and surrounding tissues.
Different portal positions and cannula sizes are selected according to the procedure.
Suture Anchors
Suture anchors secure soft tissue to bone.
They are central to rotator cuff and labral repair.
Designs include all-suture, biocomposite and polymer anchors.
Some are knotless, while others use traditional sutures tied arthroscopically.
The appropriate construct depends on anatomy and repair requirements.
Knotless Anchors
Knotless systems secure sutures without conventional arthroscopic knots.
They can simplify certain labral and cuff repair configurations.
They are not inherently superior in every case.
Repair quality depends on tissue, anchor position and overall construct.
Suture Tape
Broader tapes can distribute load over a larger area of tendon.
They are commonly used in rotator cuff repair.
Biomechanical strength does not guarantee biological healing.
The tendon still needs time to integrate with bone.
Arthroscopic Shavers
Motorized shavers remove damaged tissue and bursa.
They have interchangeable blades.
Suction draws tissue toward the blade.
The surgeon controls exactly where tissue is removed while viewing the process on the monitor.
Radiofrequency Devices
These tools can remove soft tissue and control bleeding.
They are useful for capsular work and maintaining a clear field.
Thermal injury is a potential concern if they are used excessively or too close to sensitive structures.
Arthroscopic Burrs
Burrs reshape bone.
They can be used during acromioplasty, distal clavicle excision and selected bone preparation.
Modern practice aims to remove only the amount required for the actual pathology.
Fluid Pump Systems
A pump controls sterile fluid pressure inside the shoulder.
Adequate pressure expands the joint and limits bleeding.
Excessive pressure can increase soft-tissue swelling.
The surgical team monitors pressure, procedure duration and tissue distension.
High-Definition Monitors
Modern monitors improve visualization of fine tissue structures.
The surgeon can see suture passage, cartilage surfaces and tear margins in detail.
This is particularly useful in complex repairs.
The technology improves visualization but does not replace surgical judgment.
Arthroscopic Suture-Passing Devices
Specialized instruments pass sutures through rotator cuff and labral tissue.
Some grasp, penetrate or shuttle sutures.
These devices allow complex repairs through narrow portals.
The surgeon chooses the device according to tissue thickness and angle.
Biceps Fixation Devices
Tenodesis can use anchors, screws or other fixation.
Different implants are designed for specific locations on the humerus.
No single method is ideal for every patient.
The surgeon considers tendon quality, bone and preferred technique.
Biologic Augmentation
PRP, collagen scaffolds and other biological products are sometimes used with cuff repair.
Evidence varies according to product and indication.
They should be considered adjuncts rather than replacements for correct mechanical repair.
Marketing claims should not imply guaranteed healing.
Dermal Allograft
Large or revision cuff tears can occasionally be reinforced with dermal graft.
The graft adds structural support.
This is more complex than routine Shoulder Arthroscopy.
The patient should know when augmentation is expected because it influences cost and rehabilitation.
Bioinductive Scaffold
Collagen-based bioinductive implants can be used for selected partial tears or as repair augmentation.
Evidence continues to evolve.
These products are not required for every cuff tear.
The indication should be specific.
Navigation and Robotics
Navigation and robotic assistance currently play a much smaller role in Shoulder Arthroscopy than in joint replacement.
Arthroscopy relies heavily on direct camera visualization and surgeon-controlled instruments.
Computerized technologies can evolve in the future, but they are not necessary for high-quality routine arthroscopic shoulder surgery.
Risks and how they are managed
All surgery carries risk. Partner hospitals follow enhanced-recovery and infection-prevention protocols, and your surgeon will discuss the risks specific to your case before consent.
- Infection: Infection after Shoulder Arthroscopy is uncommon but can involve superficial portal wounds or deeper structures. Persistent pain and stiffness can sometimes be the only clues to a low-grade shoulder infection.
- Shoulder stiffness: Scar formation and postoperative pain can limit motion. Risk depends partly on the procedure and preoperative shoulder condition.
- Nerve injury: Nerves can be irritated by surgical instruments, traction, positioning or regional anaesthesia. Most temporary neuropraxias recover, but permanent injury is possible.
- Blood-vessel injury: Major vascular injury is rare but potentially serious.
- Bleeding or hematoma: Significant bleeding is uncommon, although bruising is common.
- Fluid extravasation: Arthroscopic irrigation fluid can enter the surrounding tissues. Most swelling resolves spontaneously, while major neck or chest swelling and airway compromise are rare serious complications.
- Blood clots: Deep-vein thrombosis and pulmonary embolism are uncommon after shoulder arthroscopy but remain possible.
- Anaesthetic complications: General anaesthesia and regional nerve blocks can cause respiratory, cardiovascular or neurological complications.
- Temporary numbness from nerve block: The arm can remain numb and weak for hours after an interscalene block.
- Persistent shoulder pain: Surgery cannot guarantee complete pain relief, particularly when multiple pain sources exist.
- Failure of rotator cuff repair: A repaired tendon can fail to heal or can tear again.
- Failure of labral repair: The labrum can fail to heal or instability can recur.
- Recurrent dislocation: Shoulder stabilization does not completely eliminate future instability, particularly when bone loss or high-risk sport is present.
- Anchor pullout: A suture anchor can lose fixation, particularly in weak bone.
- Suture failure: Sutures can break or cut through poor-quality tissue.
- Biceps tenodesis failure: A fixed biceps tendon can lose fixation or remain painful.
- Popeye deformity: The biceps muscle can migrate distally after tenotomy or failed tenodesis.
- Cartilage injury: Instruments can accidentally damage joint cartilage.
- Iatrogenic tendon injury: Nearby tendons can be damaged during complex procedures.
- Instrument breakage: Arthroscopic instruments or implant components can rarely break.
- Skin or pressure injury: Positioning and traction can create pressure-related problems.
- Postoperative swelling: Shoulder, chest or arm swelling is common to some degree because of irrigation fluid.
- Complex regional pain syndrome: Persistent disproportionate pain and autonomic changes can rarely develop.
- Need for repeat surgery: Failure, stiffness or recurrent instability can eventually require another procedure.
- Conversion to open surgery: The surgeon can occasionally need a larger incision to complete treatment safely.
Alternatives
- Physical therapy: Appropriate for many rotator cuff, impingement, instability and stiffness problems before surgery is considered.
- Activity modification: Avoiding repetitive painful movements can reduce symptoms while tissue recovers.
- Pain medication: Acetaminophen, anti-inflammatory medication when medically appropriate and other analgesics can help manage symptoms.
- Corticosteroid injection: Can reduce inflammation and pain for selected conditions but does not repair torn tendons or detached labrum.
- Ultrasound-guided procedures: Selected calcific deposits or other conditions can sometimes be treated without arthroscopy.
- Continued observation: Appropriate when symptoms remain acceptable and the condition is not likely to deteriorate urgently.
- Open rotator cuff repair: Used selectively when arthroscopic repair is impractical or another open reconstruction is required.
- Open stabilization or bone-block procedure: Significant instability-related bone loss can require procedures such as Latarjet or another bone reconstruction rather than isolated arthroscopic repair.
- Shoulder replacement: Advanced arthritis or cuff tear arthropathy can be better treated with anatomic or reverse shoulder arthroplasty.
- Manipulation under anaesthesia: Can be considered for selected frozen shoulders, sometimes with arthroscopic capsular release.
- Tendon transfer: Selected irreparable rotator cuff tears can require reconstruction rather than simple arthroscopy.
- Continued nonsurgical rehabilitation: Many shoulder conditions improve without surgery, particularly when weakness or instability is limited.
What Shoulder Arthroscopy costs
The contracted Turkey partner package next to approved self-pay benchmarks. Benchmarks are 20th–80th percentile ranges of approved records, normalised to USD.
Turkey package
$3,000 – $5,500
United States self-pay
$9,900 – $24,800
United Kingdom self-pay
$4,400 – $13,100
Germany self-pay
$3,850 – $11,550
Typical self-pay range by country
Surgeons who perform Shoulder Arthroscopy
All surgeonsHospitals offering this procedure
Antalya Yaşam Hospital
Private hospital in Muratpaşa, Antalya, with an orthopedics and traumatology department
BHT Clinic Istanbul Tema Hospital
Large private hospital in Atakent, Küçükçekmece, with an orthopedics and traumatology unit
Biruni University Hospital
University hospital in Küçükçekmece, Istanbul, with a published orthopedics and traumatology department
Çankaya Hospital for Orthopedic Care
Çankaya Hospital for Orthopedic Care is an orthopedic hospital in central Ankara with robotic-arm assisted surgery
Sources and references
Peer-reviewed guidance and institutional sources used to write and review this page.
- 01General description of arthroscopy, use of a small camera through small incisions, diagnostic assessment and arthroscopic treatment of tendon, ligament, cartilage and synovial pathology. OrthoInfo
American Academy of Orthopaedic Surgeons / OrthoInfo
https://orthoinfo.aaos.org/globalassets/pdfs/arthroscopy.pdf
- 02Current general patient guidance on keyhole joint surgery, arthroscope technique, outpatient recovery and broad procedure-duration range according to complexity
National Health Service, 2025
https://www.nhs.uk/tests-and-treatments/arthroscopy
- 03Shoulder-specific guidance describing day-case diagnostic arthroscopy, small portals, general anaesthesia, postoperative sling use according to need, early mobilization and return to work after limited diagnostic surgery
Royal National Orthopaedic Hospital NHS Trust, 2025
https://www.rnoh.nhs.uk/patients-and-visitors/patient-information-guides/diagnostic-shoulder-arthroscopy-patients-guide
- 04Patient guidance covering shoulder arthroscopy, anaesthesia, hospital stay, pain, sling use, wound care, sleeping, driving and postoperative recovery considerations.
East Kent Hospitals University NHS Foundation Trust, 2025
https://leaflets.ekhuft.nhs.uk/s3/leaflets/shoulder-arthroscopy/
- 05Evidence-based patient guidance covering arthroscopic treatment of superior labral pathology, options including labral repair or biceps treatment, typical sling protection and progressive rehabilitation after repair.
American Academy of Orthopaedic Surgeons / OrthoInfo
https://orthoinfo.aaos.org/
- 06Clinical guidance describing arthroscopic stabilization, repair of the labrum and capsule with suture anchors, general anaesthesia and regional nerve block, and the small portal scars used for stabilization surgery.
Frimley Health NHS Foundation Trust, 2025
https://www.fhft.nhs.uk/patients-and-visitors/patient-information-library/guidelines-patients-arthroscopic-stabilisation-their-shoulder
- 07Evidence-based information on rotator cuff diagnosis, MRI and ultrasound assessment, nonsurgical treatment and surgical repair consideratio
American Academy of Orthopaedic Surgeons
https://orthoinfo.aaos.org/globalassets/pdfs/rotator-cuff-cpg_pls.pdf
- 08Patient guidance on conservative treatment, surgical indications and the several-month rehabilitation required after rotator cuff surgery.
American Academy of Orthopaedic Surgeons / OrthoInfo
https://orthoinfo.aaos.org/globalassets/pdfs/rotator-cuff-tears.pdf
- 09Contemporary systematic review showing progressive pain and functional recovery through three months, six months and one year after arthroscopic rotator cuff repair rather than immediate recovery after the small arthroscopic incisions heal.
EFORT Open Reviews / PubMed, 2025
https://pubmed.ncbi.nlm.nih.gov/41223034